

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Hemangioma pathophysiology
Introduction
Overview
Overview
Development of hemangioma is the result of genetic mutations, overexpression of angiogenic fators and downregulation of inhibitors of angiogenesis. Hemangioma may be associated with POEMS syndrome and Castleman disease. On gross pathology, spongy with vascular compartments of various sizes separated by fibrous tissue are findings of hemangioma. On microscopic histopathological analysis, channels lined by benign endothelium containing red blood cells are findings of hemangioma.
Pathophysiology
Pathophysiology
The pathogenesis of hemangiomas has not been elucidated, but there are two competing theories;
First theory
- The first theory supports the notion that there is overexpression of angiogenic factors such as:[1]
- And there is downregulation of some inhibitors of angiogenesis such as:[1]
Second theory
- The second theory is that the presence of liver hemangiomas involves a genetic background of mutations.[1]
- Genetic errors in growth factor receptors have also been shown to affect development of hemangiomas.
- Metalloproteinases can accumulate in the endoplasmic reticulum of the tumor cells causing:
- Self-digestion
- Vacuole formation
- Cavernous hemangioma cell can downregulate Derlin-1.
- Derlin-1 is a protein that when overexpressed induces the dilated endoplasmic reticulum to return to its normal size.
Third theory
- The third theory suggests that hemangioma endothelial cells arise from disrupted placental tissue imbedded in fetal soft tissues during gestation or birth.[2]
- Markers of hemangiomas have been shown to coincide with those found in placental tissue.
- This is further supported by the fact that they are found more commonly in infants following:[2]
Growth Pattern
- Hemangiomas follow a predictable course with three distinct developmental phases:[2]
- Proliferation phase
- Quiescence phase
- Involution phase
Proliferation phase
- In most hemangiomas, eighty percent of proliferation occurs by three months of life but may last longer.[2][3]
- During proliferation, rapid growth can lead to exhaustion of blood supply with resulting ischemia, necrosis, ulceration, and bleeding.
Quiescence phase
- Following proliferation, hemangiomas enter a slower or no growth phase, known as quiescence.[2]
- This phase typically lasts from nine to twelve months of age.
Involution phase
- The final and unique phase of the hemangioma lifecycle is involution.[2]
- This phase is marked by graying of the overlying skin and shrinking of the deeper components.
- At the final stages of involution, a fibrofatty protuberance may remain.
Associated Conditions
Associated Conditions
Hemangioma may be associated with:
Gross Pathology
Gross Pathology
- Grossly hemangiomas are described as “spongy” with vascular compartments of various sizes separated by fibrous tissue.[1]
- Thrombi may be present and are well separated from the normal liver parenchyma despite the absence of a fibrous capsule.
Microscopic Pathology
Microscopic Pathology
On microscopic histopathological analysis channels lined by benign endothelium containing red blood cells are findings of hemangioma.[3]
Gallery
-
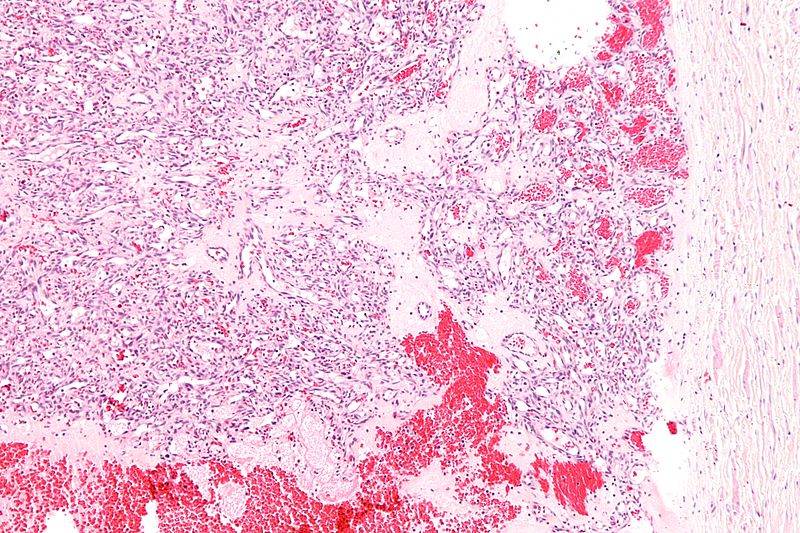 Intermediate magnification micrograph of a capillary hemangioma. H&E stain.[3]
-
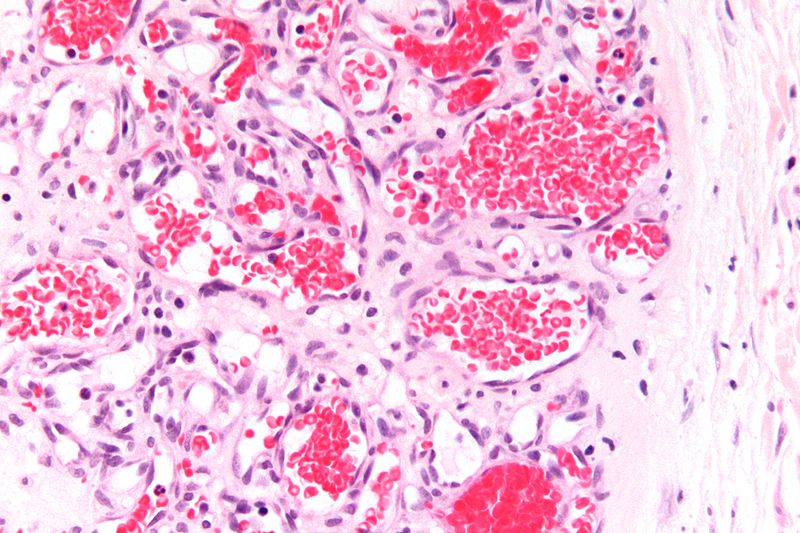 Very high magnification micrograph of a capillary hemangioma. H&E stain.[3]
-
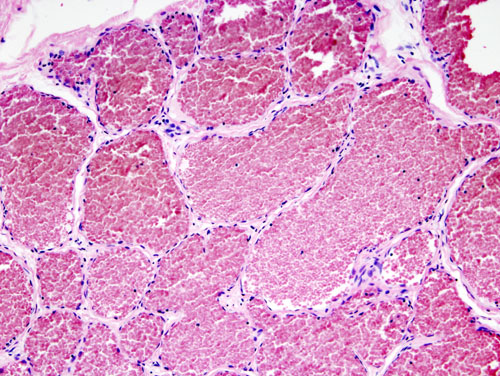 Histopathological image representing a cavernous hemangioma of the liver. Surgical excision of the lesion for the impending risk for rupture. H&E stain.[3]
-
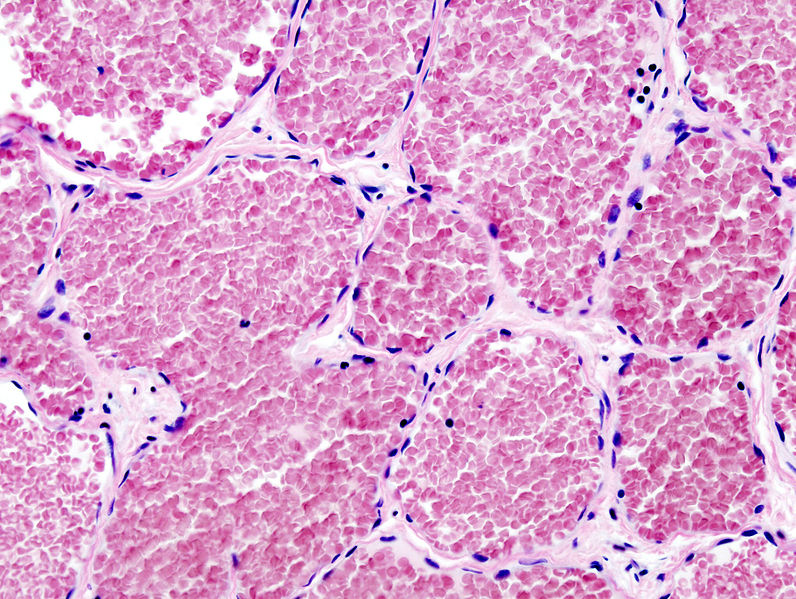 Histopathological image reprsenting a cavernous hemangioma of the liver. H&E stain.[3]


Immunohistochemistry
Immunohistochemistry
Hemangioma is demonstrated by positivity to:[3]
- CD31 positive
- D2-40 negative
References
References
- ↑ 1.0 1.1 1.2 1.3 Papafragkakis, Haris; Moehlen, Martin; Garcia-Buitrago, Monica T.; Madrazo, Beatrice; Island, Eddie; Martin, Paul (2011). “A Case of a Ruptured Sclerosing Liver Hemangioma”. International Journal of Hepatology. 2011: 1–5. doi:10.4061/2011/942360. ISSN 2090-3456.
- ↑ 2.0 2.1 2.2 2.3 2.4 2.5 Richter, Gresham T.; Friedman, Adva B. (2012). “Hemangiomas and Vascular Malformations: Current Theory and Management”. International Journal of Pediatrics. 2012: 1–10. doi:10.1155/2012/645678. ISSN 1687-9740.
- ↑ 3.0 3.1 3.2 3.3 3.4 3.5 3.6 Microscopic features of hemangioma. Librepathology (2015). http://librepathology.org/wiki/index.php/Hemangioma. Accessed on November 12, 2015
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Nawal Muazam M.D.[2]