

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Boil
Introduction
Synonyms and keywords: furuncle; furunculosis
For patient information click here
Overview
Overview
Boil or furuncle is a skin disease caused by the inflammation of hair follicles, thus resulting in the localized accumulation of pus and dead tissue. Individual boils can cluster together and form an interconnected network of boils called carbuncles. In severe cases, boils may develop to form abscesses.
Historical Perspective
Staphylococcus aureus was discovered in late 1870’s by Alexander Ogston, a surgeon at the Aberdeen Royal Infirmary. It was discovered to be the major cause of skin and soft tissue infections such as boils, staphylococcal scalded skin syndrome and impetigo[1] [2]. Carl Alois Philipp Garrè was a Swiss surgeon who proved that Staphylococcus aureus causes carbuncles and boils by self experimentation. Dr. Garre discovered and named Garre’s sclerosing osteomyelitis (sclerosing osteitis – form of chronic osteomyelitis with proliferative periostitis).[3]
Classification
Boil (furuncle) may be classified according to the International Classification of Diseases (ICD-10) based on anatomical location.[4] Based on the duration of symptoms, boils may be classified into acute and chronic.
Pathophysiology
Boil (furuncle) is a localized deep suppurative necrotizing form of folliculitis which involves the dermis and the subcutaneous tissue. Staphylococcus aureus is the most common causative agent. Following an abrasion or cut, the pathogen uses the wound site to invade and colonize the hair follicle. This leads to the formation of tender, erythematous, perifollicular nodule. The boil later becomes painful and fluctuant leading to discharge of pus and formation of necrotic plugs, which may leave a scar.[5]
Causes
Boils (furuncles) are generally caused by an infection of the hair follicles by Staphylococcus aureus or Staphylococcus epidermidis.
Differentiating Boil overview from Other Diseases
Boil (furuncle) must be differentiated from other common diseases that cause tender swelling or a reddened lump filled with pus such as cystic acne, hydradrenitis suppurativa, and pilonidal cyst.[6]
Epidemiology and Demographics
The incidence and prevalence of boils (furuncles) is uncertain. In England, between 2002-2003, boils and carbuncles were responsible for approximately 190 out of 100,000 hospital visits[7]. Patients with all age groups can develop boils(furuncles). Boils(furuncles) is common among teenagers and young adults.
Risk Factors
Common risk factors in the development of boils include immunosupression, malnutrition, coexisting skin conditions, and poor hygiene.
Screening
According to the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for furunculosis.
Natural History, Complications, and Prognosis
If left untreated, patients with boils (furuncles) may progress to develop carbuncles, fever, and lymphadenopathy. The most common complications of boils include scarring and recurrence. Other complications include septicemia leading to abscess of spinal cord, brain, kidneys, or other organs. The prognosis is generally good, however, it varies with underlying risk factors.
Diagnosis
History and Symptoms
A detailed and thorough history from the patient is necessary. Specific areas of focus when obtaining a history from the patient include history of immunosupression, family history of furunculosis, history of contact sports, history of close contact, and recent travel. Common symptoms of the boil include firm, red, and painful bump with pus filled head.[8][9][8]
Physical Examination
Patients with boils usually appear normal. However, the appearance varies with the associated risk factors.
Images
The following are the images associated with boils on extremities.


Laboratory Findings
Laboratory study which is consistent with the diagnosis of boils include the pus culture.
Imaging Findings
X ray may be performed to detect internal abscess and osteomyelitis.
Other Diagnostic Studies
Other diagnostic studies of boils include blood analysis, urine analysis, and biopsy.
Treatment
Medical Therapy
The mainstay of therapy for mild furuncles is incision and drainage only. Antimicrobial therapies are indicated in moderate and severe furuncles. Empiric antimicrobial therapies for furuncle include either TMP-SMX or Doxycycline for moderate furuncles, and either Vancomycin, Daptomycin, Linezolid, Telavancin, or Ceftaroline for severe furuncles.[10][11]
Surgery
Incision and drainage is indicated if the boil is deep large and persistent despite medical therapy.[12]
Prevention
Primary prevention
Effective measures for primary prevention of boils include hand washing, antibacterial soaps, maintain proper hygiene (hand sanitizers, antiseptic washes), avoid close contact (homeless shelters, military, prisons).
Secondary prevention
Secondary prevention strategies following boils are warm moist compresses on the boil, hand washing, and proper wound care.
References
- ↑ Methicillin resistant staphylococcus aureus. National institute of allergy and infectious diseases(2016) https://www.niaid.nih.gov/topics/antimicrobialresistance/examples/mrsa/Pages/history.aspx Accessed on August 12,2016
- ↑ Boil. London review of books. http://www.lrb.co.uk/v27/n24/hugh-pennington/dont-pick-your-nose accessed on August 12,2016
- ↑ Wikipedia. CarlGarre(boil). https://en.wikipedia.org/wiki/Carl_Garr%C3%A9 Accessed on August 12,2016
- ↑ ICD-10 Diagnosis Codes Index. http://icdlist.com/icd-10/index/cutaneous-abscess-furuncle-and-carbuncle-l02 Accessed on August 4,2016
- ↑ Ibler KS, Kromann CB (2014). “Recurrent furunculosis – challenges and management: a review”. Clin Cosmet Investig Dermatol. 7: 59–64. doi:10.2147/CCID.S35302. PMC 3934592. PMID 24591845.
- ↑ Boil(furuncle)(2016).https://en.wikipedia.org/wiki/Boil Accessed on August 9, 2016.
- ↑ Statistics about boil. Right diagnosis(2015). http://www.rightdiagnosis.com/b/boil/stats.htm Accessed on August 12,2016
- ↑ 8.0 8.1 Stevens, Dennis L., et al. “Practice guidelines for the diagnosis and management of skin and soft-tissue infections.” Clinical Infectious Diseases 41.10 (2005): 1373-1406.
- ↑ MedlinePlus https://medlineplus.gov/ency/article/001474.htm August 1,2016 Accessed on August 10,2016
- ↑ Gilbert, David (2015). The Sanford guide to antimicrobial therapy. Sperryville, Va: Antimicrobial Therapy. ISBN 978-1930808843.
- ↑ Boils(furuncle). MedlinePlus(2016). [1] Accessed on August 11,2016
- ↑ Boils(furuncle). MedlinePlus(2016). [2] Accessed on August 11,2016
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [3]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[4]Jesus Rosario Hernandez, M.D. [5]
Historical Perspective
Overview
Staphylococcus aureus was discovered in late 1870’s by Alexander Ogston, a surgeon at the Aberdeen Royal Infirmary. It was discovered to be the major cause of skin and soft tissue infections such as boils, staphylococcal scalded skin syndrome and impetigo.[1] [2] Carl Alois Philipp Garrè was a Swiss surgeon who proved that Staphylococcus aureus causes carbuncles and boils by self experimentation. Dr. Garre discovered and named Garre’s sclerosing osteomyelitis (sclerosing osteitis – form of chronic osteomyelitis with proliferative periostitis).[3]
Historical Perspective
- Staphylococcus aureus was discovered in late 1870’s by Alexander Ogston, a surgeon at the Aberdeen Royal Infirmary. It was the major cause of skin and soft tissue infections such as boils, staphylococcal scalded skin syndrome, and impetigo.[1] [2]
- Carl Alois Philipp Garre was a Swiss surgeon who proved that Staphylococcus aureus causes carbuncles and boils by self-experimentation. Dr. Garre discovered and named Garre’s sclerosing osteomyelitis (sclerosing osteitis – form of chronic osteomyelitis with proliferative periostitis).[3]
References
- ↑ 1.0 1.1 Methicillin resistant staphylococcus aureus. National institute of allergy and infectious diseases(2016) https://www.niaid.nih.gov/topics/antimicrobialresistance/examples/mrsa/Pages/history.aspx Accessed on August 12,2016
- ↑ 2.0 2.1 Boil. London review of books. http://www.lrb.co.uk/v27/n24/hugh-pennington/dont-pick-your-nose accessed on August 12,2016
- ↑ 3.0 3.1 Wikipedia. CarlGarre(boil). https://en.wikipedia.org/wiki/Carl_Garr%C3%A9 Accessed on August 12,2016
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Classification
Overview
Boils (furuncles) may be classified according to the International Classification of Diseases (ICD-10) based on anatomical location.[1]
Classification
Boil (furuncle) may be classified according to the International Classification of Diseases (ICD-10) based on anatomical location:[1][2]
- Furuncle of face
- Furuncle of neck
- Furuncle of trunk
- Furuncle of buttock
- Furuncle of limb
- Furuncle of hand
- Furuncle of foot
- Furuncle of other sites
- Furuncle, unspecified
Based on the duration of symptoms, boils may be classified into:[3]
References
- ↑ 1.0 1.1 ICD-10 Diagnosis Codes Index. http://icdlist.com/icd-10/index/cutaneous-abscess-furuncle-and-carbuncle-l02 Accessed on August 4,2016
- ↑ Dings JP, van Damme PA (2008). “[Face the facial furuncle]”. Ned Tijdschr Tandheelkd. 115 (3): 125–31. PMID 18444499.
- ↑ TULLOCH LG, ALDER VG, GILLESPIE WA (1960). “Treatment of chronic furunculosis”. Br Med J. 2 (5195): 354–6. PMC 2097510. PMID 13839797.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Pathophysiology
Overview
Boils (furuncles) are a localized deep suppurative necrotizing form of folliculitis which involve the dermis and the subcutaneous tissue. Staphylococcus aureus is the most common causative agent. Following an abrasion or cut, the pathogen uses the wound site to invade and colonize the hair follicle. This leads to the formation of tender, erythematous, perifollicular nodule. The boil later becomes painful and fluctuant leading to discharge of pus and formation of necrotic plugs, which may leave a scar.[1]
Pathophysiology
Pathogenesis
- Boil (furuncle) is a localized deep suppurative necrotizing form of folliculitis which involves the dermis and the subcutaneous tissue. Staphylococcus aureus is the most common causative agent.
- Following abrasion or cut the pathogen uses the wound site to invade and colonize the hair follicle. This leads to the formation of a tender erythematous perifollicular nodule.
- Boils may become painful and fluctuant, leading to the discharge of pus and formation of necrotic plugs, which may leave a scar.[1]
- Furunculosis is the acute or chronic appearance of a number of boils (furuncles) at multiple skin sites. Recurrent furunculosis is defined as three or more attacks within a 12 month period.[1]
- It is a contagious condition, which usually develops in moist or sweaty areas such as the scalp, face, buttocks, axillae, and areas that are subject to friction and perspiration.
- A group of furuncles coalesce to form a carbuncle.
Schematic of Pathogenesis
-
 Boil(furuncle)pathogenesis

Associated Conditions
Gross Pathology
On gross pathology, characteristic findings of boils include firm, tender, red, dome shaped nodules, which progress to fluctuant, pus-filled, and painful lesions. Boils may vary in size.
Microscopic histopathological analysis
On microscopic histopathological analysis, characteristic findings of boils include:
- Infiltrate predominantly consists of neutrophils within the wall and ostia of hair follicles
- Lesions may subsequently be infiltrated with lymphocytes and macrophages creating a central focus of necrosis.
- Inflammation of hair follicle may be:
- Superficial (primarily involving the infandibulum)
- Deep
Examples of Gross Pathology
The following are images associated with boil:
-
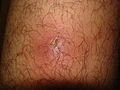 Boil(furuncle) on Anterior leg: Dome shaped pus filled boil(furuncle) with erythema of skin – By The original uploader was Mahdouch at French Wikipedia – Transferred from fr.wikipedia to Commons., CC BY 1.0, https://commons.wikimedia.org/w/index.php?curid=3123389

References
- ↑ 1.0 1.1 1.2 Ibler KS, Kromann CB (2014). “Recurrent furunculosis – challenges and management: a review”. Clin Cosmet Investig Dermatol. 7: 59–64. doi:10.2147/CCID.S35302. PMC 3934592. PMID 24591845.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Causes
Overview
Boils (furuncles) are generally caused by an infection of the hair follicles by Staphylococcus aureus or Staphylococcus epidermidis.
Causes
Common causes of boils include:[1]
Bacteria:
- Staphylococcus aureus is the most common cause of furunculosis.
- Colonization of Staphylococcus aureus in the anterior nares and in the warm, moist skin folds such as behind ears, under pendulous breasts and in the groin plays a definitive role in the etiology of chronic or recurrent furunculosis.[2]
- Infection with Methicillin resistant staphylococcus aureus is the leading cause of morbidity and mortality in patients with furunculosis.[3]
Other bacterial causes:
- Enterobacteriaceae
- Enterococci
- Corynebacterium
- Streptococcus epidermidis
- Streptococcus pyogenes
- Pseudomonas Aeruginosa
Fungal causes
- Candida
- Pityrosporum species
Other causes
- Ingrown hair
- Blocked glands
References
- ↑ MedlinePlus https://medlineplus.gov/ency/article/001474.htm August 1,2016 Accessed on August 10,2016
- ↑ Le Bozec P (1996). “[Follicular staphylococcal infections]”. Rev Prat. 46 (13): 1599–602. PMID 8949489.
- ↑ Venniyil PV, Ganguly S, Kuruvila S, Devi S (2016). “A study of community-associated methicillin-resistant Staphylococcus aureus in patients with pyoderma”. Indian Dermatol Online J. 7 (3): 159–63. doi:10.4103/2229-5178.182373. PMC 4886585. PMID 27294048.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Differentiating a Boil from other Diseases
Overview
Boil (furuncle) must be differentiated from other common diseases that cause tender swelling or a reddened lump filled with pus such as cystic acne, hydradrenitis suppurativa, and pilonidal cyst.[1]
Differentiating Boil(furuncle) from Other Diseases
Boils must be differentiated from:[1]
| Disease | Findings |
|---|---|
| Cystic acne | Presents with tender cystic pustules usually confined to the face and trunk, where there are higher concentration of sebaceous glands. |
| Hydradrenitis suppurativa | Presents as painful suppurative lesions in the axillary, genital and perianal areas, where there are higher concentration of apocrine glands. Chronic disease may cause irregular sinus tracts and scarring. Diagnosis is primarily clinical based on distribution, characteristic lesions and recurrence. |
| Pilonidal cyst | The cyst usually contains skin and hair debris, which if gets infected results in painful pus filled nodule at the bottom of tail bone (coccyx). Diagnosis is based on physical examination. |
| Others | Anthrax, Herpetic whitlow, Cellulitis, Furuncular myasis, Impetigo herpitiformis, SAPHO syndrome, Interleukin 1 receptor antagonist deficiency, sporotrichosis and Eosinophilic pustular folliculitis can produce signs and symptoms that may be confused with boils(furuncles). |
References
- ↑ 1.0 1.1 Boil(furuncle)(2016).https://en.wikipedia.org/wiki/Boil Accessed on August 9, 2016.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Epidemiology and Demographics
Overview
The incidence and prevalence of boils (furuncles) is uncertain. In England, between 2002-2003, boils and carbuncles were responsible for approximately 190 out of 100,000 hospital visits[1]. Patients in all age groups can develop furuncles; however, they are common among teenagers and young adults.
Epidemiology and Demographics
Incidence
- In England, between 2002-2003, boils and carbuncles were responsible for approximately 190 out of 100,000 hospital visits[1]
Age
- Patients of all age groups may develop furuncles. However, furuncles most commonly occur in teenagers and young adults.
- Recurrent boils cause significant mortality and morbidity among adult population in both developed and developing countries.
Gender
Furuncles affect men and women equally.
Race
There is no racial predilection to boils.
References
- ↑ 1.0 1.1 Statistics about boil. Right diagnosis(2015). http://www.rightdiagnosis.com/b/boil/stats.htm Accessed on August 12,2016
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Risk Factors
Overview
Common risk factors in the development of boils include immunosupression, malnutrition, coexisting skin conditions, and poor hygiene.
Risk Factors
Common risk factors in the development of boils include:
- Obesity
- Sports
- Athletes participating in contact sports and using shared equipment
- Malnutrition
- Coexisting skin conditions
- Staphylococcal carriers[3]
- Most common site: anterior nares[4][5][2]
- Poor hygiene
- People living in close contact
- Low socioeconomic status
- living in military barracks, homeless shelters, or prison
- Recent travel
References
- ↑ ANNING ST (1953). “Recurrent boils”. Br Med J. 1 (4812): 721–3. PMC 2015621. PMID 13032475.
- ↑ 2.0 2.1 TULLOCH LG, ALDER VG, GILLESPIE WA (1960). “Treatment of chronic furunculosis”. Br Med J. 2 (5195): 354–6. PMC 2097510. PMID 13839797.
- ↑ Kluytmans J, van Belkum A, Verbrugh H (1997). “Nasal carriage of Staphylococcus aureus: epidemiology, underlying mechanisms, and associated risks”. Clin Microbiol Rev. 10 (3): 505–20. PMC 172932. PMID 9227864.
- ↑ Mertz D, Frei R, Jaussi B, Tietz A, Stebler C, Flückiger U; et al. (2007). “Throat swabs are necessary to reliably detect carriers of Staphylococcus aureus”. Clin Infect Dis. 45 (4): 475–7. doi:10.1086/520016. PMID 17638197.
- ↑ ROODYN L (1954). “Staphylococcal infections in general practice”. Br Med J. 2 (4900): 1322–5. PMC 2080205. PMID 13209110.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Screening
Overview
According to the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for furunculosis.
Screening
According to the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for furunculosis.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Natural History, Complications and Prognosis
Overview
If left untreated, patients with boils (furuncles) may progress to develop carbuncles, fever, and lymphadenopathy. The most common complications of boils include scarring and recurrence. Other complications include septicemia leading to abscess of spinal cord, brain, kidneys, or other organs. The prognosis is generally good, however, it varies with underlying risk factors.
Natural History
- If left untreated, patients with boils may progress to develop carbuncles, fever and lymphadenopathy. The most common complications of boils include scarring and recurrence. Other rare complications are bacteremia, fever, and abscess of spinal cord, brain, kidneys, or other organs.
- Recurrent furunculosis is commonly caused by methicillin susceptible staphylococcus aureus however Panton-Valentine leukocidin staphylococcus aureus (PVL-SA) and community acquired MRSA (CA-MRSA) is the leading cause of severe infection.[1][2][3]
Complications
Common complications of furuncles include:[4][2][5][6][7]
- Permanent scarring
- Recurrence
- Abscess of the skin, spinal cord, brain, kidneys, or other organ
- Endocarditis
- Osteomyelitis
- Sepsis
- Infection of brain
- Infection of spinal cord
- Spread of infection to other parts of body or skin surfaces
Prognosis
- Prognosis is generally good and a full recovery is expected.[6]
- The prognosis varies with underlying risk factors or subsequent complications.
References
- ↑ Venniyil PV, Ganguly S, Kuruvila S, Devi S (2016). “A study of community-associated methicillin-resistant Staphylococcus aureus in patients with pyoderma”. Indian Dermatol Online J. 7 (3): 159–63. doi:10.4103/2229-5178.182373. PMC 4886585. PMID 27294048.
- ↑ 2.0 2.1 Ibler KS, Kromann CB (2014). “Recurrent furunculosis – challenges and management: a review”. Clin Cosmet Investig Dermatol. 7: 59–64. doi:10.2147/CCID.S35302. PMC 3934592. PMID 24591845.
- ↑ Masiuk H, Kopron K, Grumann D, Goerke C, Kolata J, Jursa-Kulesza J; et al. (2010). “Association of recurrent furunculosis with Panton-Valentine leukocidin and the genetic background of Staphylococcus aureus”. J Clin Microbiol. 48 (5): 1527–35. doi:10.1128/JCM.02094-09. PMC 2863926. PMID 20200289.
- ↑ ROODYN L (1954). “Staphylococcal infections in general practice”. Br Med J. 2 (4900): 1322–5. PMC 2080205. PMID 13209110.
- ↑ Medows M, Sharma A (2013). “Lancing of a boil leading to severe invasive methicillin-sensitive Staphylococcus aureus infection in an adolescent”. BMJ Case Rep. 2013. doi:10.1136/bcr-2013-200651. PMC 3863041. PMID 24336580.
- ↑ 6.0 6.1 MedlinePlus https://medlineplus.gov/ency/article/001474.htm August 1,2016 Accessed on August 10,2016
- ↑ ANNING ST (1953). “Recurrent boils”. Br Med J. 1 (4812): 721–3. PMC 2015621. PMID 13032475.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]
Diagnosis
Diagnosis
History and Symptoms | Physical Examination | Laboratory Findings | Electrocardiogram | X Ray | CT | MRI | Echocardiography or Ultrasound | Other Imaging Findings | Other Diagnostic Studies
Treatment
Treatment
Medical Therapy | Surgery | Primary Prevention | Secondary Prevention | Cost-Effectiveness of Therapy | Future or Investigational Therapies
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Yamuna Kondapally, M.B.B.S[2]