

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Insulinoma
Introduction
For patient information click here
Synonyms and keywords: Pancreatic beta cell tumor; tumor of beta cells; beta cell tumor; cancer of beta cells
Overview
Overview
Insulinoma is the tumor of β islet cells of pancreas involved in the production of insulin. They are rare tumors and the incidence varies from 0.1 to 0.4 per 100,000. It commonly affects females in the age group of 40-60 years. It is associated with diseases such as MEN1, Von Hippel-Lindau, and Neurofibromatosis. The overproduction of insulin causes hypoglycemia and manifests as neuroglycopenic symptoms such as altered mental status, confusion, coma and adrenergic symptoms such as profuse sweating, tremors and palpitations. There are no physical exam findings usually. It is suspected by the presence of Whipple’s triad which is serum glucose < 55mg/dL, features/symptoms of hypoglycemia as described above and resolution of symptoms with administration of glucose. The gold standard for diagnosis is 72-hour fasting and the laboratory findings include serum glucose < 55 mg/dL . Insulin > 5-10 μU/mL, S. C-Peptide >200 pmol/L, S. proinsulin ≥ 22 pmol/L. CT scan is the first line of investigation. The highest sensitivity is seen in dual-phase helical CT with thin slices up to 94.4%. MRI is the second line of investigation. Trans-abdominal ultrasound and X-ray have less sensitivity in detecting insulinoma. Invasive modalities like endoscopic ultrasound are adopted if CT and MRI are inconclusive. Other diagnostic modalities include PET scan, intra-operative ultrasound and arterial calcium stimulation with hepatic vein sampling (ASVS).
Historical Perspective
In 1869, pancreatic islet cells were discovered by Paul Langerhans and the first adenoma of islets was discovered by Nicholls in 1902. Insulin was first discovered by Banting and Best in 1922. Association between hyperinsulinism and functional islet tumor was described in 1926 by Wilder. In 1927, the insulinoma was first described in Mayo clinic which was dissected in 1929 in Toronto. In 1929, the first surgical cure was performed by Roscoe Graham. In 1935, Whipple suggested a diagnostic criterion for the diagnosis of insulinoma called as Whipple’s triad.
Classification
Insulinoma may be classified according to their malignant potential into 2 sub-types: Benign (90%) and malignant (10%). It is also classified into 2 subtypes based on the number: solitary (90%) and multiple (10%). Previously, insulinoma was classified into 2 subtypes based on hormonal level as determined by radioimmunoassay into group A and group B. The staging of malignant insulinoma is based on the AJCC 2010, ENETS and modified ENETS staging classification.
Pathophysiology
Insulinoma arises from β islet cells, which are endocrine cells that are normally involved in the production of insulin. It is thought that insulinoma is mediated by mTOR/P70S6K signaling pathway. Thus, inhibitors of mTOR (rapamycin) or dual PI3K/mTOR (NVP-BEZ2235) have become new drugs for treating insulinoma. YY1 gene is mutated by T372R mutation that causes a defect in mitochondrial function for glucose-stimulated insulin action which is thought to be involved in mTOR pathway. The progression to hypoglycemia is actually because of decreased glucose synthesis rather than increased use due to the direct effect of insulin on the liver. Insulinoma is transmitted in an autosomal dominant pattern when it is associated with MEN 1 syndrome. They are usually small (90%), sporadic (90%), solitary (90%) and benign (90%) tumors. On gross pathology insulinomas are encapsulated and have a gray to red-brown appearance. On microscopic histopathological analysis, patterns like trabecular, gyriform, lobular and solid structures, particularly with amyloid in the fibrovascular stroma, are characteristic findings of insulinoma. It is also evaluated for the mitotic index (mitosis per 10 high power field) and immunohistochemistry staining by Chromogranin A, synaptophysin, and Ki-67 index. The structure of tumor cells observed under electron microscopy as group A characterized by abundant well-granulated typical β cells with a trabecular arrangement and group B as scarce well-granulated typical β cells and a medullary arrangement.
Causes
There are no established causes for insulinoma.
Differential Diagnosis
Insulinoma must be differentiated from other diseases that cause features of hypoglycemia like altered mental status/confusion, profuse sweating and visual disturbances (blurring/diplopia). These are classified on the basis of laboratory findings into exogenous insulin, oral hypoglycemic agents (e.g. sulphonylureas), nesidioblastosis, insulin autoimmune hypoglycemia.
Epidemiology and Demographics
The incidence of insulinoma is approximately 0.1-0.4 per 100,000 individuals that constitute 1-2% of all pancreatic neoplasms. The female to male ratio is approximately 3:2. There is no regional predisposition.
Risk Factors
Common risk factors in the development of insulinoma include female gender, age:40-60 years, MEN1 syndrome, Von Hippel-Lindau disease, and Neurofibromatosis 1.
Screening
There is insufficient evidence to recommend routine screening for insulinoma.
Natural History, Complications and Prognosis
If left untreated, patients with insulinoma may progress to develop seizures, coma and even death. Prognosis is generally excellent for benign insulinoma after the removal of the tumor. Recurrence rates are higher in those associated with MEN1 syndrome.
Staging
The staging had been done according to American Joint Cancer Committee (AJCC) 7th edition 2010. Being a pancreatic neuroendocrine tumor, it is also staged by European Neuroendocrine Tumor Society (ENETS). In its new 8th edition of AJCC which is planned to be published on January 1, 2018; AJCC had developed a modified ENETS (mENETS) staging classification.
History and Symptoms
A positive long history of frequent episodes of altered mental status/confusion, visual disturbances and sweating is suggestive of insulinoma. The most common symptoms of insulinoma include altered mental status/confusion, visual disturbances like blurred vision/diplopia, sweating, hyperphagia and coma. Less common symptoms of insulinoma include palpitations, seizures, tremors, behavioral disturbances and weakness.
Physical Examination
Physical examination of patients with insulinoma is usually unremarkable.
Laboratory Findings
Laboratory findings consistent with the diagnosis of insulinoma include serum glucose < 55 mg/dL; serum insulin > 5-10 μU/mL; serum C-Peptide > 200 pmol/L and serum proinsulin ≥ 22 pmol/L. Patients with insulinoma may have elevated insulin to glucose ratio > 0.4, which is usually suggestive of insulinoma after a 72-hour fast test as a gold standard test. One-thirds or 33% patients have clinical symptoms within 12 hours of fasting, 80% develop within 24 hours, 90% develop within 48 hours and 100% develop within 72 hours.
CT
CT scan is currently accepted as the first line of investigation for diagnosing insulinoma. Currently, with the advances in technology, the sensitivity has risen to 80% and 94.4% for helical CT scan with dual-phase multi-detector CT scan. Insulinoma is hypervascular and thus CT shows greater enhancement (hyper-attenuation) than rest of the pancreatic parenchyma. Cystic and nodular masses with calcification indicates malignant insulinoma. Metastasis can be detected by CT scan.
MRI
MRI has better sensitivity than CT scan. However, it is still considered as the second line of investigation due to cost and availability. Insulinoma shows low intensity on T1 weighted and high intensity on T2 weighted signals, having better visualization on T1 and T2 weighted images with fat suppression.They exhibit typically homogenous enhancement when small and ring enhancement when more than 2 cm. A similar pattern is seen in metastatic lesion as of primary tumor.
Ultrasonography
Trans-abdominal ultrasound has low sensitivity varying between 0 to 66% in detecting insulinoma. The sensitivity increases with the use of more invasive technique including endoscopic ultrasound (93%) and intra-operative ultrasound (86%). We see hypo-echoic lesions and hypervascular mass on the ultrasound.
Other Imaging Findings
The other imaging studies include positron emission tomography (PET) and somatostatin receptor Scintigraphy (SRS) which are nuclear studies used for detecting somatostatin receptor especially subtype 2 using radioisotopes of Gallium. The increased uptake of radioligands is suggestive of insulinoma. The metastasis also shows the increased uptake. The sensitivity of PET is increased by doing a CT scan coupled with PET scan. The sensitivity of SRS is 50 to 60% as insulinomas have less somatostatin subtype 2 receptor which is detected by the test.
Other Diagnostic Studies
Arterial calcium stimulation with hepatic venous sampling (ASVS) is an invasive diagnostic study which is used when all other imaging studies are inconclusive. Findings are noted after calcium stimulation of tumor supplying arteries and in the hepatic venous samples which show the positive response of a two-fold or greater increase in insulin levels.
Medical Therapy
Medical therapy is reserved for those who can’t undergo the primary surgical therapy. Drugs commonly used for benign insulinoma are diazoxide, octreotide/lanreotide, Phenytoin, verapamil and everolimus. For malignant insulinoma, these drugs are used with the chemotherapy drugs streptozocin, 5-fluorouracil, doxorubicin, bevacizumab and capecitabine in different combinations. For metastasis mainly going to liver regimens include hepatic artery embolization, radiation, chemo-embolization, ethanol ablation radiofrequency ablation and cryoablation.
Surgery
Surgery is the mainstay of treatment for insulinoma. The feasibility of surgery depends on the stage of insulinoma at diagnosis.
Primary Prevention
There is no established method for prevention of insulinoma.
Secondary Prevention
There are no secondary preventive measures available for insulinoma.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Historical Perspective
Overview
In 1869, pancreatic islet cells were discovered by Paul Langerhans. The first adenoma of islets was discovered by Nicholls in 1902. Insulin was first discovered by Banting and Best in 1922. Association between hyperinsulinism and functional islet tumor was described in 1926 by Wilder. In 1927, the insulinoma was first described in Mayo clinic which was dissected in 1929 in Toronto. In 1929, the first surgical cure was performed by Roscoe Graham. In 1935, Whipple suggested a diagnostic criterion for the diagnosis of insulinoma called as Whipple’s triad.
Historical Perspective
Discovery
- Pancreatic islet cells were first described by Paul Langerhans in 1869 when he was still a medical student.
- In 1902, the first adenoma of pancreatic islets was discovered by Nicholls.[1]
- Insulin was first discovered by Frederick Banting and Charles Best in 1922 from a dog’s pancreas.
- The association between hyperinsulinism and functional islet tumor was made in 1926 by Wilder-et-al after a surgery on a person who had hypoglycemia and found an islet cell cancer with liver metastasis.[2]
- In 1927, William J Mayo was the first to discover the association between hyperinsulinism and a functional pancreatic islet cell tumor. In 1927 the insulinoma was first described in Mayo clinic which was dissected in 1929 in Toronto.[1]
- In 1929, the first surgical cure was performed by Roscoe Graham.[3]
- In 1935, Whipple suggested a diagnostic criterion for the diagnosis of insulinoma called as Whipple’s triad. [3]
Landmark Events in the Development of Treatment Strategies
- William J Mayo did the first operation for insulinoma in 1927 and found it to be unresectable. Two years later, Roscoe Graham successfully completed the first surgical cure of an islet cell tumor.
- In 1935, Whipple’s triad was developed by Virginia Kneeland Frantz and Allen O. Whipple to diagnose insulinoma.
Famous Cases
- Steve Jobs, the founder, and CEO of Apple Inc. had died on Oct 5,2011 due to pancreatic neuroendocrine cancer.
- Dag Kittlaus, the creator of “Siri” had been diagnosed with a pancreatic neuroendocrine tumor in 2016.
References
- ↑ 1.0 1.1 Stamatakos M, Safioleas C, Tsaknaki S, Safioleas P, Iannescu R, Safioleas M (2009). “Insulinoma: a rare neuroendocrine pancreatic tumor”. Chirurgia (Bucur). 104 (6): 669–73. PMID 20187464.
- ↑ Wilder, Russell M.; Allan, Frank N.; Power, M. H.; Robertson, H. E. (1927). “CARCINOMA OF THE ISLANDS OF THE PANCREAS”. Journal of the American Medical Association. 89 (5): 348. doi:10.1001/jama.1927.02690050014007. ISSN 0002-9955.
- ↑ 3.0 3.1 Whipple AO, Frantz VK (1935). “ADENOMA OF ISLET CELLS WITH HYPERINSULINISM: A REVIEW”. Ann. Surg. 101 (6): 1299–335. PMC 1390871. PMID 17856569.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2], Parminder Dhingra, M.D. [3]
Classification
Overview
Insulinoma may be classified according to their malignant potential into 2 sub-types: Benign (90%) and malignant (10%). It is also classified into 2 subtypes based on the number: solitary (90%) and multiple (10%). Previously insulinoma was classified into 2 subtypes based on hormonal level as determined by radioimmunoassay into group A and group B. The staging of malignant insulinoma is based on the AJCC 2010, ENETS and modified ENETS staging classification.
Classification
| Classification of insulinoma | ||
|---|---|---|
| Criteria | Classification | Features |
| Malignancy potential | Benign |
|
| Malignant |
| |
| Based on number | Solitary |
|
| Multiple |
| |
| Based on the functionality
(clinical manifestations) |
Functional |
|
| Non-functional[7] | ||
| Based on hormonal level determined by radioimmunoassay[8]
(previously used) |
Group A |
|
| Group B |
| |
American Joint Cancer Committee (AJCC) 7th edition 2010 calssification
The staging of malignant insulinoma being a pancreatic neuroendocrine tumor may be classified into several subtypes based on American Joint Cancer Committee (AJCC) 7th edition 2010: [9][10]
| Stage | T | N | M |
| IA | T1 | N0 | M0 |
| IB | T2 | N0 | M0 |
| IIA | T3 | N0 | M0 |
| IIB | T1-3 | N1 | M0 |
| III | T4 | Any N | M0 |
| IV | Any T | Any N | M1 |
| AJCC 2010 | |||
| T | T1 | <2 cm in greatest dimension | |
|---|---|---|---|
| T2 | >2 cm in greatest dimension | ||
| T3 | Beyond the pancreas but without involvement of the superior mesenteric artery | ||
| T4 | Involvement of the celiac axis or superior mesenteric artery (unresectable tumor) | ||
| N | N0 | No regional lymph node metastasis | |
| N1 | Regional lymph node metastasis | ||
| M | M0 | No distant metastasis | |
| M1 | Distant metastasis | ||
European Neuroendocrine Tumor Society (ENETS) classification:
Being a pancreatic neuroendocrine tumor, it is also staged by European Neuroendocrine Tumor Society (ENETS) as: [9][10]
| Stage | T | N | M |
| I | T1 | N0 | M0 |
| IIA | T2 | N0 | M0 |
| IIB | T3 | N0 | M0 |
| IIIA | T4 | N0 | M0 |
| III B | Any T | N1 | M0 |
| IV | Any T | Any N | M1 |
| ENETS | |||
| T | T1 | Tumor limited to pancreas, <2 cm | |
|---|---|---|---|
| T2 | Tumor limited to pancreas, 2-4 cm | ||
| T3 | >4cm, or invading the duodenum or common bile duct | ||
| T4 | Tumor invades adjacent structures | ||
| N | N0 | No regional lymph node metastasis | |
| N1 | Regional lymph node metastasis | ||
| M | M0 | No distant metastasis | |
| M1 | Distant metastasis | ||
WHO 2010 classification system
- WHO classification system combined differentiation and grading characteristics to classify the belligerence of a pancreatic neuroendocrine tumor.
- The aggressiveness of tumor was expressed in form of mitotic count and staining of a nuclear antigen called Ki-67: [11][6]
| Grade of tumor | Mitotic Count(Mitoses per 10 high powerfields) | Expression of Ki 67 |
| Grade 1 | <2 | ≤3% |
| Grade 2 | 2-10 | 3-20% |
| Grade 3 | >20 | >20% |
- Grade 1 and 2 tumors were classified as neuroendocrine neoplasm (NET) and grade 3 were classified as neuroendocrine carcinoma (NEC).
- In its new 8th edition of AJCC which is planned to be published on January 1, 2018; AJCC had developed a modified ENETS (mENETS) staging classification:[9]
| Stage | T | N | M |
| IA | T1 | N0 | M0 |
| IB | T2 | N0 | M0 |
| IIA | T3 | N0 | M0 |
| IIB | T1-3 | N1 | M0 |
| III | T4 | Any N | M0 |
| IV | Any T | Any N | M1 |
| mENETS | ||
| T | T1 | Tumor limited to pancreas, <2 cm |
|---|---|---|
| T2 | Tumor limited to pancreas, 2-4 cm | |
| T3 | >4cm, or invading the duodenum or common bile duct | |
| T4 | Tumor invades adjacent structures | |
| N | N0 | No regional lymph node metastasis |
| N1 | Regional lymph node metastasis | |
| M | M0 | No distant metastasis |
| M1 | Distant metastasis | |
References
- ↑ F. J. Service, M. M. McMahon, P. C. O’Brien & D. J. Ballard (1991). “Functioning insulinoma–incidence, recurrence, and long-term survival of patients: a 60-year study”. Mayo Clinic proceedings. 66 (7): 711–719. PMID 01677058.
- ↑ Ahmad N, Almutawa AM, Abubacker MZ, Elzeftawy HA, Bawazir OA (2017). “Recurrent insulinoma in a 10-year-old boy with Down’s syndrome”. Endocrinol Diabetes Metab Case Rep. 2017. doi:10.1530/EDM-16-0155. PMC 5445445. PMID 28567298.
- ↑ de Herder, Wouter W.; Niederle, Bruno; Scoazec, Jean-Yves; Pauwels, Stanislas; Klöppel, Günter; Falconi, Massimo; Kwekkeboom, Dik J.; Öberg, Kjel; Eriksson, Barbro; Wiedenmann, Bertram; Rindi, Guido; O’Toole, Dermot; Ferone, Diego (2007). “Well-Differentiated Pancreatic Tumor/Carcinoma: Insulinoma”. Neuroendocrinology. 84 (3): 183–188. doi:10.1159/000098010. ISSN 0028-3835.
- ↑ Schott M, Klöppel G, Raffel A, Saleh A, Knoefel WT, Scherbaum WA (2011). “Neuroendocrine neoplasms of the gastrointestinal tract”. Dtsch Arztebl Int. 108 (18): 305–12. doi:10.3238/arztebl.2011.0305. PMC 3103981. PMID 21629514.
- ↑ Bosman, F. T. (2010). WHO classification of tumours of the digestive system. Lyon: International Agency for Research on Cancer. ISBN 978-9283224327.
- ↑ 6.0 6.1 Sun J (2017). “Pancreatic neuroendocrine tumors”. Intractable Rare Dis Res. 6 (1): 21–28. doi:10.5582/irdr.2017.01007. PMC 5359348. PMID 28357177.
- ↑ Mittendorf EA, Liu YC, McHenry CR (2005). “Giant insulinoma: case report and review of the literature”. J Clin Endocrinol Metab. 90 (1): 575–80. doi:10.1210/jc.2004-0825. PMID 15522939.
- ↑ Berger M, Bordi C, Cüppers HJ, Berchtold P, Gries FA, Münterfering H; et al. (1983). “Functional and morphologic characterization of human insulinomas”. Diabetes. 32 (10): 921–31. PMID 6311653.
- ↑ 9.0 9.1 9.2 Luo G, Javed A, Strosberg JR, Jin K, Zhang Y, Liu C; et al. (2017). “Modified Staging Classification for Pancreatic Neuroendocrine Tumors on the Basis of the American Joint Committee on Cancer and European Neuroendocrine Tumor Society Systems”. J Clin Oncol. 35 (3): 274–280. doi:10.1200/JCO.2016.67.8193. PMID 27646952.
- ↑ 10.0 10.1 Yang M, Zeng L, Zhang Y, Wang WG, Wang L, Ke NW; et al. (2015). “TNM staging of pancreatic neuroendocrine tumors: an observational analysis and comparison by both AJCC and ENETS systems from 1 single institution”. Medicine (Baltimore). 94 (12): e660. doi:10.1097/MD.0000000000000660. PMC 4554009. PMID 25816036.
- ↑ Bosman, F. T. (2010). WHO classification of tumours of the digestive system. Lyon: International Agency for Research on Cancer. ISBN 978-9283224327.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Pathophysiology
Overview
Insulinoma arises from β islet cells, which are endocrine cells that are normally involved in the production of insulin. It is thought that insulinoma is mediated by mTOR/P70S6K signaling pathway. Thus, inhibitors of mTOR (rapamycin) or dual PI3K/mTOR (NVP-BEZ2235) have become new drugs for treating insulinoma. YY1 gene is mutated by T372R mutation that causes a defect in mitochondrial function for glucose-stimulated insulin action which is thought to be involved in mTOR pathway. The progression to hypoglycemia is actually because of decreased glucose synthesis rather than increased use due to the direct effect of insulin on the liver. Insulinoma is transmitted in an autosomal dominant pattern when it is associated with MEN 1 syndrome. They are usually small (90%), sporadic (90%), solitary (90%) and benign (90%) tumors. On gross pathology insulinomas are encapsulated and have a gray to red-brown appearance. On microscopic histopathological analysis, patterns like trabecular, gyriform, lobular and solid structures, particularly with amyloid in the fibrovascular stroma, are characteristic findings of insulinoma. It is also evaluated for the mitotic index (mitosis per 10 high power field) and immunohistochemistry staining by Chromogranin A, synaptophysin, and Ki-67 index. The structure of tumor cells observed under electron microscopy as group A characterized by abundant well-granulated typical β cells with a trabecular arrangement and group B as scarce well-granulated typical β cells and a medullary arrangement.
Pathophysiology
Pathogenesis
- Insulinoma is a rare benign pancreatic neuroendocrine tumor that arises from β islet cells, which are cells that are normally involved in the production of insulin. Few insulinomas can also produce other hormones such as Serotonin, gastrin, ACTH, glucagon, and somatostatin. [1]
- They are usually small (90%), sporadic (90%), solitary (90%) and benign (90%) tumors.
- It usually occurs sporadically (90%) but 10% are found to be associated with MEN 1 syndrome.[2] Those associated with the MEN1 syndrome are usually malignant and higher recurrence rate (21% at 10 and 20 years) than in those without MEN 1 (5% at 10 and 7% at 20 years). [3]
- It is thought that insulinoma is mediated by mTOR/P70S6K signaling pathway. Thus, inhibitors of mTOR (rapamycin) or dual PI3K/mTOR (NVP-BEZ2235) have become new drugs for treating insulinoma.
- Everolimus (an oral mTOR inhibitor) has a better glycemic control in people having an insulinoma.[4][5]
- Mitochondria play a key role in glucose and insulin coupling to assure insulin secretion after glucose stimulation in pancreatic β cells. Coupling is impaired due to abnormal mitochondrial function in β cells causing the death of the cell.[6] This mitochondrial function is regulated by YY1.[7]
- T372R mutation increases the transcription of YY1.[8]
- The progression to hypoglycemia is the result of decreased glucose synthesis rather than increased use due to the direct effect of insulin on the liver.[9]
- The neuroglycopenic symptoms appear eventually due to decreased blood glucose. Hypoglycemia stimulates catecholamine release which produces adrenergic symptoms.[10]
Genetics
- Insulinoma is transmitted in an autosomal dominant pattern when it is associated with MEN 1 syndrome.
- Genes involved in the pathogenesis of insulinoma include MEN1 gene. Loss of heterozygosity of MEN1 gene takes place on chromosome 11q13. [11]
Associated Conditions
The following conditions are associated with insulinomas:
- Pancreatic neuroendocrine tumors such as:[3]
- MEN 1
- Von Hippel-Lindau
- Neurofibromatosis type 1
Gross Pathology
- On gross pathology insulinoma is encapsulated and have a gray to red brown appearance.[12]
- They are usually small and solitary tumors, although there is a case report of a large (9 cm), pedunculated insulinoma and weighing more than 100 grams.[13]

- Almost all insulinomas are present throughout the pancreas and extrapancreatic ones causing hypoglycemia are rare (<2%)[15]
- Various other findings are noted on gross pathology are: [16]
- Size of the tumor
- Metastasis to lymph nodes
- Extrapancreatic involvement
- Distant metastasis
Microscopic Pathology
- On microscopic histopathological analysis, patterns like trabecular, gyriform, lobular and solid structures particularly with amyloid in fibrovascular stroma are characteristic findings of insulinoma.[17]
- It is also evaluated for the mitotic index (mitosis per 10 high power field) and immunohistochemistry staining by chromogranin A, synaptophysin, and Ki-67 index.[16]
- The structure of tumor cells observed under electron microscopy as:
- Group A characterized by abundant well-granulated typical β cells with trabecular arrangement.
- Group B as scarce well-granulated typical β cells and a medullary arrangement. [18]
-
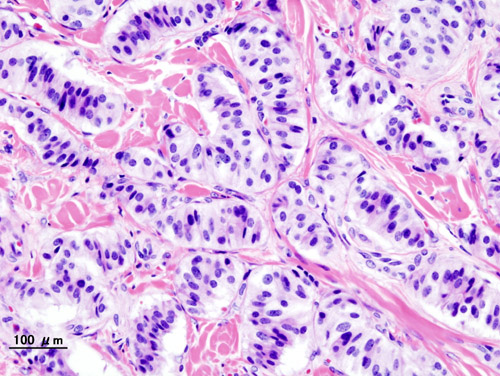 Histopathology of a pancreatic endocrine tumor (insulinoma). Source:https://librepathology.org/wiki/Neuroendocrine_tumour_of_the_pancreas[19]
-
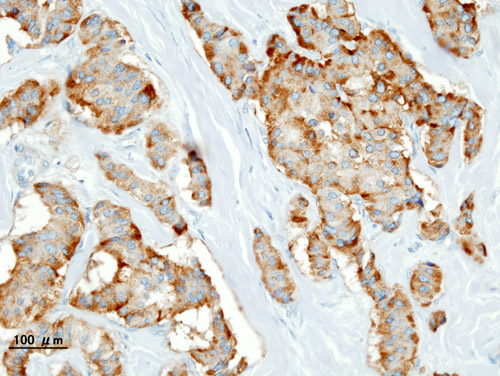 Histopathology of a pancreatic endocrine tumor (insulinoma). Chromogranin A immunostain. Source:https://librepathology.org/wiki/Neuroendocrine_tumour_of_the_pancreas[19]
-
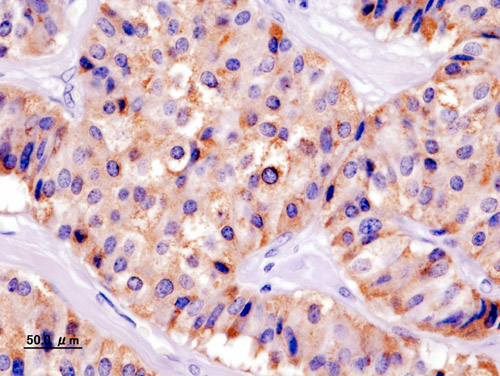 Histopathology of a pancreatic endocrine tumor (insulinoma). Insulin immunostain. Source:https://librepathology.org/wiki/Neuroendocrine_tumour_of_the_pancreas[19]


References
- ↑ AlJadir, Saadi (2015). “Insulinoma: Literature’s Review (Part 1)”. Endocrinology&Metabolism International Journal. 2 (3). doi:10.15406/emij.2015.02.00025. ISSN 2473-0815.
- ↑ Callender GG, Rich TA, Perrier ND (2008). “Multiple endocrine neoplasia syndromes”. Surg Clin North Am. 88 (4): 863–95, viii. doi:10.1016/j.suc.2008.05.001. PMID 18672144.
- ↑ 3.0 3.1 Service FJ, McMahon MM, O’Brien PC, Ballard DJ (1991). “Functioning insulinoma–incidence, recurrence, and long-term survival of patients: a 60-year study”. Mayo Clin Proc. 66 (7): 711–9. PMID 1677058.
- ↑ Kulke MH, Bergsland EK, Yao JC (2009). “Glycemic control in patients with insulinoma treated with everolimus”. N Engl J Med. 360 (2): 195–7. doi:10.1056/NEJMc0806740. PMID 19129539.
- ↑ Zhan HX, Cong L, Zhao YP, Zhang TP, Chen G, Zhou L; et al. (2012). “Activated mTOR/P70S6K signaling pathway is involved in insulinoma tumorigenesis”. J Surg Oncol. 106 (8): 972–80. doi:10.1002/jso.23176. PMID 22711648.
- ↑ Supale S, Li N, Brun T, Maechler P (2012). “Mitochondrial dysfunction in pancreatic β cells”. Trends Endocrinol Metab. 23 (9): 477–87. doi:10.1016/j.tem.2012.06.002. PMID 22766318.
- ↑ Cunningham JT, Rodgers JT, Arlow DH, Vazquez F, Mootha VK, Puigserver P (2007). “mTOR controls mitochondrial oxidative function through a YY1-PGC-1alpha transcriptional complex”. Nature. 450 (7170): 736–40. doi:10.1038/nature06322. PMID 18046414.
- ↑ Cao, Yanan; Gao, Zhibo; Li, Lin; Jiang, Xiuli; Shan, Aijing; Cai, Jie; Peng, Ying; Li, Yanli; Jiang, Xiaohua; Huang, Xuanlin; Wang, Jiaqian; Wei, Qing; Qin, Guijun; Zhao, Jiajun; Jin, Xiaolong; Liu, Li; Li, Yingrui; Wang, Weiqing; Wang, Jun; Ning, Guang (2013). “Whole exome sequencing of insulinoma reveals recurrent T372R mutations in YY1”. Nature Communications. 4. doi:10.1038/ncomms3810. ISSN 2041-1723.
- ↑ Rizza, R. A.; Haymond, M. W.; Verdonk, C. A.; Mandarino, L. J.; Miles, J. M.; Service, F. J.; Gerich, J. E. (1981). “Pathogenesis of Hypoglycemia in Insulinoma Patients: Suppression of Hepatic Glucose Production by Insulin”. Diabetes. 30 (5): 377–381. doi:10.2337/diab.30.5.377. ISSN 0012-1797.
- ↑ Abe T (1992). “[Letter from Alabama–Medicaid and Medicare]”. Kango. 44 (2): 135–40. PMID 1305178.
- ↑ Shin JJ, Gorden P, Libutti SK (2010). “Insulinoma: pathophysiology, localization and management”. Future Oncol. 6 (2): 229–37. doi:10.2217/fon.09.165. PMC 3498768. PMID 20146582.
- ↑ Lloyd, Ricardo (2010). Endocrine pathology : differential diagnosis and molecular advances. New York London: Springer. ISBN 978-1441910684.
- ↑ Mittendorf EA, Liu YC, McHenry CR (2005). “Giant insulinoma: case report and review of the literature”. J Clin Endocrinol Metab. 90 (1): 575–80. doi:10.1210/jc.2004-0825. PMID 15522939.
- ↑ Pancreatic insulinoma co-existing with gastric GIST in the absence of neurofibromatosis-1. World Journal of Surgical Oncology 2009, 7:18doi:10.1186/1477-7819-7-18, CC BY 2.0, Source: https://commons.wikimedia.org/w/index.php?curid=6686376
- ↑ Okabayashi T, Shima Y, Sumiyoshi T, Kozuki A, Ito S, Ogawa Y, Kobayashi M, Hanazaki K (2013). “Diagnosis and management of insulinoma”. World J. Gastroenterol. 19 (6): 829–37. doi:10.3748/wjg.v19.i6.829. PMC 3574879. PMID 23430217.
- ↑ 16.0 16.1 de Herder, Wouter W.; Niederle, Bruno; Scoazec, Jean-Yves; Pauwels, Stanislas; Klöppel, Günter; Falconi, Massimo; Kwekkeboom, Dik J.; Öberg, Kjel; Eriksson, Barbro; Wiedenmann, Bertram; Rindi, Guido; O’Toole, Dermot; Ferone, Diego (2007). “Well-Differentiated Pancreatic Tumor/Carcinoma: Insulinoma”. Neuroendocrinology. 84 (3): 183–188. doi:10.1159/000098010. ISSN 0028-3835.
- ↑ Lloyd, Ricardo (2010). Endocrine pathology : differential diagnosis and molecular advances. New York London: Springer. ISBN 978-1441910684.
- ↑ Berger M, Bordi C, Cüppers HJ, Berchtold P, Gries FA, Münterfering H; et al. (1983). “Functional and morphologic characterization of human insulinomas”. Diabetes. 32 (10): 921–31. PMID 6311653.
- ↑ 19.0 19.1 19.2 Neuroendocrine tumor of the pancreas. Libre Pathology. http://librepathology.org/wiki/index.php/Neuroendocrine_tumour_of_the_pancreas
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Causes
Overview
The cause of insulinoma has not been identified. To review risk factors for the development of insulinoma, click here.
Causes
There are no established causes of insulinoma but there is an association with MEN 1 syndrome and rarely with Von Hippel-Lindau disease, Neurofibromatosis-1 and Tuberous sclerosis. [1][2][3]
- To review risk factors for the development of insulinoma, click here.
References
- ↑ Service FJ, McMahon MM, O’Brien PC, Ballard DJ (1991). “Functioning insulinoma–incidence, recurrence, and long-term survival of patients: a 60-year study”. Mayo Clin Proc. 66 (7): 711–9. PMID 1677058.
- ↑ Jensen RT, Berna MJ, Bingham DB, Norton JA (2008). “Inherited pancreatic endocrine tumor syndromes: advances in molecular pathogenesis, diagnosis, management, and controversies”. Cancer. 113 (7 Suppl): 1807–43. doi:10.1002/cncr.23648. PMC 2574000. PMID 18798544.
- ↑ Beisang D, Forlenza GP, Luquette M, Sarafoglou K (2017). “Sporadic Insulinoma Presenting as Early Morning Night Terrors”. Pediatrics. doi:10.1542/peds.2016-2007. PMID 28562256.
Editor-In-Chief:
C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Differentiating Insulinoma from other Diseases

Overview
Insulinoma must be differentiated from other diseases that cause features of hypoglycemia like altered mental status/confusion, profuse sweating and visual disturbances (blurring/diplopia). These are classified on the basis of laboratory findings into exogenous insulin, oral hypoglycemic agents (e.g. Sulphonylureas), Nesidioblastosis, insulin autoimmune hypoglycemia.
Differentiating insulinoma from other Diseases
Insulinoma must be differentiated from other diseases that cause features of hypoglycemia. These are classified on the basis of laboratory findings.
Differentials for Hypoglycemia on the basis of Laboratory findings:[1]
| Diagnoses | Laboratory Findings differentiating among causes of Hypoglycemia | |||||||
|---|---|---|---|---|---|---|---|---|
| S.Glucose (mg/dL) |
C Peptide (pmol/L) | S.Insulin (μU/mL) | S.Proinsulin (pmol/L) |
S. Beta hydroxybutyrate | Glucose increase after glucagon(mg/dL) | Oral Hypoglycemic agent | Antibodies to Insulin | |
| Normal/Fasting | <55 | <200 | <3 | <5 | >2.7 | <25 | – | – |
| Exogenous Insulin | <55 | <200 | >>3 | <5 | ≤2.7 | >25 | – | – |
| Insulinoma | <55 | ≥200 | ≥3 | ≥5 | ≤2.7 | >25 | – | – |
| Nesidioblastosis | ||||||||
| Post gastric bypass hypoglycemia (PGPH) | ||||||||
| Insulin autoimmune hypoglycemia | <55 | >>200‡ | >>3 | >>5‡ | ≤2.7 | >25 | – | + |
| Oral hypoglycemic agent | <55 | ≥200 | ≥3 | ≥5 | ≤2.7 | >25 | + | – |
| IGF¤ | <55 | <200 | <3 | <5 | ≤2.7 | >25 | – | – |
|
‡ Free C-peptide and proinsulin concentrations are low | ||||||||
Differentiating hypoglycemia from other diseases that cause autonomic hyperactivity symptoms :
| Disease | Clinical Manifestation | Investigations | ||||
|---|---|---|---|---|---|---|
| Symptoms | Signs | |||||
| Palpitations | Fever | Sweating | Headache | |||
| Hypoglycemia | + | – | + | + |
|
|
| Anxiety disorders | + | – | + | + |
|
|
| Pheochromocytoma | + | + | + | + |
|
|
| Arrhythmia | + | – | – | – |
|
|
| Hyperthyroidism | + | + | + | + |
|
|
References
- ↑ Cryer PE, Axelrod L, Grossman AB, Heller SR, Montori VM, Seaquist ER; et al. (2009). “Evaluation and management of adult hypoglycemic disorders: an Endocrine Society Clinical Practice Guideline”. J Clin Endocrinol Metab. 94 (3): 709–28. doi:10.1210/jc.2008-1410. PMID 19088155.
- ↑ Lenders JW, Pacak K, Walther MM, Linehan WM, Mannelli M, Friberg P; et al. (2002). “Biochemical diagnosis of pheochromocytoma: which test is best?”. JAMA. 287 (11): 1427–34. PMID 11903030.
- ↑ Bravo EL (1991). “Pheochromocytoma: new concepts and future trends”. Kidney Int. 40 (3): 544–56. PMID 1787652.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Epidemiology and Demographics
Overview
The incidence of insulinoma is approximately 0.1-0.4 per 100,000 individuals that constitute 1-2% of all pancreatic neoplasms. The female to male ratio is approximately 3:2. There is no regional predisposition.
Epidemiology and Demographics
Incidence
- The incidence of insulinoma is approximately 0.1-0.4 per 100,000 individuals that constitute 1-2% of all pancreatic neoplasms.[1][2]
Age
- Patients of all age groups may develop insulinoma.
- Insulinoma commonly affects individuals 40-60 years of age.
Race
- There is no racial predilection to insulinoma.
Gender
- Females (60-75%) are more commonly affected by insulinoma than males. The female to male ratio is approximately 3:2.[2]
Region
- There is no regional predisposition but it was described according to local studies. One of the best studies ever conducted for insulinoma, by Mayo clinic, showed the incidence of insulinoma in residents of Olmsted County, Minnesota over the time frame of 60 years.
References
- ↑ Okabayashi T, Shima Y, Sumiyoshi T, Kozuki A, Ito S, Ogawa Y, Kobayashi M, Hanazaki K (2013). “Diagnosis and management of insulinoma”. World J. Gastroenterol. 19 (6): 829–37. doi:10.3748/wjg.v19.i6.829. PMC 3574879. PMID 23430217.
- ↑ 2.0 2.1 Service FJ, McMahon MM, O’Brien PC, Ballard DJ (1991). “Functioning insulinoma–incidence, recurrence, and long-term survival of patients: a 60-year study”. Mayo Clin. Proc. 66 (7): 711–9. PMID 1677058.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Risk Factors
Overview
Common risk factors in the development of insulinoma include female gender, age group 40-60 years, MEN1 syndrome, Von Hippel-Lindau disease, and neurofibromatosis 1.
Risk Factors
Common Risk Factors
Common risk factors in the development of insulinoma include:
- Gender
- Age
- People who are in the age range of 40-60 years.
- Genetics
- Persons with family history of pancreatic neuroendocrine tumors are at higher risk of developing insulinomas. [1]
- People with associated Multiple endocrine neoplasia type 1 syndrome (MEN 1).[1][2][3][4]
Less Common Risk Factors
Less common risk factors in the development of insulinoma include:
- Von Hippel-Lindau disease
- Neurofibromatosis type 1 [1][4]
References
- ↑ 1.0 1.1 1.2 Zhan HX, Cong L, Zhao YP, Zhang TP, Chen G (2013). “Risk factors for the occurrence of insulinoma: a case-control study”. Hepatobiliary Pancreat Dis Int. 12 (3): 324–8. PMID 23742779.
- ↑ Service FJ, McMahon MM, O’Brien PC, Ballard DJ (1991). “Functioning insulinoma–incidence, recurrence, and long-term survival of patients: a 60-year study”. Mayo Clin Proc. 66 (7): 711–9. PMID 1677058.
- ↑ Boukhman MP, Karam JH, Shaver J, Siperstein AE, Duh QY, Clark OH (1998). “Insulinoma–experience from 1950 to 1995”. West J Med. 169 (2): 98–104. PMC 1305178. PMID 9735690.
- ↑ 4.0 4.1 “Insulinoma – Health Encyclopedia – University of Rochester Medical Center”.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Screening
Overview
There is insufficient evidence to recommend routine screening for insulinoma.
Screening
- There is insufficient evidence to recommend routine screening for insulinoma.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Natural History, Complications and Prognosis
Overview
If left untreated, patients with insulinoma may progress to develop seizures, coma and even death. Prognosis is generally excellent for benign insulinoma after the removal of the tumor. Recurrence rates are higher in those associated with MEN1 syndrome.
Natural History, Complications, and Prognosis
Natural History
- The symptoms of insulinoma are found in any age group and start with neuroglycopenic symptoms such as altered mental status, visual disturbances, confusion and adrenergic symptoms such as profuse sweating, palpitations and tremors.
- If left untreated, hypoglycemic episodes progresses in frequency, although the tumor size remains small. [1]
Complications
- Common complications of insulinoma are due to hypoglycemia include:[2]
Prognosis
- 90% insulinomas are benign and they are generally cured after the removal of the tumor, so benign insulinoma is associated with the most favorable prognosis. [3]
- The prognosis varies with the malignant potential of the tumor; grade 1 and 2 tumor have the most favorable prognosis.
- Malignant insulinomas: In a study of 10 patients, the first 4 who presented with lymph node metastasis after surgical excision, maintained a prolonged tumor-free survival. The next four patients presented with metastasis to the liver, which appeared years after the initial diagnosis and presumed curative surgery. One patient presented with a large α-fetoprotein-secreting liver mass. Finally, 9 of the 10 patients had a prolonged survival.[4]
References
- ↑ “Natural History of Untreated Insulinoma over a Course of 7 Years : Endocrine Neoplasia: Tumorigenesis and Therapeutics”.
- ↑ Graves TD, Gandhi S, Smith SJ, Sisodiya SM, Conway GS (2004). “Misdiagnosis of seizures: insulinoma presenting as adult-onset seizure disorder”. J Neurol Neurosurg Psychiatry. 75 (8): 1091–2. doi:10.1136/jnnp.2003.029249. PMC 1739168. PMID 15258206.
- ↑ Service FJ, McMahon MM, O’Brien PC, Ballard DJ (1991). “Functioning insulinoma–incidence, recurrence, and long-term survival of patients: a 60-year study”. Mayo Clin Proc. 66 (7): 711–9. PMID 1677058.
- ↑ Hirshberg B, Cochran C, Skarulis MC, Libutti SK, Alexander HR, Wood BJ; et al. (2005). “Malignant insulinoma: spectrum of unusual clinical features”. Cancer. 104 (2): 264–72. doi:10.1002/cncr.21179. PMC 4136659. PMID 15937909.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]
Diagnosis
Diagnosis
Staging | History and Symptoms | Physical Examination | Laboratory Findings | CT | MRI | Ultrasound | Other Imaging Findings | Other Diagnostic Studies
Treatment
Treatment
Medical Therapy | Surgery | Primary Prevention | Secondary Prevention | Cost-Effectiveness of Therapy | Future or Investigational Therapies
Related Chapters
Related Chapters
Template:Tumor morphology de:Insulinom he:אינסולינומה nl:Insulinoom fi:Insulinooma
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Amandeep Singh M.D.[2]