

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Burkitt lymphoma
Introduction
For patient information click here
Synonyms and keywords:: Burkitt’s tumor; Burkitt lymphoma; Burkitt’s type non-Hodgkin’s lymphoma; Malignant lymphoma, Burkitt’s type
Overview
Overview
Burkitt’s lymphoma (“Burkitt’s tumor”, or “Malignant lymphoma, Burkitt’s type”) is a cancer of the lymphatic system (in particular, B lymphocytes). Burkitt’s lymphoma was first described by Denis Parsons Burkitt, a surgeon, in 1958 while working in equatorial Africa. Burkitt’s lymphoma may be classified according to WHO classification into 3 clinical variants: endemic Burkitt’s lymphoma, sporadic Burkitt’s lymphoma, and immunodeficiency-associated Burkitt’s lymphoma. Gene involved in the pathogenesis of Burkitt’s lymphoma includes c-myc. On gross pathology, ulceration and discharge are characteristic findings of Burkitt’s lymphoma. On microscopic histopathological analysis, “starry sky” appearance is characteristic finding of Burkitt’s lymphoma. There are no established causes for Burkitt’s lymphoma. Burkitt’s lymphoma must be differentiated from other diseases such as Hodgkin’s lymphoma, diffuse large B cell lymphoma, follicular lymphoma, Mucosa-Associated Lymphatic Tissue lymphoma (MALT), small cell lymphocytic lymphoma, and mantle cell lymphoma (MCL). Burkitt’s lymphoma is a common disease that tends to affect children or young adults. Males are more commonly affected with Burkitt’s lymphoma than females. Burkitt’s lymphoma usually affects individuals of the African race. Common risk factors in the development of Burkitt’s lymphoma may be HIV/AIDS and post-transplant immunosuppression. According to the the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for Burkitt’s lymphoma. The prognosis varies with the age, children have the most favorable prognosis. Burkitt’s lymphoma in children is associated with a 5 year survival rate of 90%. The presence of metastasis in bone marrow or CNS is associated with a particularly poor prognosis among patients with Burkitt’s lymphoma. According to the Murphy staging system, there are four stages of Burkitt’s lymphoma based on the number of nodes and extra nodal involvement. Laboratory tests for Burkitt’s lymphoma include complete blood count (CBC), blood chemistry studies, immuno histochemistry, HIV blood test, flow cytometric analysis, and cytogenetics. Chest and knee x ray may be helpful in the diagnosis of Burkitt’s lymphoma. CT and MRI may be helpful in the diagnosis of Burkitt’s lymphoma. Lymph node or extra nodal tissue biopsy is diagnostic of Burkitt’s lymphoma. PET and bone scan may be helpful in the diagnosis of Burkitt’s lymphoma. Other diagnostic studies for the diagnosis of Burkitt’s lymphoma include bone marrow biopsy and spinal fluid examination. The predominant therapy for Burkitt’s lymphoma is chemotherapy. Adjunctive immunotherapy and stem cell transplantation may be required. Surgical intervention is not recommended for the management of Burkitt’s lymphoma.
Historical Perspective
Burkitt’s lymphoma was first described by Denis Parsons Burkitt, a surgeon, in 1958 while working in equatorial Africa.
Classification
Burkitt’s lymphoma may be classified according to WHO classification into 3 clinical variants: endemic Burkitt’s lymphoma, sporadic Burkitt’s lymphoma, and immunodeficiency-associated Burkitt’s lymphoma.
Pathophysiology
The c-myc gene involved in the pathogenesis of Burkitt’s lymphoma. On gross pathology, ulceration and discharge are characteristic findings of Burkitt’s lymphoma. On microscopic histopathological analysis, “starry sky” appearance is a characteristic finding of Burkitt’s lymphoma.
Causes
There are no established causes for Burkitt’s lymphoma.
Differential diagnosis
Burkitt’s lymphoma must be differentiated from other diseases such as Hodgkin’s lymphoma, diffuse large B cell lymphoma, follicular lymphoma, Mucosa-Associated Lymphatic Tissue lymphoma (MALT), small cell lymphocytic lymphoma, and mantle cell lymphoma (MCL).
Epidemiology and Demographics
Burkitt’s lymphoma is a common disease that tends to affect children or young adults. Males are more commonly affected with Burkitt’s lymphoma than females. Burkitt’s lymphoma usually affects individuals of the African race.
Risk Factors
Common risk factors in the development of Burkitt’s lymphoma may be HIV/AIDS and post-transplant immunosuppression.
Screening
According to the the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for Burkitt’s lymphoma.
Prognosis
The prognosis varies with the age, children have the most favorable prognosis. Burkitt’s lymphoma in children is associated with a 5 year survival rate of 90%. The presence of metastasis in bone marrow or CNS is associated with a particularly poor prognosis among patients with Burkitt’s lymphoma.
Diagnosis
Staging
According to the Murphy staging system, there are four stages of Burkitt’s lymphoma based on the number of nodes and extra nodal involvement.
Laboratory Findings
Laboratory tests for Burkitt’s lymphoma include complete blood count (CBC), blood chemistry studies, immuno histochemistry, HIV blood test, flow cytometric analysis, and cytogenetics.
X Ray Findings
Chest and knee x ray may be helpful in the diagnosis of Burkitt’s lymphoma.
CT
Chest, abdomen, and pelvis CT scan may be helpful in the diagnosis of Burkitt’s lymphoma.
MRI
MRI may be helpful in the diagnosis of Burkitt’s lymphoma.
Biopsy
Lymph node or extra nodal tissue biopsy is diagnostic of Burkitt’s lymphoma.
Other Imaging Studies
PET and bone scan may be helpful in the diagnosis of Burkitt’s lymphoma.
Other diagnostic studies
Other diagnostic studies for the diagnosis of Burkitt’s lymphoma include bone marrow biopsy and spinal fluid examination.
Treatment
Medical Therapy
The predominant therapy for Burkitt’s lymphoma is chemotherapy. Adjunctive immunotherapy and stem cell transplantation may be required.
Surgery
Surgical intervention is not recommended for the management of Burkitt’s lymphoma.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2]
Historical Perspective
Overview
Burkitt’s lymphoma was first discovered by Denis Parsons Burkitt, an Irish surgeon, in 1958 while working in Africa.
Historical Perspective
- Burkitt’s lymphoma was first discovered by Denis Parsons Burkitt, an Irish surgeon, in 1958 while working in Africa.[1]
- In 1961 Burkitt and O’Connor detailed the features of the clinical syndrome known as Burkitt’s lymphoma. Soon afterward, Wright discovered that this lymphoma can be distinguished from other forms of lymphomas based on key histopathological features.[2]
References
- ↑ Burkitt D (1958). “A sarcoma involving the jaws in African children”. The British journal of surgery. 46 (197): 218–23. doi:10.1002/bjs.18004619704. PMID 13628987.
- ↑ Ortiz-Hidalgo C (1994). “A short history of Hodgkin’s disease and Burkitt’s lymphoma”. Am J Clin Pathol. 101 (4 Suppl 1): S27–33. PMID 8154453.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2], Kamal Akbar, M.D.[3]
Classification
Overview
Burkitt’s lymphoma may be classified according to the World Health Organization (WHO) classification into 3 clinical variants. The clinical variants are endemic Burkitt’s lymphoma, sporadic Burkitt’s lymphoma, and immunodeficiency-associated Burkitt’s lymphoma.
Classification
Burkitt’s lymphoma may be classified according to WHO classification into 3 clinical variants:
- Endemic Burkitt’s lymphoma [1]
- Sporadic Burkitt’s lymphoma[2]
- Immunodeficiency-associated Burkitt’s lymphoma[3]
It is almost impossible to differentiate these three clinical variants based on histology (i.e. microscopic appearance) or immunophenotype.
| Name | Description |
|---|---|
| Endemic Burkitt’s lymphoma
(African Burkitt’s lymphoma) |
|
| Sporadic Burkitt’s lymphoma
(Non-African or Non-endemic Burkitt’s lymphoma) |
|
| Immunodeficiency-associated Burkitt’s lymphoma |
|
References
- ↑ Tao Q, Robertson KD, Manns A, Hildesheim A, Ambinder RF (1998). “Epstein-Barr virus (EBV) in endemic Burkitt’s lymphoma: molecular analysis of primary tumor tissue”. Blood. 91 (4): 1373–81. PMID 9454768.
- ↑ Ng JY, Thompson RJ, Lam A, Nigam S (2018). “Sporadic Burkitt’s lymphoma masquerading as an intussuscepted Meckel’s diverticulum in a 9-year-old child”. BMJ Case Rep. 2018. doi:10.1136/bcr-2018-224333. PMID 30042102.
- ↑ Linke-Serinsöz E, Fend F, Quintanilla-Martinez L (2017). “Human immunodeficiency virus (HIV) and Epstein-Barr virus (EBV) related lymphomas, pathology view point”. Semin Diagn Pathol. 34 (4): 352–363. doi:10.1053/j.semdp.2017.04.003. PMID 28506687.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2]
Pathophysiology
Overview
The c-myc gene is involved in the pathogenesis of Burkitt’s lymphoma. On gross pathology, ulceration and discharge are characteristic findings of Burkitt’s lymphoma. On microscopic histopathological analysis, “starry sky” appearance is a characteristic finding of Burkitt’s lymphoma.
Pathology
Burkitt’s lymphoma is an aggressive and rapidly growing tumor.[1]. It can present in a wide variety of locations which include:
- Head and neck (facial bones and Waldeyer’s ring)
- Pleural space (~70%)
- Gastrointestinal tract, especially ileocaecal region
- Mesentery, peritoneum, and retroperitoneum
- Kidneys
- Gonads (~75%)
Genetics
Translocation of chromosome 8 myc locus with 3 possible partners (accounting for 90% of translocations):[2]
- The Ig heavy chain region on chromosome 14: t(8;14)
- The kappa light chain locus on chromosome 2: t(2;8)
- The lambda light chain locus on chromosome 22: t(8;22)
- WHO committees suggest the following:
- If morphologic features are intermediate, diagnosis of Burkitt’s should only be made if the Ki-67 fraction of viable cells is at least 99 percent
- If morphologic features suggest diffuse large B cell lymphoma, but have with a high proliferation fraction or t(8;14), they should be classified as diffuse large B cell lymphoma
Gene targets
- Unique genetic alterations promote cell survival in Burkitt’s lymphoma, distinct from other types of lymphoma[3]
- These TCF3 and ID3 gene mutations in Burkitt’s correspond to a cell survival pathway that may be found to be amenable to targeted therapy.[4]
MicroRNA expression
- In 2014, it was described that short non-coding RNAs named microRNAs (miRNAs) have important functions in lymphoma biology
- In malignant B cells miRNAs participate in pathways fundamental to B cell development like B cell receptor (BCR) signaling, B cell migration/adhesion, cell-cell interactions in immune niches, and the production and class-switching of immunoglobulins[5]
- MiRNAs influences B cells in the following manner:[5]
- Maturation
- Generation of marginal zone
- Follicular
- Plasma
- Memory B cells
Immunohistochemistry
The tumor cells in Burkitt lymphoma generally strongly express markers of B cell differentiation and they are the following:[6]
- (CD19
- CD20
- CD22)
- CD10
- BCL6
- The tumor cells are generally negative for BCL2 and TdT. The high mitotic activity of Burkitt’s lymphoma is confirmed by nearly 100% of the cells staining positive for Ki67.[7]
Malignant B cell characteristics
Malignant B cells have identical DNA recombinations of the V(D)J region of the immunoglobin genes and there characteristics are the following: [8]
- This means that no increase in specificity of antibody molecules is occurring in the malignant cells
- These malignant cells are thus clonal populations and can be assayed for by using DNA probes specific for the regions where recombination is expected
- Normal DNA will be characterized by two high concentration of identical germ line DNA V(D)J regions and endless, likely undetectable, non-germline Ig V(D)J DNA
- Lymphoma cells have an additional high concentration of V(D)J DNA that is unlike the germ line, indicating clonal populations of B Cells that are not undifferentiated B cells (germ line DNA cells)
- Assays typically use the process of electrophoresis and southern blot analysis to determine the existence of these characteristics
Gross Pathology
-
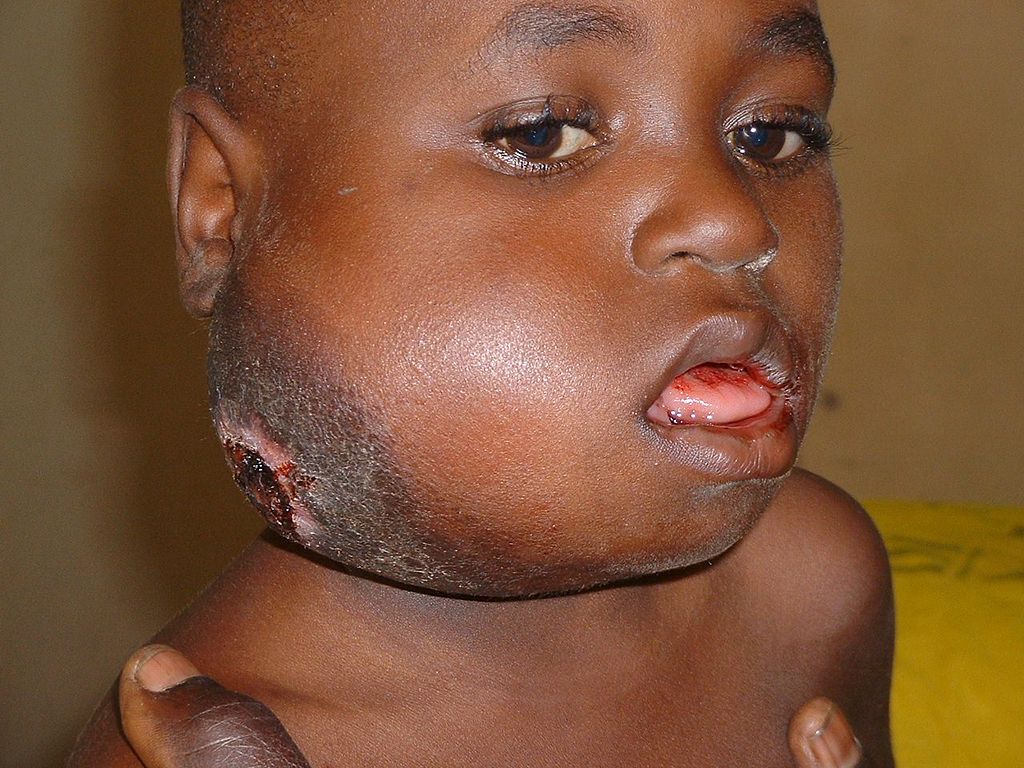 Seven-year-old Nigerian boy with a several-month history of jaw swelling which had been treated with antibiotics: The tumor was ulcerated and draining[9]
-
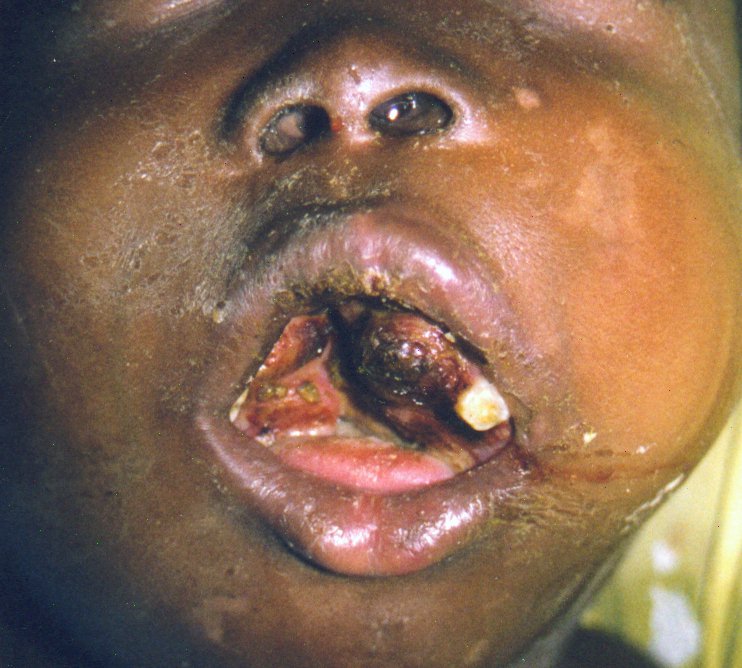 Picture of a mouth of a patient with Burkitt lymphoma showing disruption of teeth and partial obstruction of airway[9]


Microscopic Pathology
On microscopic histopathological analysis, characteristic findings of Burkitt’s lymphoma include:[10]
- Medium-sized (~1.5-2x the size of a RBC) with uniform size (“monotonous”) — key feature (i.e. tumor nuclei size similar to that of histiocytes or endothelial cells)
- Round nucleus
- Small nucleoli
- Relatively abundant cytoplasm (basophilic)
- Brisk mitotic rate and apoptotic activity
- Cellular outline usually appears squared off
- “Starry-sky pattern”:
- The stars in the pattern are tingible-body macrophages (macrophages containing apoptotic tumor cells)
- The tumour cells are the sky
Video
{{#ev:youtube|CwsQ-wIbbK8}}
References
- ↑ Burkitt lymphoma. Radiopedia. http://radiopaedia.org/articles/burkitt-lymphoma Accessed on October,5 2015
- ↑ Burkitt’s Lymphoma. Wikibooks. https://en.wikibooks.org/wiki/Radiation_Oncology/NHL/Burkitt_lymphoma#Pathology Accessed on October,5 2015
- ↑ “NIH study shows Burkitt lymphoma is molecularly distinct from other lymphomas”. National Cancer Institute.
- ↑ Staudt L, et al. Burkitt Lymphoma Pathogenesis and Therapeutic Targets from Structural and Functional Genomics. Nature. August 12, 2012 doi:10.1038/nature11378
- ↑ 5.0 5.1 Musilova, K; Mraz, M (2014). “MicroRNAs in B cell lymphomas: How a complex biology gets more complex”. Leukemia. doi:10.1038/leu.2014.351. PMID 25541152.
- ↑ Chuang, Shih-Sung; Ye, Hongtao; Du, Ming-Qing; Lu, Chin-Li; Dogan, Ahmet; Hsieh, Pin-Pen; Huang, Wan-Ting; Jung, Yun-Chih (2007). “Histopathology and Immunohistochemistry in Distinguishing Burkitt Lymphoma From Diffuse Large B-Cell Lymphoma With Very High Proliferation Index and With or Without a Starry-Sky Pattern”. American Journal of Clinical Pathology. 128 (4): 558–564. doi:10.1309/EQJR3D3V0CCQGP04. ISSN 0002-9173.
- ↑ Steven H Swerdlow (2008). WHO classification of tumours of haematopoietic and lymphoid tissues. World Health Organization classification of tumours. Lyon, France : International Agency for Research on Cancer. ISBN 978-92-832-2431-0.
- ↑ Ferry, J. A. (2006). “Burkitt’s Lymphoma: Clinicopathologic Features and Differential Diagnosis”. The Oncologist. 11 (4): 375–383. doi:10.1634/theoncologist.11-4-375. ISSN 1083-7159.
- ↑ 9.0 9.1 Burkitt’s lymphoma. Wikipedia. https://en.wikipedia.org/wiki/Burkitt%27s_lymphomaAccessed on October 5, 2015
- ↑ Bellan C, Lazzi S, De Falco G, Nyongo A, Giordano A, Leoncini L (2003). “Burkitt’s lymphoma: new insights into molecular pathogenesis”. J. Clin. Pathol. 56 (3): 188–92. PMC 1769902. PMID 12610094. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Shivali Marketkar, M.B.B.S. [2] Sowminya Arikapudi, M.B,B.S. [3], Kamal Akbar, M.D.[4]
Causes
Overview
There are no established causes for Burkitt’s lymphoma.
Causes
There are no established causes for Burkitt’s lymphoma.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Soumya Sachdeva, Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2]
Differentiating Burkitt’s lymphoma from other Diseases

Overview
Burkitt’s lymphoma must be differentiated from other diseases such as Hodgkin’s lymphoma, diffuse large B cell lymphoma, follicular lymphoma, Mucosa-Associated Lymphatic Tissue lymphoma (MALT), small cell lymphocytic lymphoma, and mantle cell lymphoma (MCL).
Differentiating Burkitt’s lymphoma from other Diseases
Burkitt’s lymphoma must be differentiated from other diseases such as:[1]
- Diffuse large B cell lymphoma
- Hodgkin’s lymphoma
- Follicular lymphoma
- Mucosa-Associated Lymphatic Tissue lymphoma (MALT)
- Small cell lymphocytic lymphoma
- Mantle cell lymphoma (MCL)
Differential Diagnosis of Sporadic Burkitt’s Lymphoma
| S.No. | Disease | Symptoms | Signs | Diagnosis | Comments | |||||
|---|---|---|---|---|---|---|---|---|---|---|
| Abdominal Pain | Hematuria | Headache | Abdominal mass | Abdominal tenderness | Ultrasonography | CT scan | Histology | |||
| 1. | Wilms tumor | + | + | – | + | + |
|
|
|
|
| 2. | Renal cell carcinoma | + | + | +/- | + | – |
|
Both CT and MRI may be used to detect neoplastic masses that may define renal cell carcinoma or metastasis of the primary cancer. CT scan and use of intravenous (IV) contrast is generally used for work-up and follow-up of patients with renal cell carcinoma. | The histological pattern of renal cell carcinoma depends whether it is papillary, chromophobe or collecting duct renal cell carcinoma. | |
| 3. | Rhabdoid kidney disease | + | + | – | + | – |
|
|
|
|
| 4. | Polycystic kidney disease | + | + | + (from hypertension) | + | – |
Ultrasound may be helpful in the diagnosis of polycystic kidney disease. Findings on an ultrasound diagnostic of polycystic kidney disease include:[6][7] |
Renal CT scan may be helpful in the diagnosis of polycystic kidney disease. Findings on CT scan diagnostic of ADPKD include:
|
||
| 5. | Pheochromocytoma | – | – | + (as a part of the hypertension paroxysm) | – | – |
|
The following findings may be observed on CT scan:[12]
|
|
|
| 6. | Burkitt lymphoma | +/- (in non-endemic or sporadic form of the disease) | – | – | – | – |
|
|
|
|
| 7. | Intussusception | + | – | – | +/- | + |
|
|
|
|
| 8. | Hydronephrosis | + | +/- | – | – | + (CVA tenderness in case of pyelonephritis) |
|
|
|
|
| 9. | Dysplastic kidney | N/A | N/A | N/A | N/A | N/A |
MCDK is usually diagnosed by ultrasound examination before birth.
|
|
||
| 10. | Pediatric Neuroblastoma | + | – | – | +/- | +/- |
|
|
|
|
| 11. | Pediatric Rhabdomyosarcoma | + | +/- | +/- | – | +/- | On CT scan, rhabdomyosarocma is characterized by:
|
|
||
| 12. | Mesoblastic nephroma | + | + | – | + | – |
|
|
Classic mesoblastic nephroma
Cellular mesoblastic nephroma
Mixed mesoblastic nephroma
|
Most common renal tumor that occurs in 1st month of life |
Differential Diagnosis of Endemic Burkitt’s Lymphoma
Endemic Burkitt’s lymphoma typically presents as a cervico-facial mass and must be differentiated from other diseases that may present as a cervico-facial mass such as salivary glands tumors, sialolithiasis, human immunodeficiency virus, radiation, and systemic diseases such as, sarcoidosis, and sjögren’s syndrome.[25][26][27][28][29][30][31][32]
| Diseases | Symptoms and sign | Laboratory Findings | Other Findings | |||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Onset | Unilateral/Bilateral | Pain | Swelling | Tenderness | Purulent discharge | Common site of involvement | ESR | Leukocytosis | ||
| Sialolithiasis | Acute | Unilateral | + | + | + | – | Submandibular gland | ↑/NL | ↑/NL | Radio-opaque in X-ray |
| Acute bacterial sialadenitis | Acute | Unilateral | + | + | + | + | Parotid | ↑ | ↑ | Other sign of infection may be present |
| Chronic bacterial sialadenitis | Chronic | Unilateral | + | + | – | +/- | Parotid | ↑ | ↑ | Other sign of infection may be present |
| Viral sialadenitis | Acute | Bilateral | + | + | + | – | Parotid | ↑ | ↑ | Coryza symptoms |
| Human immunodeficiency virus | Acute | Bilateral | + | + | – | – | Parotid | NL | NL | Other systemic findings of HIV/ check ELISA |
| Radiation sialadenitis | Acute | Unilateral | + | + | + | – | Depends on the treatment field | NL | NL | History of radiation in the salivary gland site |
| Salivary gland tumors | Subacute | Unilateral | – | + | – | – | Parotid | ↑/NL | ↑/NL | Advance age |
| Sarcoidosis | Gradual | Bilateral | – | + | – | – | Parotid | ↑ | ↑ | Systemic findings in other organs |
| Sjögren’s syndrome | Gradual | Bilateral | +/- | + | – | – | Parotid or submandibular glands | ↑/NL | ↑/NL | Dry eye/dry mouth |
| Malnutrition | Gradual | Bilateral | +/- | + | – | – | Parotid | NL | NL | Systemic findings in other organs |
Differentials Based on Cell Surface Markers
Based on the expression of cell surface markers, the table below differentiates Burkitt’s lymphoma from other diseases that cause similar clinical presentations:[33]
| Differential Diagnosis | Surface Immunoglobulin | CD5 | CD22/FMC7 | CD23 | CD79b | CD103 |
|---|---|---|---|---|---|---|
|
Chronic lymphocytic leukemia |
Weakly positive |
Positive |
Negative |
Positive |
Negative |
Positive/Negative |
|
Strongly positive |
Negative |
Positive |
Negative |
Positive |
Negative | |
|
Strongly positive |
Negative |
Positive |
Negative |
Positive/Negative |
Positive | |
|
Positive |
Positive |
Strongly positive |
Negative |
Strongly positive |
Negative | |
|
Strongly positive |
Negative |
Positive |
Negative |
Strongly positive |
Negative |
References
- ↑ Chen M, Yang JL, Zhao S, Liu WP, Li GD, Ye YX; et al. (2018). “[Diagnostic and therapeutic values of interphase fluorescence in situ hybridization in B-cell lymphomas: a clinicopathologic analysis of 604 cases]”. Zhonghua Bing Li Xue Za Zhi. 47 (12): 920–925. doi:10.3760/cma.j.issn.0529-5807.2018.12.005. PMID 30522172.
- ↑ Hartman DS, Sanders RC (April 1982). “Wilms’ tumor versus neuroblastoma: usefulness of ultrasound in differentiation”. J Ultrasound Med. 1 (3): 117–22. PMID 6152936.
- ↑ De Campo JF (1986). “Ultrasound of Wilms’ tumor”. Pediatr Radiol. 16 (1): 21–4. PMID 3003660.
- ↑ Cahan LD (1985). “Failure of encephalo-duro-arterio-synangiosis procedure in moyamoya disease”. Pediatr Neurosci. 12 (1): 58–62. PMID 4080660.
- ↑ Jolly RD, Stellwagen E, Babul J, Vodkaĭlo LV, Titov VL, Moldomusaev DM, Maianskiĭ AN (November 1975). “Mannosidosis of Angus Cattle: a prototype control program for some genetic diseases”. Adv Vet Sci Comp Med. 19 (23): 1–21. PMID 1978.
- ↑ Chapman AB, Devuyst O, Eckardt KU, Gansevoort RT, Harris T, Horie S, Kasiske BL, Odland D, Pei Y, Perrone RD, Pirson Y, Schrier RW, Torra R, Torres VE, Watnick T, Wheeler DC (July 2015). “Autosomal-dominant polycystic kidney disease (ADPKD): executive summary from a Kidney Disease: Improving Global Outcomes (KDIGO) Controversies Conference”. Kidney Int. 88 (1): 17–27. doi:10.1038/ki.2015.59. PMC 4913350. PMID 25786098.
- ↑ Pei Y, Obaji J, Dupuis A, Paterson AD, Magistroni R, Dicks E, Parfrey P, Cramer B, Coto E, Torra R, San Millan JL, Gibson R, Breuning M, Peters D, Ravine D (January 2009). “Unified criteria for ultrasonographic diagnosis of ADPKD”. J. Am. Soc. Nephrol. 20 (1): 205–12. doi:10.1681/ASN.2008050507. PMC 2615723. PMID 18945943.
- ↑ Stavrou C, Koptides M, Tombazos C, Psara E, Patsias C, Zouvani I, Kyriacou K, Hildebrandt F, Christofides T, Pierides A, Deltas CC (October 2002). “Autosomal-dominant medullary cystic kidney disease type 1: clinical and molecular findings in six large Cypriot families”. Kidney Int. 62 (4): 1385–94. doi:10.1111/j.1523-1755.2002.kid581.x. PMID 12234310.
- ↑ Bleyer AJ, Kmoch S, Antignac C, Robins V, Kidd K, Kelsoe JR, Hladik G, Klemmer P, Knohl SJ, Scheinman SJ, Vo N, Santi A, Harris A, Canaday O, Weller N, Hulick PJ, Vogel K, Rahbari-Oskoui FF, Tuazon J, Deltas C, Somers D, Megarbane A, Kimmel PL, Sperati CJ, Orr-Urtreger A, Ben-Shachar S, Waugh DA, McGinn S, Bleyer AJ, Hodanová K, Vylet’al P, Živná M, Hart TC, Hart PS (March 2014). “Variable clinical presentation of an MUC1 mutation causing medullary cystic kidney disease type 1”. Clin J Am Soc Nephrol. 9 (3): 527–35. doi:10.2215/CJN.06380613. PMC 3944763. PMID 24509297.
- ↑ Faguer S, Decramer S, Chassaing N, Bellanné-Chantelot C, Calvas P, Beaufils S, Bessenay L, Lengelé JP, Dahan K, Ronco P, Devuyst O, Chauveau D (October 2011). “Diagnosis, management, and prognosis of HNF1B nephropathy in adulthood”. Kidney Int. 80 (7): 768–76. doi:10.1038/ki.2011.225. PMID 21775974.
- ↑ Heidet L, Decramer S, Pawtowski A, Morinière V, Bandin F, Knebelmann B, Lebre AS, Faguer S, Guigonis V, Antignac C, Salomon R (June 2010). “Spectrum of HNF1B mutations in a large cohort of patients who harbor renal diseases”. Clin J Am Soc Nephrol. 5 (6): 1079–90. doi:10.2215/CJN.06810909. PMC 2879303. PMID 20378641.
- ↑ Bravo EL (1991). “Pheochromocytoma: new concepts and future trends”. Kidney Int. 40 (3): 544–56. PMID 1787652.
- ↑ Whalen RK, Althausen AF, Daniels GH (1992). “Extra-adrenal pheochromocytoma”. J Urol. 147 (1): 1–10. PMID 1729490.
- ↑ Baid SK, Lai EW, Wesley RA, Ling A, Timmers HJ, Adams KT; et al. (2009). “Brief communication: radiographic contrast infusion and catecholamine release in patients with pheochromocytoma”. Ann Intern Med. 150 (1): 27–32. PMC 3490128. PMID 19124817.
- ↑ Bravo EL (1991). “Pheochromocytoma: new concepts and future trends”. Kidney Int. 40 (3): 544–56. PMID 1787652.
- ↑ Burkitt lymphoma. MedlinePlus. https://www.nlm.nih.gov/medlineplus/ency/article/001308.htm Accessed on September 30, 2015
- ↑ Bellan C, Lazzi S, De Falco G, Nyongo A, Giordano A, Leoncini L (2003). “Burkitt’s lymphoma: new insights into molecular pathogenesis”. J. Clin. Pathol. 56 (3): 188–92. PMC 1769902. PMID 12610094. Unknown parameter
|month=ignored (help) - ↑ Ko HS, Schenk JP, Tröger J, Rohrschneider WK (2007). “Current radiological management of intussusception in children”. Eur Radiol. 17 (9): 2411–21. doi:10.1007/s00330-007-0589-y. PMID 17308922.
- ↑ Boyle MJ, Arkell LJ, Williams JT (1993). “Ultrasonic diagnosis of adult intussusception”. Am. J. Gastroenterol. 88 (4): 617–8. PMID 8470658.
- ↑ Neuroblastoma. Radiopaedia (2015) http://radiopaedia.org/articles/neuroblastoma Accessed on October, 8 2015
- ↑ Colon NC, Chung DH (2011). “Neuroblastoma”. Adv Pediatr. 58 (1): 297–311. doi:10.1016/j.yapd.2011.03.011. PMC 3668791. PMID 21736987.
- ↑ Neuroblastoma. Radiopaedia (2015) http://radiopaedia.org/articles/neuroblastoma Accessed on October, 8 2015
- ↑ Neuroblastoma. Libre Pathology(2015) http://librepathology.org/wiki/index.php/Adrenal_gland#Neuroblastoma Accessed on October, 5 2015
- ↑ Mesoblastic nephroma.Dr Ayush Goel and Dr Yuranga Weerakkody et al. Radiopaedia.org 2015. http://radiopaedia.org/articles/mesoblastic-nephroma
- ↑ Delli K, Spijkervet FK, Vissink A (2014). “Salivary gland diseases: infections, sialolithiasis and mucoceles”. Monogr Oral Sci. 24: 135–48. doi:10.1159/000358794. PMID 24862601.
- ↑ Delli K, Spijkervet FK, Vissink A (2014). “Salivary gland diseases: infections, sialolithiasis and mucoceles”. Monogr Oral Sci. 24: 135–48. doi:10.1159/000358794. PMID 24862601.
- ↑ Capaccio P, Torretta S, Pignataro L, Koch M (2017). “Salivary lithotripsy in the era of sialendoscopy”. Acta Otorhinolaryngol Ital. 37 (2): 113–121. doi:10.14639/0392-100X-1600. PMC 5463518. PMID 28516973.
- ↑ Wallace E, Tauzin M, Hagan J, Schaitkin B, Walvekar RR (2010). “Management of giant sialoliths: review of the literature and preliminary experience with interventional sialendoscopy”. Laryngoscope. 120 (10): 1974–8. doi:10.1002/lary.21082. PMID 20824782.
- ↑ Wallace E, Tauzin M, Hagan J, Schaitkin B, Walvekar RR (2010). “Management of giant sialoliths: review of the literature and preliminary experience with interventional sialendoscopy”. Laryngoscope. 120 (10): 1974–8. doi:10.1002/lary.21082. PMID 20824782.
- ↑ Loury, MC (2006). “Salivary gland disorder”. Advanced Otolaryngology.
- ↑ Raad II, Sabbagh MF, Caranasos GJ (1990). “Acute bacterial sialadenitis: a study of 29 cases and review”. Rev. Infect. Dis. 12 (4): 591–601. PMID 2385766.
- ↑ Silvers AR, Som PM (1998). “Salivary glands”. Radiol. Clin. North Am. 36 (5): 941–66, vi. PMID 9747195.
- ↑ Hoffbrand V, Moss P. Essential Haematology. John Wiley & Sons; 2011
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Soumya Sachdeva, Sowminya Arikapudi, M.B,B.S. [2], Kamal Akbar, M.D.[3]
Epidemiology and Demographics
Overview
Burkitt’s lymphoma is a common disease that tends to affect children or young adults. Males are more commonly affected with Burkitt’s lymphoma compared to females. Burkitt’s lymphoma usually affects individuals of the African race.
Epidemiology and Demographics
Incidence
- The incidence of is approximately 3 to 6 cases per 100,000 children per year for endemic and 0.02 cases per 100,000 people for sporadic burkitt’s lymphoma[1][2]
Age
- Burkitt’s lymphoma is a common disease that tends to affect children or young adults. The median age at diagnosis is 8 years[3]
Gender
- Males are more commonly affected with Burkitt’s lymphoma than females. The Male to Female ratio is approximately 4 to 1[4]
Race
- Burkitt’s lymphoma usually affects individuals of the African race[4]
Region
- The majority of Burkitt’s lymphoma cases are reported in equitorial Africa[5]
References
- ↑ Magrath, Ian (2012). “Epidemiology: clues to the pathogenesis of Burkitt lymphoma”. British Journal of Haematology. 156 (6): 744–756. doi:10.1111/j.1365-2141.2011.09013.x. ISSN 0007-1048.
- ↑ Sant, M.; Allemani, C.; Tereanu, C.; De Angelis, R.; Capocaccia, R.; Visser, O.; Marcos-Gragera, R.; Maynadie, M.; Simonetti, A.; Lutz, J.-M.; Berrino, F. (2010). “Incidence of hematologic malignancies in Europe by morphologic subtype: results of the HAEMACARE project”. Blood. 116 (19): 3724–3734. doi:10.1182/blood-2010-05-282632. ISSN 0006-4971.
- ↑ Dozzo M, Carobolante F, Donisi PM, Scattolin A, Maino E, Sancetta R; et al. (2017). “Burkitt lymphoma in adolescents and young adults: management challenges”. Adolesc Health Med Ther. 8: 11–29. doi:10.2147/AHMT.S94170. PMC 5207020. PMID 28096698.
- ↑ 4.0 4.1 Boerma EG, van Imhoff GW, Appel IM, Veeger NJ, Kluin PM, Kluin-Nelemans JC (2004). “Gender and age-related differences in Burkitt lymphoma–epidemiological and clinical data from The Netherlands”. Eur J Cancer. 40 (18): 2781–7. doi:10.1016/j.ejca.2004.09.004. PMID 15571961.
- ↑ Orem J, Mbidde EK, Lambert B, de Sanjose S, Weiderpass E (2007). “Burkitt’s lymphoma in Africa, a review of the epidemiology and etiology”. Afr Health Sci. 7 (3): 166–75. doi:10.5555/afhs.2007.7.3.166. PMC 2269718. PMID 18052871.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2], Kamal Akbar, M.D.[3]
Risk Factors
Overview
Common risk factors in the development of Burkitt’s lymphoma are HIV/AIDS and post-transplant immunosuppression. There are no established risk factors for childhood Burkitt’s lymphoma.
Risk Factors
Common risk factors in the development of Burkitt’s lymphoma may include:[1]
References
- ↑ 1.0 1.1 Karimi P, Birmann BM, Anderson LA, McShane CM, Gadalla SM, Sampson JN; et al. (2018). “Risk factors for Burkitt lymphoma: a nested case-control study in the UK Clinical Practice Research Datalink”. Br J Haematol. 181 (4): 505–514. doi:10.1111/bjh.15229. PMC 5980720. PMID 29676453.
- ↑ Meister A, Hentrich M, Wyen C, Hübel K (2018). “Malignant lymphoma in the HIV-positive patient”. Eur J Haematol. 101 (1): 119–126. doi:10.1111/ejh.13082. PMID 29663523.
- ↑ Naik S, Tayapongsak K, Robbins K, Manavi CK, Pettenati MJ, Grier DD (2013). “Burkitt’s Lymphoma Presenting as Late-Onset Posttransplant Lymphoproliferative Disorder following Kidney and Pancreas Transplantation: Case Report and Review of the Literature”. Case Rep Oncol. 6 (1): 6–14. doi:10.1159/000346346. PMC 3573821. PMID 23466659.
- ↑ Mbulaiteye SM, Clarke CA, Morton LM, Gibson TM, Pawlish K, Weisenburger DD; et al. (2013). “Burkitt lymphoma risk in U.S. solid organ transplant recipients”. Am J Hematol. 88 (4): 245–50. doi:10.1002/ajh.23385. PMC 3608801. PMID 23386365.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2], Kamal Akbar, M.D.[3]
Screening
Overview
According to the the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for Burkitt’s lymphoma.
Screening
According to the the U.S. Preventive Service Task Force (USPSTF), there is insufficient evidence to recommend routine screening for Burkitt’s lymphoma.[1]
References
- ↑ Recommendations. U.S Preventive Services Task Force. http://www.uspreventiveservicestaskforce.org/BrowseRec/Search?s=Burkitt+lymphoma Accessed on October 1, 2015
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2]
Natural History, Complications and Prognosis
Overview
The prognosis varies with the age, children have the most favorable prognosis. Burkitt’s lymphoma in children is associated with a 5 year survival rate of 90%. The presence of metastasis in bone marrow or CNS is associated with a particularly poor prognosis among patients with Burkitt’s lymphoma.
Complications
Common complications of Burkitt’s lymphoma include:
- Disruption of teeth[1]
- Partial obstruction of airway[2]
- Ulceration and drainage[3]
- Tumor lysis syndrome[4]
Prognosis
- In children, prognosis is good with survival rates >90%[5]
- In adults, prognosis is poor, with a 5-year survival rate of 50% and is even worse with bone marrow or CNS involvement (>30% 5-year survival rate).
References
- ↑ Comfort AO (2004). “Burkitt’s lymphoma of the jaws: role of dental practitioner in management”. Pac Health Dialog. 11 (1): 89–93. PMID 18181448.
- ↑ Aslan G (2013). “Unusual presentation of sporadic Burkitt’s lymphoma originating from the nasal septum: a case report”. J Med Case Rep. 7: 60. doi:10.1186/1752-1947-7-60. PMC 3599746. PMID 23497670.
- ↑ Madabhavi I, Patel A, Revannasiddaiah S, Choudhary M, Anand A, Das P; et al. (2014). “Primary esophageal Burkitt’s lymphoma: a rare case report and review of literature”. Gastroenterol Hepatol Bed Bench. 7 (4): 230–7. PMC 4185878. PMID 25289138.
- ↑ Wössmann W, Schrappe M, Meyer U, Zimmermann M, Reiter A (2003). “Incidence of tumor lysis syndrome in children with advanced stage Burkitt’s lymphoma/leukemia before and after introduction of prophylactic use of urate oxidase”. Ann Hematol. 82 (3): 160–5. doi:10.1007/s00277-003-0608-2. PMID 12634948.
- ↑ Jacobson C, LaCasce A (2014). “How I treat Burkitt lymphoma in adults”. Blood. 124 (19): 2913–20. doi:10.1182/blood-2014-06-538504. PMID 25258344.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Sowminya Arikapudi, M.B,B.S. [2], Kamal Akbar, M.D.[3]
Diagnosis
Diagnosis
Staging | History and Symptoms | Physical Examination | Laboratory Findings | X Ray Findings | CT | MRI | Biopsy | Other Imaging Studies | Other Diagnostic Studies
Treatment
Treatment
Medical Therapy | Surgery | Cost Effectiveness of Therapy | Future or Investigational Therapies
For patient information click here
Synonyms and keywords:: Burkitt’s tumor; Burkitt lymphoma; Burkitt’s type non-Hodgkin’s lymphoma; Malignant lymphoma, Burkitt’s type
Diagnosis
Staging | History and Symptoms | Physical Examination | Laboratory Findings | X Ray Findings | CT | MRI | Biopsy | Other Imaging Studies | Other Diagnostic Studies
Treatment
Medical Therapy | Surgery | Cost Effectiveness of Therapy | Future or Investigational Therapies
Case Studies
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Umar Ahmad, M.D.[2] Sowminya Arikapudi, M.B,B.S. [3]
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Umar Ahmad, M.D.[2] Sowminya Arikapudi, M.B,B.S. [3]