

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Hepatocellular adenoma
Introduction
For patient information, click here
Synonyms and keywords: Hepadenoma; Hepatic adenoma; Liver cell adenoma; Liver adenoma; Liver cell adenomatosis; Hepatocyte adenoma; Inflammatory hepatic adenoma; HNF1-alpha mutated hepatic adenoma; Beta-catenin mutated hepatic adenoma; Hepatocyte benign tumor; Unclassified hepatocellular adenoma; Inflammatory hepatocellular adenoma; HNF1-alpha mutated hepatocellular adenoma; Beta-catenin mutated hepatocellular adenoma; Unclassified hepatic adenoma
Overview
Overview
Hepatocellular adenoma is an uncommon benign liver adenoma that is most commonly associated with oral contraceptive use in women of childbearing age. It was first described by Edmondson in 1958 as an encapsulated liver tumor that does not contain bile ducts. In 1970s several case series supported the hypothesis of an association between oral contraceptives and hepatocellular adenoma. It is generally asymptomatic, the typical clinical manifestations include spontaneous rupture or hemorrhage leading to acute abdominal pain with progression to hypotension and even death. There are no specific physical examination findings associated with adenoma. The liver function tests and serum tumor markers are usually normal, but may be raised secondary to necrosis or hemorrhage and alkaline phosphatase may be raised in hepatocellular adenomatosis. The causes of hepatocellular adenoma include; oral contraceptive medications, long term anabolic androgenic steroids, obesity, metabolic syndrome and glycogen storage diseases. It is more commonly seen in western countries where they are exposed to higher doses of oral contraceptive medications. The estimated incidence is 3 per 1,000,000/year and is 3 to 4 per 100,000 with long term oral contraceptive use. The hepatocellular adenomas are classified on the basis of molecular patterns called phenotypic genotypic classification into 04 groups including; HNF1 alpha inactivated adenoma, beta catenin activated adenoma, inflammatory hepatic adenoma and unclassified type adenoma. The exact pathogenesis of hepatocellular adenoma is still unknown, however, its association with oral contraceptive use is well established. Other associations of adenoma include; long term use of anabolic androgenic steroids and glycogen storage diseases as well. It has been linked to mutations in HNF1a and beta catenin genes. On gross pathology, the hepatocellular adenoma appears as solitary or multiple, unencapsulated and well demarcated lesion, which can occasionally be pedunculated or encapsulated that can also form multiple masses. The intra tumoral hemorrhage can give rise to soft, necrotic, red brown lesion on gross appearance. The microscopic features of hepatocellular adenoma include benign hepatocytes arranged in mildly thickened cell plates with a preserved reticulin network and thin walled arteries. The arteries and arterioles are not accompanied by other portal tract elements such as bile ducts, portal veins or fibroconnective tissue. Hepatocellular adenoma must be differentiated from focal nodular hyperplasia, large regenerative hyperplasia, hepatocellular carcinoma in noncirrhotic patients & fibrolamellar hepatocellular carcinoma, cholangiocarcinoma and metastases. If left untreated, there is 30% bleeding risk. Complications include; bleeding, rupture and malignant transformation. The CT scan findings of hepatocellular adenoma include; non lobulated, well marginated mass that can be encapsulated and rarely calcified and heterogeneous hyperattenuating area within the tumor seen in necrosis or old hemorrhage. The MRI findings include; from hyperintense to mildly hypointense relative to the liver tissue on T1 weighted images. On T2 weighted images they are predominantly hyperintense relative to the liver, whereas in the presence of necrosis or hemorrhage they can be heterogeneous with hyper or hypoattenuating signal. The gold standard method for diagnosis of hepatocellular adenoma is excision biopsy of the liver lesions either by surgery or laparoscopically. There is no specific medical therapy for the adenoma, wait & watch policy is recommended for hepatocellular adenomas <5 cm following cessation of oral contraceptives. Annual followup with MRI or ultrasound is recommended until menopause. Surgical resection is the treatment of choice for adenomas that are >5 cm in diameter, that increase in size, lesions with intra tumoral hemorrhage and male patients (irrespective of the adenoma size). The radiofrequency ablation (RFA) and transcatheter arterial embolization (TAE) may be tried in patients who are poor candidates for surgery.
Historical Perspective
Hepatocellular adenoma was first described in 1958 by Edmondson as an encapsulated liver tumor that does not contain bile ducts. Baum reported the important relationship between the oral contraceptive use and hepatocellular adenoma development in 1973. Edmondson in 1976 published a case control study giving further evidence of this association.
Classification
The hepatocellular adenomas are classified on the basis of molecular patterns called phenotypic–genotypic classification into 04 major groups including; HNF1 alpha inactivated adenoma, beta catenin activated adenoma, inflammatory hepatic adenoma and unclassified type adenoma.
Pathophysiology
The exact pathogenesis of hepatocellular adenoma is still unknown, however, its association with oral contraceptive use is well established. It has also been associated with long term use of anabolic androgenic steroids and glycogen storage diseases. The hepatocellular adenoma have been linked to mutations in HNF1a and beta catenin genes. On gross pathology it appears as a solitary or multiple, unencapsulated and well demarcated mass lesion, which can occasionally be pedunculated or encapsulated that can also form multiple masses. The intratumoral hemorrhage can give rise to soft, necrotic, red brown lesion on gross appearance. The microscopic features of hepatocellular adenoma include benign hepatocytes arranged in mildly thickened cell plates, with a preserved reticulin network and this walled arteries. The arteries and arterioles are not accompanied by other portal tract elements such as bile ducts, portal veins or fibroconnective tissue.
Causes
The causes of hepatocellular adenoma include; oral contraceptive medications, pregnancy, long term use of anabolic androgenic steroids, maturity onset diabetes of the young, metabolic syndrome, obesity, glycogen storage diseases, clomiphene and vascular disorders like portal vein agenesis, budd chiari syndrome and hereditary hemorrhagic telangiectasia.
Epidemiology and Demographics
The hepatocellular adenoma is more common in women in western countries where they are exposed to higher doses of oral contraceptives. The estimated incidence is 3 per 1,000,000/year and is 3 to 4 per 100,000 with long term oral contraceptive use. It is more common in women of childbearing age who take oral contraceptives and can rarely occur in men who take long term anabolic androgenic steroids.
Risk factors
The most important risk factor in the development of hepatocellular adenoma is use of oral contraceptive medications. Other risk factors include; glycogen storage diseases, familial adenomatous polyposis, klinefelters syndrome, metabolic syndrome, obesity, long term use of anabolic androgenic steroids, vascular disorders such as portal vein agenesis, budd chiari syndrome and hereditary hemorrhagic telangiectasia.
Screening
There is insufficient evidence to recommend any screening test for the hepatocellular adenoma.
Differentiating Hepatocellular adenoma from other Diseases
The hepatocellular adenoma must be differentiated from focal nodular hyperplasia, large regenerative hyperplasia, hepatocellular carcinoma in non cirrhotic patients and fibrolamellar hepatocellular carcinoma, cholangiocarcinoma, primary lymphoma and metastases on the basis of clinical presentation and MRI findings.
Natural History, Complications and Prognosis
There is 30% bleeding risk for hepatocellular adenoma if left untreated. The natural course of hepatocellular adenoma after cessation of oral contraceptive use remains unclear, it may regress or remain stable in size. Complications include bleeding, rupture and malignant transformation. The prognosis is usually good after discontinuation of oral contraceptives, as it may regress. In cases where it does not regress after oral contraception withdrawal, surgery is the management of choice.
Diagnosis
History and Symptoms
The small hepatocellular adenoma is generally asymptomatic. Typical clinical manifestations include spontaneous rupture or hemorrhage leading to acute abdominal pain with progression hypotension and even death. There is history of oral contraceptive use in women and long term anabolic steroids use in men.
Physical Examination
There are no specific physical examination findings associated with hepatocellular adenoma.
Laboratory Findings
The hepatocellular adenoma usually have normal liver function tests and normal serum tumor markers, but may be raised secondary to necrosis or hemorrhage and alkaline phosphatase may be raised in hepatocellular adenomatosis.
Chest X Ray
There are no chest x-ray findings associated with hepatocellular adenoma.
CT
The CT scan appearances of hepatocellular adenoma are usually variable and characteristic lesions are best seen with multiphase helical CT scanning. The CT scan findings include; nonlobulated well marginated mass that can be encapsulated and is rarely, heterogeneous hypoattenuating area within the tumor seen in necrosis or old hemorrhage, and larger hepatocellular adenomas may be more heterogeneous than smaller lesions and their CT scan appearance is less specific.
MRI
The MRI findings of hepatocellular adenoma include; from hyperintense to mildly hypointense relatvive to the liver tissue on T1 weighted images. On T2 weighted images they are predominantly hyperintense relative to the liver, whereas in the presence of necrosis and hemorrhage they can be heterogeneous with hyper or hypo attenuating signal. The central scar is on godalinium is not seen in hepatocellular adenoma. There is usually no significant uptake with injection of hepatocellular specific contrast agent, godalinium benzoyloxypropionictetraacetate (Gd-BOTA).
Ultrasound
The ultrasonographic features of hepatocellular adenoma are non specific and may appear as hyper, iso or hypo echoic. It can show a hyper echoic mass. The color doppler ultrasound shows intratumoral veins associated with peritumoral veins and arteries. The contrast enhanced ultrasound is hypervascular in arterial phase and shows centripetal filling in portal venous and delayed phases.
Other Imaging Findings
There are no other imaging findings associated with hepatocellular adenoma.
Other Diagnostic Studies
The gold standard method for diagnosis of hepatocellular adenoma is excision biopsy of liver lesions either by surgery or laparoscopically. Percutaneous biopsy is not recommended due to the risk of bleeding and tumor dissemination. Other tests that can be used to differentiate between benign and carcinomatous lesions include; QBend10 and erbB2 immunostaining, comparative genomic insitu hybridization and fluorescence insitu hybridization.
Treatment
Medical Therapy
here is no specific medical therapy for the hepatocellular adenomas. The wait and watch policy is recommended for hepatocellular adenomas <5cm following cessation of offending drugs (OCPs) and no further growth detected. Annual followup is scheduled with MRI or ultrasound until menopause.
Surgery
The surgical resection is treatment of choice for hepatocellular adenomas that are >5cm in diameter, that increase in size, lesions with intra tumoral hemorrhage and male patients (irrespective of the adenoma size). The liver transplantation may be considered for the hepatocellular adenomas associated with glycogen storage disease type 1. Radiofrequency ablation (RFA) and transcatheter arterial embolization (TAE) may be considered for the adenoma patients who are poor candidates for surgery.
Primary Prevention
here are no primary preventive measures available for hepatocellular adenoma.
Secondary Prevention
An yearly followup with MRI or ultrasound may be scheduled for female patients until menopause.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-In-Chief: Cafer Zorkun, M.D., PhD. Zahir Ali Shaikh, MD[2]
Historical Perspective
Overview
Hepatocellular adenoma was first described in 1958 by Edmondson as an encapsulated liver tumor that does not contain bile ducts. Baum reported the important relationship between oral contraceptive use and hepatocellular adenoma development in 1973. Edmondson, in 1976, published a case control study giving further evidence of this association.
Historical Perspective
- In 1958, hepatocellular adenoma was first described by Edmondson as an encapsulated liver tumor that does not contain bile ducts, when he identified two such lesions in 50,000 autopsies.[1][2]
- In 1973, Baum reported the important relationship between oral contraceptive use and development of hepatocellular adenomas in seven patients.[3][4]
- In the 1970s, several subsequent case series supported the hypothesis of an association between oral contraceptive pills and hepatocellular adenoma.[5]
- In 1976, Edmondson published a case control study giving further evidence of this association. [6]
References
- ↑ Barthelmes L, Tait IS (2005). “Liver cell adenoma and liver cell adenomatosis”. HPB (Oxford). 7 (3): 186–96. doi:10.1080/13651820510028954. PMC 2023950. PMID 18333188.
- ↑ Barthelmes L, Tait IS (2005). “Liver cell adenoma and liver cell adenomatosis”. HPB (Oxford). 7 (3): 186–96. doi:10.1080/13651820510028954. PMC 2023950. PMID 18333188.
- ↑ G. Klatskin (1977). “Hepatic tumors: possible relationship to use of oral contraceptives”. Gastroenterology. 73 (2): 386–394. PMID 194813. Unknown parameter
|month=ignored (help) - ↑ J. K. Baum, J. J. Bookstein, F. Holtz & E. W. Klein (1973). “Possible association between benign hepatomas and oral contraceptives”. Lancet (London, England). 2 (7835): 926–929. PMID 4126557. Unknown parameter
|month=ignored (help) - ↑ E. Horvath, K. Kovacs & R. C. Ross (1974). “Letter: Benign hepatoma in a young woman on contraceptive steroids”. Lancet (London, England). 1 (7853): 357–358. PMID 4131203. Unknown parameter
|month=ignored (help) - ↑ H. A. Edmondson, B. Henderson & B. Benton (1976). “Liver-cell adenomas associated with use of oral contraceptives”. The New England journal of medicine. 294 (9): 470–472. doi:10.1056/NEJM197602262940904. PMID 173996. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Classification
Overview
The hepatocellular adenomas are classified on the basis of molecular patterns called phenotypic–genotypic classification into 4 major groups, including HNF1-alpha inactivated adenoma, beta-catenin activated adenoma, inflammatory hepatic adenoma and unclassified type adenoma.
Classification
- In 2007, Bioulac-Sage and associates from Bordeaux, classified the hepatocellular adenomas based on molecular patterns called phenotypic–genotypic classification. They classified hepatocellular adenomas into 4 main groups.[1][2][3][4]
| Hepatocellular Adenoma | |||||||||||||||||||||||||||||||||||||||||||
| HNF-1 alpha inactivated adenoma | Beta catenin activated adenoma | Inflammatory hepatic adenoma | Unclassified type adenoma | ||||||||||||||||||||||||||||||||||||||||
HNF-1 Alpha Inactivated Hepatocellular Adenoma (35 – 40%)
- This group of hepatocellular adenomas is defined by the somatic inactivation of HNF1A (hepatocyte nuclear factor 1 A) gene by a mutational mechanism in tumor cells.[5]
- HNF1A is a transcription factor controlling hepatocyte metabolism.[6]
- Most of these variants show macrovesicular steatosis of variable extent and no atypical hepatocytes and are associated with metabolic syndrome.
- This type occurs mostly in women and is often associated with maturity onset diabetes of young (MODY3).
- Expression of liver fatty acid binding protein (LFABP) involved in lipid trafficking, usually expressed in normal liver, is specifically down-regulated in these cases as a consequence of HNF1A mutation.
Inflammatory Hepatocellular Adenoma (40 – 50%)
- The most important feature of these tumors is activation of JAK/STAT pathway.[7]
- Inflammatory hepatocellular adenoma also exhibits over expression of serum amyloid alpha (SAA) and C-reactive protein (CRP) induced by STAT3.
- They show greater morphological pleomorphism as they may show pseudo portal tracts, sinusoidal dilatation, dystrophic arteries, hemorrhage, and inflammatory infiltrate.
- Inflammatory syndrome, obesity, and alcohol consumption are reported in these patients.
- Five different molecular drivers, IL6 signal transducer, FRK, STAT3, GNAS, and JAK1 have been reported.[8]
Beta-catenin Mutated Hepatocellular Adenoma (10 – 15%)
- These are frequently associated with exposure to male hormones, glycogenolysis, and familial adenomatous polyposis.[9]
- This group has a higher risk of malignant potential.[10]
- Morphologically, these tumors have cytological and architectural atypical features of tumoral hepatocytes as well as that of cholestasis.
- On immunohistochemical staining, these adenomas tend to stain for glutamine synthetase rather than beta catenin, which stains patchily.
Unclassified Hepatocellular Adenoma (10%)
- By definition, they lack characteristics of other sub-types and their identification relies on a silent phenotype and by exclusion of criteria featuring other sub-types.
- The exact underlying pathogenesis is not completely understood.
- These adenomas do not stain for the C-reactive protein (CRP), beta-catenin, or glutamine synthetase.[11]
References
- ↑ Kun Jiang, Sameer Al-Diffhala & Barbara A. Centeno (2018). “Primary Liver Cancers-Part 1: Histopathology, Differential Diagnoses, and Risk Stratification”. Cancer control : journal of the Moffitt Cancer Center. 25 (1): 1073274817744625. doi:10.1177/1073274817744625. PMID 29350068. Unknown parameter
|month=ignored (help) - ↑ H. Dharmana, S. Saravana-Bawan, S. Girgis & G. Low (2017). “Hepatocellular adenoma: imaging review of the various molecular subtypes”. Clinical radiology. 72 (4): 276–285. doi:10.1016/j.crad.2016.12.020. PMID 28126185. Unknown parameter
|month=ignored (help) - ↑ Paulette Bioulac-Sage, Christine Sempoux & Charles Balabaud (2017). “Hepatocellular adenoma: Classification, variants and clinical relevance”. Seminars in diagnostic pathology. 34 (2): 112–125. doi:10.1053/j.semdp.2016.12.007. PMID 28131467. Unknown parameter
|month=ignored (help) - ↑ Paulette Bioulac-Sage, Sandra Rebouissou, Cristel Thomas, Jean-Frederic Blanc, Jean Saric, Antonio Sa Cunha, Anne Rullier, Gaelle Cubel, Gabrielle Couchy, Sandrine Imbeaud, Charles Balabaud & Jessica Zucman-Rossi (2007). “Hepatocellular adenoma subtype classification using molecular markers and immunohistochemistry”. Hepatology (Baltimore, Md.). 46 (3): 740–748. doi:10.1002/hep.21743. PMID 17663417. Unknown parameter
|month=ignored (help) - ↑ Aparna P.. Shreenath & Arslan Kahloon (2018). “Hepatic (Hepatocellular) Adenoma”. PMID 30020636. Unknown parameter
|month=ignored (help) - ↑ Motoko Sasaki, Norihide Yoneda, Seiko Kitamura, Yasunori Sato & Yasuni Nakanuma (2011). “Characterization of hepatocellular adenoma based on the phenotypic classification: The Kanazawa experience”. Hepatology research : the official journal of the Japan Society of Hepatology. 41 (10): 982–988. doi:10.1111/j.1872-034X.2011.00851.x. PMID 21883740. Unknown parameter
|month=ignored (help) - ↑ Jean-Charles Nault, Paulette Bioulac-Sage & Jessica Zucman-Rossi (2013). “Hepatocellular benign tumors-from molecular classification to personalized clinical care”. Gastroenterology. 144 (5): 888–902. doi:10.1053/j.gastro.2013.02.032. PMID 23485860. Unknown parameter
|month=ignored (help) - ↑ Motoko Sasaki, Norihide Yoneda, Yoshiyuki Sawai, Yasuharu Imai, Fukuo Kondo, Toshio Fukusato, Seiichi Yoshikawa, Satoshi Kobayashi, Yasunori Sato, Osamu Matsui & Yasuni Nakanuma (2015). “Clinicopathological characteristics of serum amyloid A-positive hepatocellular neoplasms/nodules arising in alcoholic cirrhosis”. Histopathology. 66 (6): 836–845. doi:10.1111/his.12588. PMID 25318388. Unknown parameter
|month=ignored (help) - ↑ Kimberley J. Evason, James P. Grenert, Linda D. Ferrell & Sanjay Kakar (2013). “Atypical hepatocellular adenoma-like neoplasms with beta-catenin activation show cytogenetic alterations similar to well-differentiated hepatocellular carcinomas”. Human pathology. 44 (5): 750–758. doi:10.1016/j.humpath.2012.07.019. PMID 23084586. Unknown parameter
|month=ignored (help) - ↑ Camilla Pilati, Eric Letouze, Jean-Charles Nault, Sandrine Imbeaud, Anais Boulai, Julien Calderaro, Karine Poussin, Andrea Franconi, Gabrielle Couchy, Guillaume Morcrette, Maxime Mallet, Said Taouji, Charles Balabaud, Benoit Terris, Frederic Canal, Valerie Paradis, Jean-Yves Scoazec, Anne de Muret, Catherine Guettier, Paulette Bioulac-Sage, Eric Chevet, Fabien Calvo & Jessica Zucman-Rossi (2014). “Genomic profiling of hepatocellular adenomas reveals recurrent FRK-activating mutations and the mechanisms of malignant transformation”. Cancer cell. 25 (4): 428–441. doi:10.1016/j.ccr.2014.03.005. PMID 24735922. Unknown parameter
|month=ignored (help) - ↑ Paulette Bioulac-Sage, Gaelle Cubel, Said Taouji, Jean-Yves Scoazec, Emmanuelle Leteurtre, Valerie Paradis, Nathalie Sturm, Jeanne Tran Van Nhieu, Dominique Wendum, Brigitte Bancel, Jeanne Ramos, Francois Paraf, Marie Christine Saint Paul, Sophie Michalak, Monique Fabre, Catherine Guettier, Brigitte Le Bail, Jessica Zucman-Rossi & Charles Balabaud (2012). “Immunohistochemical markers on needle biopsies are helpful for the diagnosis of focal nodular hyperplasia and hepatocellular adenoma subtypes”. The American journal of surgical pathology. 36 (11): 1691–1699. doi:10.1097/PAS.0b013e3182653ece. PMID 23060349. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Pathophysiology
Overview
The exact pathogenesis of hepatocellular adenoma is still unknown, however, its association with oral contraceptive use is well established. It has also been associated with long term use of anabolic androgenic steroids and glycogen storage diseases. It has been linked to mutations in HNF1A and beta-catenin genes. On gross pathology, it appears as a solitary or multiple, unencapsulated and well demarcated mass, which can occasionally be pedunculated or encapsulated and also form multiple masses. The intratumoral hemorrhage can give rise to soft, necrotic, and red brown lesion on gross appearance. The microscopic features of hepatocellular adenoma include benign hepatocytes arranged in mildly thickened cell plates, with a preserved reticulin network and thin walled arteries. The arteries and arterioles are not accompanied by other portal tract elements such as bile ducts, portal veins, or fibroconnective tissue.
Pathophysiology
- The exact pathogenesis of hepatocellular adenoma is still unknown, however, its association with oral contraceptive use is well established.[1]
- In 1973, Baum et al first described the causal association of hepatocellular adenoma with oral contraceptive use.
- In 1979, Rooks et al reported the relationship with oral contraceptive use to be dose and duration dependent and is highest in women over 30 years of age after using oral contraceptive for more than 24 months.[2]
- Hepatocellular adenoma has also been associated with long term use of anabolic androgenic steroids and glycogen storage diseases.
- Other rare causal associations include familial adenomatous polyposis, maturity onset diabetes of the young, obesity, metabolic syndrome, and vascular disorders like portal vein agenesis, Budd chiari syndrome, and hereditary hemorrhagic telangiectasia.[3][4]
Genetics
- Hepatocellular adenoma has been linked to mutations in the hepatocyte nuclear factor 1 alpha (HNF1a) gene and beta catenin gene.[5]
Gross Pathology
- On gross pathological appearance, hepatocellular adenoma is a solitary or multiple, unencapsulated and well demarcated mass lesion, which can occasionally be pedunculated or encapsulated, which can also form multiple masses.[6][7]
- The mass has a soft and fleshy consistency and size ranges from 1 to 30 cm.
- The cut surface may be solid tan or yellow depending upon the presence or absence of steatosis.
- The intratumoral hemorrhage can give rise to a soft, necrotic, red brown lesion.
Microscopic Pathology
- The microscopic features of hepatocellular adenoma include benign hepatocytes arranged in mildly thickened cell plates, with a preserved reticulin network and thin walled arteries.[6]
- Tumor hepatocytes have cytoplasm that may be normal, clear (glycogen rich), steatotic, or contain pigment in the lysosomes.[5][8]
- Nuclear atypia and mitosis are unusual but may be seen in specific variants.[5][9]
- The arteries and arterioles are not accompanied by other portal tract elements, such as bile ducts, portal veins or fibroconnective tissue.
- Other variable features include the presence of steatosis, inflammatory cell infiltrates, dystrophic blood vessels, ductular reaction, sinusoidal dilatation, hemorrhage, and peliosis.[10][11]
-
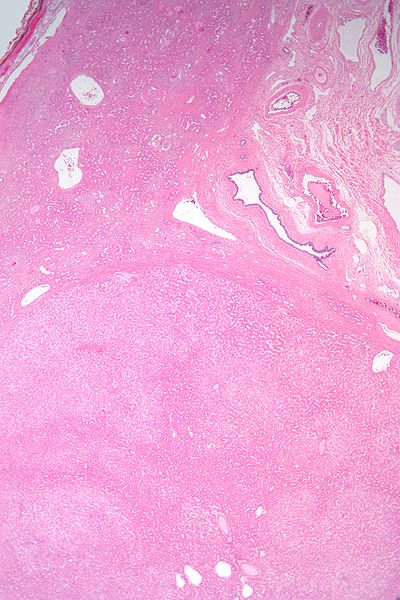 Low magnification micrograph of a hepatic adenoma. H&E stain.[12]
-
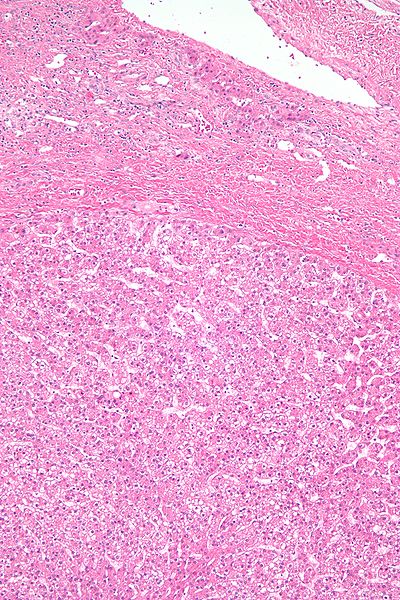 High magnification micrograph of a hepatic adenoma. H&E stain.[13]


References
- ↑ J. K. Baum, J. J. Bookstein, F. Holtz & E. W. Klein (1973). “Possible association between benign hepatomas and oral contraceptives”. Lancet (London, England). 2 (7835): 926–929. PMID 4126557. Unknown parameter
|month=ignored (help) - ↑ L. Rosenberg (1991). “The risk of liver neoplasia in relation to combined oral contraceptive use”. Contraception. 43 (6): 643–652. PMID 1651205. Unknown parameter
|month=ignored (help) - ↑ Khan, MuhammadRizwan; Begum, Saleema (2018). “Hepatocellular adenoma: Review of contemporary diagnostic and therapeutic options”. IJS Short Reports. 3 (1): 1. doi:10.4103/ijssr.ijssr_4_18. ISSN 2468-7332.
- ↑ Védie, Anne-Laure; Sutter, Olivier; Ziol, Marianne; Nault, Jean-Charles (2018). “Molecular classification of hepatocellular adenomas: impact on clinical practice”. Hepatic Oncology. 5 (1): HEP04. doi:10.2217/hep-2017-0023. ISSN 2045-0923.
- ↑ 5.0 5.1 5.2 Nault, Jean-Charles; Paradis, Valérie; Cherqui, Daniel; Vilgrain, Valérie; Zucman-Rossi, Jessica (2017). “Molecular classification of hepatocellular adenoma in clinical practice”. Journal of Hepatology. 67 (5): 1074–1083. doi:10.1016/j.jhep.2017.07.009. ISSN 0168-8278.
- ↑ 6.0 6.1 Barthelmes L, Tait IS (2005). “Liver cell adenoma and liver cell adenomatosis”. HPB (Oxford). 7 (3): 186–96. doi:10.1080/13651820510028954. PMC 2023950. PMID 18333188.
- ↑ Grazioli L, Federle MP, Brancatelli G, Ichikawa T, Olivetti L, Blachar A (2001). “Hepatic adenomas: imaging and pathologic findings”. Radiographics. 21 (4): 877–92, discussion 892-4. doi:10.1148/radiographics.21.4.g01jl04877. PMID 11452062.
- ↑ L. M. Franco, V. Krishnamurthy, D. Bali, D. A. Weinstein, P. Arn, B. Clary, A. Boney, J. Sullivan, D. P. Frush, Y.-T. Chen & P. S. Kishnani (2005). “Hepatocellular carcinoma in glycogen storage disease type Ia: a case series”. Journal of inherited metabolic disease. 28 (2): 153–162. doi:10.1007/s10545-005-7500-2. PMID 15877204.
- ↑ L. M. Franco, V. Krishnamurthy, D. Bali, D. A. Weinstein, P. Arn, B. Clary, A. Boney, J. Sullivan, D. P. Frush, Y.-T. Chen & P. S. Kishnani (2005). “Hepatocellular carcinoma in glycogen storage disease type Ia: a case series”. Journal of inherited metabolic disease. 28 (2): 153–162. doi:10.1007/s10545-005-7500-2. PMID 15877204.
- ↑ Dhingra, Sadhna; Fiel, M. Isabel (2014). “Update on the New Classification of Hepatic Adenomas: Clinical, Molecular, and Pathologic Characteristics”. Archives of Pathology & Laboratory Medicine. 138 (8): 1090–1097. doi:10.5858/arpa.2013-0183-RA. ISSN 0003-9985.
- ↑ Nault, Jean-Charles; Couchy, Gabrielle; Balabaud, Charles; Morcrette, Guillaume; Caruso, Stefano; Blanc, Jean-Frederic; Bacq, Yannick; Calderaro, Julien; Paradis, Valérie; Ramos, Jeanne; Scoazec, Jean-Yves; Gnemmi, Viviane; Sturm, Nathalie; Guettier, Catherine; Fabre, Monique; Savier, Eric; Chiche, Laurence; Labrune, Philippe; Selves, Janick; Wendum, Dominique; Pilati, Camilla; Laurent, Alexis; De Muret, Anne; Le Bail, Brigitte; Rebouissou, Sandra; Imbeaud, Sandrine; Bioulac-Sage, Paulette; Letouzé, Eric; Zucman-Rossi, Jessica; Laurent, Christophe; Saric, Jean; Frulio, Nora; Castain, Claire; Dujardin, Fanny; Benchellal, Zin; Bourlier, Pascal; Azoulay, Daniel; Luciani, Alain; Pageaux, Georges-Philippe; Fabre, Jean-Michel; Vilgrain, Valerie; Belghiti, Jacques; Bancel, Brigitte; Boleslawski, Emmanuel; Letoublon, Christophe; Vaillant, Jean Christophe; Prévôt, Sophie; Castaing, Denis; Jacquemin, Emmanuel; Peron, Jean Marie; Quaglia, Alberto; Paye, François; Terraciano, Luigi; Mazzaferro, Vincenzo; Saint Paul, Marie Christine; Terris, Benoit (2017). “Molecular Classification of Hepatocellular Adenoma Associates With Risk Factors, Bleeding, and Malignant Transformation”. Gastroenterology. 152 (4): 880–894.e6. doi:10.1053/j.gastro.2016.11.042. ISSN 0016-5085.
- ↑ Hepatic adenoma. Librepathology (2015). http://librepathology.org/wiki/index.php/File:Hepatic_adenoma_low_mag.jpg Accessed on November 3, 2015
- ↑ Hepatic adenoma. Librepathology (2015). http://librepathology.org/wiki/index.php/File:Hepatic_adenoma_high_mag.jpg Accessed on November 7, 2015
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Causes
Overview
Estrogen has a central role in the development of hepatocellular adenoma. The causes of hepatocellular adenoma can include the settings where prolonged and/or excessive estrogen exposure is involved. These can include oral contraceptive medications, pregnancy, long term use of anabolic androgenic steroids, metabolic syndrome, obesity, glycogen storage diseases, and clomiphene.
Causes
- Estrogen has a central role in the development of hepatocellular adenoma.
- The causes of hepatocellular adenoma can include the settings involving prolonged and/or excessive estrogen exposure, such as:[1][2][3][4][5][6][7][8][9]
References
- ↑ M. Kawakatsu, V. Vilgrain, S. Erlinger & H. Nahum (1997). “Disappearance of liver cell adenoma: CT and MR imaging”. Abdominal imaging. 22 (3): 274–276. PMID 9107649. Unknown parameter
|month=ignored (help) - ↑ W. H. Marks, N. Thompson & H. Appleman (1988). “Failure of hepatic adenomas (HCA) to regress after discontinuance of oral contraceptives. An association with focal nodular hyperplasia (FNH) and uterine leiomyoma”. Annals of surgery. 208 (2): 190–195. PMID 2840865. Unknown parameter
|month=ignored (help)</ref<ref>H. Tesluk & J. Lawrie (1981). “Hepatocellular adenoma. Its transformation to carcinoma in a user of oral contraceptives”. Archives of pathology & laboratory medicine. 105 (6): 296–299. PMID 6263214. Unknown parameter|month=ignored (help) - ↑ D. Carrasco, M. Barrachina, M. Prieto & J. Berenguer (1984). “Clomiphene citrate and liver-cell adenoma”. The New England journal of medicine. 310 (17): 1120–1121. doi:10.1056/NEJM198404263101716. PMID 6323982. Unknown parameter
|month=ignored (help) - ↑ G. B. Coombes, J. Reiser, F. J. Paradinas & I. Burn (1978). “An androgen-associated hepatic adenoma in a trans-sexual”. The British journal of surgery. 65 (12): 869–870. PMID 737424. Unknown parameter
|month=ignored (help) - ↑ U. Beuers, W. O. Richter, M. M. Ritter, B. Wiebecke & P. Schwandt (1991). “Klinefelter’s syndrome and liver adenoma”. Journal of clinical gastroenterology. 13 (2): 214–216. PMID 1851773. Unknown parameter
|month=ignored (help) - ↑ N. S. Alshak, J. Cocjin, L. Podesta, R. van de Velde, L. Makowka, P. Rosenthal & S. A. Geller (1994). “Hepatocellular adenoma in glycogen storage disease type IV”. Archives of pathology & laboratory medicine. 118 (1): 88–91. PMID 8285839. Unknown parameter
|month=ignored (help) - ↑ P. Labrune, P. Trioche, I. Duvaltier, P. Chevalier & M. Odievre (1997). “Hepatocellular adenomas in glycogen storage disease type I and III: a series of 43 patients and review of the literature”. Journal of pediatric gastroenterology and nutrition. 24 (3): 276–279. PMID 9138172. Unknown parameter
|month=ignored (help) - ↑ S. Bala, P. H. Wunsch & W. G. Ballhausen (1997). “Childhood hepatocellular adenoma in familial adenomatous polyposis: mutations in adenomatous polyposis coli gene and p53”. Gastroenterology. 112 (3): 919–922. PMID 9041254. Unknown parameter
|month=ignored (help) - ↑ J. K. Baum, J. J. Bookstein, F. Holtz & E. W. Klein (1973). “Possible association between benign hepatomas and oral contraceptives”. Lancet (London, England). 2 (7835): 926–929. PMID 4126557. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Epidemiology and Demographics
Overview
Hepatocellular adenoma is more common in women in Western countries where they are exposed to higher doses of oral contraceptives. The estimated incidence is 3 per 100,000 individuals/year and is 3 to 4 per 100,000 individuals with long term history of oral contraceptive use. It is more common in women of childbearing age who take oral contraceptives and can rarely occur in men who take long term anabolic androgenic steroids.
Epidemiology and Demographics
Incidence
- The estimated incidence of hepatocellular adenoma is 3 per 100,000 individuals/year.[1][2][3]
- The annual incidence is substantially higher with long term oral contraceptive use, estimated at 3 to 4 per 100,000 individuals, but may be less with newer oral contraceptives.
Prevalence
- Prevalence of hepatocellular adenoma is difficult to asses because of the large proportion of adenomas not presenting with conventional symptoms.
- The prevalence of hepatocellular adenoma was increased in the 1970s following the introduction of oral contraception in Western countries.[4]
Age
- The hepatocellular adenoma is more common in women of childbearing age who take oral contraceptives.[5][6]
Gender
- The hepatocellular adenoma is more common in women of childbearing age who take oral contraceptives.[6]
- It can also rarely develop in men with long term anabolic androgenic steroids use.[7]
References
- ↑ Barthelmes L, Tait IS (2005). “Liver cell adenoma and liver cell adenomatosis”. HPB (Oxford). 7 (3): 186–96. doi:10.1080/13651820510028954. PMC 2023950. PMID 18333188.
- ↑ Nault, Jean-Charles; Couchy, Gabrielle; Balabaud, Charles; Morcrette, Guillaume; Caruso, Stefano; Blanc, Jean-Frederic; Bacq, Yannick; Calderaro, Julien; Paradis, Valérie; Ramos, Jeanne; Scoazec, Jean-Yves; Gnemmi, Viviane; Sturm, Nathalie; Guettier, Catherine; Fabre, Monique; Savier, Eric; Chiche, Laurence; Labrune, Philippe; Selves, Janick; Wendum, Dominique; Pilati, Camilla; Laurent, Alexis; De Muret, Anne; Le Bail, Brigitte; Rebouissou, Sandra; Imbeaud, Sandrine; Bioulac-Sage, Paulette; Letouzé, Eric; Zucman-Rossi, Jessica; Laurent, Christophe; Saric, Jean; Frulio, Nora; Castain, Claire; Dujardin, Fanny; Benchellal, Zin; Bourlier, Pascal; Azoulay, Daniel; Luciani, Alain; Pageaux, Georges-Philippe; Fabre, Jean-Michel; Vilgrain, Valerie; Belghiti, Jacques; Bancel, Brigitte; Boleslawski, Emmanuel; Letoublon, Christophe; Vaillant, Jean Christophe; Prévôt, Sophie; Castaing, Denis; Jacquemin, Emmanuel; Peron, Jean Marie; Quaglia, Alberto; Paye, François; Terraciano, Luigi; Mazzaferro, Vincenzo; Saint Paul, Marie Christine; Terris, Benoit (2017). “Molecular Classification of Hepatocellular Adenoma Associates With Risk Factors, Bleeding, and Malignant Transformation”. Gastroenterology. 152 (4): 880–894.e6. doi:10.1053/j.gastro.2016.11.042. ISSN 0016-5085.
- ↑ J. B. Rooks, H. W. Ory, K. G. Ishak, L. T. Strauss, J. R. Greenspan, A. P. Hill & C. W. Jr Tyler (1979). “Epidemiology of hepatocellular adenoma. The role of oral contraceptive use”. JAMA. 242 (7): 644–648. PMID 221698. Unknown parameter
|month=ignored (help) - ↑ Védie, Anne-Laure; Sutter, Olivier; Ziol, Marianne; Nault, Jean-Charles (2018). “Molecular classification of hepatocellular adenomas: impact on clinical practice”. Hepatic Oncology. 5 (1): HEP04. doi:10.2217/hep-2017-0023. ISSN 2045-0923.
- ↑ L. A. Heinemann, A. Weimann, G. Gerken, C. Thiel, M. Schlaud & T. DoMinh (1998). “Modern oral contraceptive use and benign liver tumors: the German Benign Liver Tumor Case-Control Study”. The European journal of contraception & reproductive health care : the official journal of the European Society of Contraception. 3 (4): 194–200. PMID 10036602. Unknown parameter
|month=ignored (help) - ↑ 6.0 6.1 Nault, Jean-Charles; Paradis, Valérie; Cherqui, Daniel; Vilgrain, Valérie; Zucman-Rossi, Jessica (2017). “Molecular classification of hepatocellular adenoma in clinical practice”. Journal of Hepatology. 67 (5): 1074–1083. doi:10.1016/j.jhep.2017.07.009. ISSN 0168-8278.
- ↑ G. B. Coombes, J. Reiser, F. J. Paradinas & I. Burn (1978). “An androgen-associated hepatic adenoma in a trans-sexual”. The British journal of surgery. 65 (12): 869–870. PMID 737424. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Risk Factors
Overview
The most important risk factor for the development of hepatocellular adenoma is the use of oral contraceptive medications. Other risk factors include glycogen storage diseases, familial adenomatous polyposis, Klinefelter’s syndrome, metabolic syndrome, obesity, long term use of anabolic androgenic steroids, vascular disorders such as portal vein agenesis, Budd-Chiari syndrome, and hereditary hemorrhagic telangiectasia.
Risk Factors
- The most important risk factor for the development of hepatocellular adenoma is the use of oral contraceptive medications, such as:[1]
- Drospirenone and Ethinyl estradiol
- Norethindrone acetate and Ethinyl estradiol
- Norgestimate and Ethinyl estradiol
- Norgestrel and Ethinyl estradiol
- The risk is proportional to:[2]
- Hormonal dose
- Duration of medication
- Other risk factors include:[2][3][4][5]
Risk Factors for Malignant Transformation
Risk factors for the malignant transformation of hepatocellular adenoma to hepatocellular carcinoma include:[6]
- Gender (men)
- Size (> 8 cm)
- Sub-type (beta-catenin-activated hepatocellular adenoma)
References
- ↑ L. Rosenberg (1991). “The risk of liver neoplasia in relation to combined oral contraceptive use”. Contraception. 43 (6): 643–652. PMID 1651205. Unknown parameter
|month=ignored (help) - ↑ 2.0 2.1 Barthelmes L, Tait IS (2005). “Liver cell adenoma and liver cell adenomatosis”. HPB (Oxford). 7 (3): 186–96. doi:10.1080/13651820510028954. PMC 2023950. PMID 18333188.
- ↑ U. Beuers, W. O. Richter, M. M. Ritter, B. Wiebecke & P. Schwandt (1991). “Klinefelter’s syndrome and liver adenoma”. Journal of clinical gastroenterology. 13 (2): 214–216. PMID 1851773. Unknown parameter
|month=ignored (help) - ↑ N. S. Alshak, J. Cocjin, L. Podesta, R. van de Velde, L. Makowka, P. Rosenthal & S. A. Geller (1994). “Hepatocellular adenoma in glycogen storage disease type IV”. Archives of pathology & laboratory medicine. 118 (1): 88–91. PMID 8285839. Unknown parameter
|month=ignored (help) - ↑ S. Bala, P. H. Wunsch & W. G. Ballhausen (1997). “Childhood hepatocellular adenoma in familial adenomatous polyposis: mutations in adenomatous polyposis coli gene and p53”. Gastroenterology. 112 (3): 919–922. PMID 9041254. Unknown parameter
|month=ignored (help) - ↑ Aamann L, Schultz N, Fallentin E, Hamilton-Dutoit S, Vogel I, Grønbæk H (2015). “[Hepatocellular adenoma – new classification and recommendations]”. Ugeskr Laeger. 177 (12). PMID 25786843.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Screening
Overview
There is insufficient evidence to recommend routine screening for hepatocellular adenoma.
Screening
There is insufficient evidence to recommend routine screening for hepatocellular adenoma.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Differentiating Hepatocellular adenoma from other Diseases

Overview
Hepatocellular adenoma must be differentiated from focal nodular hyperplasia, large regenerative hyperplasia, hepatocellular carcinoma in non cirrhotic patients, fibrolamellar hepatocellular carcinoma, cholangiocarcinoma, primary lymphoma, and metastases on the basis of clinical presentation and MRI findings.
Differentiating Hepatocellular Adenoma from other Diseases
Hepatocellular adenoma must be differentiated from focal nodular hyperplasia, large regenerative hyperplasia, hepatocellular carcinoma in non cirrhotic patients, fibrolamellar hepatocellular carcinoma, cholangiocarcinoma, primary lymphoma, and metastases on the basis of clinical presentation and MRI findings:[1][2][3][4][5][6][7][8][9][10][11][12][13][14][15][16][16][17][18][19][20][21][22][13][23][24][25][26][27][28] [29][30][31][32][33][34][35][36][37][38][39][40][41][42][43][44][45]
Abbreviations: RUQ= Right upper quadrant of the abdomen, LUQ= Left upper quadrant, LLQ= Left lower quadrant, RLQ= Right lower quadrant, LFT= Liver function test, SIRS= Systemic inflammatory response syndrome, ERCP= Endoscopic retrograde cholangiopancreatography, IV= Intravenous, N= Normal, AMA= Anti-mitochondrial antibodies, LDH= Lactate dehydrogenase, GI= Gastrointestinal, CXR= Chest X ray, IgA= Immunoglobulin A, IgG= Immunoglobulin G, IgM= Immunoglobulin M, CT= Computed tomography, PMN= Polymorphonuclear cells, ESR= Erythrocyte sedimentation rate, CRP= C-reactive protein, TS= Transferrin saturation, SF= Serum ferritin, SMA= Superior mesenteric artery, SMV= Superior mesenteric vein, ECG= Electrocardiogram
| Disease | Clinical Manifestations | Diagnosis | Comments | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Symptoms | Signs | |||||||||||||||
| Abdominal Pain | Fever | Rigors and Chills | Nausea or Vomiting | Jaundice | Constipation | Diarrhea | Weight Loss | GI Bleeding | Hypotension | Guarding | Rebound Tenderness | Bowel Sounds | Lab Findings | Imaging | ||
| Hepatocellular adenoma | RUQ | – | – | – | – | – | – | – | + | + | – | – |
|
|
| |
| Hepatocellular carcinoma/Metastasis | RUQ | + | − | + | + | + | + | + | + | + | − | + |
|
|
Other symptoms: | |
| Cholangiocarcinoma | RUQ | + | − | + | + | − | − | + | − | − | − | + |
|
|
| |
| Pancreatic carcinoma | MidEpigastric | − | − | + | + | + | − | + | − | − | − | + |
|
Skin manifestations may include: | ||
| Focal nodular hyperplasia | Diffuse | ± | − | − | ± | − | − | + | + | − | − | − |
|
|
|
|
| Disease | Abdominal Pain | Fever | Rigors and Chills | Nausea or Vomiting | Jaundice | Constipation | Diarrhea | Weight Loss | GI Bleeding | Hypotension | Guarding | Rebound Tenderness | Bowel Sounds | Lab Findings | Imaging | Comments |
| Gallbladder cancer | Midepigastric | − | − | + | + | − | + | + | − | − | − | − |
|
|||
| Liver hemangioma | Intermittent RUQ | − | − | + | + | − | − | − | − | − | − | − |
|
|
| |
| Liver abscess | RUQ | + | − | + | + | − | − | + | − | − | − | − |
|
|
||
| Cirrhosis | RUQ +Bloating | + | − | + | + | − | − | + | − | − | − | − |
|
|
|
|
| Inflammatory lesions | RUQ | ± | − | + | + | − | − | − | − | − | − | − |
|
|
|
|
References
- ↑ Choi BI, Kim TK, Han JK (1998). “MRI of clonorchiasis and cholangiocarcinoma”. J Magn Reson Imaging. 8 (2): 359–66. PMID 9562062.
- ↑ Guo, Le-Hang; Xu, Hui-Xiong (2015). “Contrast-Enhanced Ultrasound in the Diagnosis of Hepatocellular Carcinoma and Intrahepatic Cholangiocarcinoma: Controversy over the ASSLD Guideline”. BioMed Research International. 2015: 1–5. doi:10.1155/2015/349172. ISSN 2314-6133.
- ↑ Wilson, Stephanie R.; Kim, Tae Kyoung; Jang, Hyun-Jung; Burns, Peter N. (2007). “Enhancement Patterns of Focal Liver Masses: Discordance Between Contrast-Enhanced Sonography and Contrast-Enhanced CT and MRI”. American Journal of Roentgenology. 189 (1): W7–W12. doi:10.2214/AJR.06.1060. ISSN 0361-803X.
- ↑ Ohtomo K, Baron RL, Dodd GD, Federle MP, Miller WJ, Campbell WL, Confer SR, Weber KM (1993). “Confluent hepatic fibrosis in advanced cirrhosis: appearance at CT”. Radiology. 188 (1): 31–5. doi:10.1148/radiology.188.1.8511316. PMID 8511316.
- ↑ Wu, Jim S.; Saluja, Sanjay; Garcia-Tsao, Guadalupe; Chong, Alice; Henderson, Katherine J.; White, Robert I. (2006). “Liver Involvement in Hereditary Hemorrhagic Telangiectasia: CT and Clinical Findings Do Not Correlate in Symptomatic Patients”. American Journal of Roentgenology. 187 (4): W399–W405. doi:10.2214/AJR.05.1068. ISSN 0361-803X.
- ↑ Itai, Y; Matsui, O (1997). “Blood flow and liver imaging”. Radiology. 202 (2): 306–314. doi:10.1148/radiology.202.2.9015047. ISSN 0033-8419.
- ↑ {{cite
- ↑ Mathieu D, Vasile N, Dibie C, Grenier P (1985). “Portal cavernoma: dynamic CT features and transient differences in hepatic attenuation”. Radiology. 154 (3): 743–8. doi:10.1148/radiology.154.3.3881794. PMID 3881794.
- ↑ Itai Y, Murata S, Saida Y, Minami M. Central zone and peripheral zone of the liver based on portal and hepatic arterial blood supply: imaging approach to deformity of cirrhotic liver. Jpn J Clin Radiol. 1994;39:1553–1559
- ↑ Kim, Tae Kyoung; Lee, Kyoung Ho; Jang, Hyun–Jung; Haider, Masoom A.; Jacks, Lindsay M.; Menezes, Ravi J.; Park, Seong Ho; Yazdi, Leyla; Sherman, Morris; Khalili, Korosh (2011). “Analysis of Gadobenate Dimeglumine–enhanced MR Findings for Characterizing Small (1–2-cm) Hepatic Nodules in Patients at High Risk for Hepatocellular Carcinoma”. Radiology. 259 (3): 730–738. doi:10.1148/radiol.11101549. ISSN 0033-8419.
- ↑ Kim JH, Kim TK, Kim BS, Eun HW, Kim PN, Lee MG, Ha HK (2002). “Enhancement of hepatic hemangiomas with levovist on coded harmonic angiographic ultrasonography”. J Ultrasound Med. 21 (2): 141–8. PMID 11833870.
- ↑ Brannigan, Margot; Burns, Peter N.; Wilson, Stephanie R. (2004). “Blood Flow Patterns in Focal Liver Lesions at Microbubble-enhanced US”. RadioGraphics. 24 (4): 921–935. doi:10.1148/rg.244035158. ISSN 0271-5333.
- ↑ 13.0 13.1 Kim TK, Jang HJ, Wilson SR (2006). “Benign liver masses: imaging with microbubble contrast agents”. Ultrasound Q. 22 (1): 31–9. PMID 16641791.
- ↑ Jang, Hyun-Jung; Kim, Tae Kyoung; Lim, Hyo Keun; Park, Sang Jae; Sim, Jung Suk; Kim, Hyae Young; Lee, Joo-Hyuk (2003). “Hepatic Hemangioma: Atypical Appearances on CT, MR Imaging, and Sonography”. American Journal of Roentgenology. 180 (1): 135–141. doi:10.2214/ajr.180.1.1800135. ISSN 0361-803X.
- ↑ . doi:10.1102/1470-7330.2009.0015. Missing or empty
|title=(help) - ↑ 16.0 16.1 Jang, Hyun-Jung; Yu, Hojun; Kim, Tae Kyoung (2009). “Imaging of Focal Liver Lesions”. Seminars in Roentgenology. 44 (4): 266–282. doi:10.1053/j.ro.2009.05.008. ISSN 0037-198X.
- ↑ Bhayana, Deepak; Kim, Tae Kyoung; Jang, Hyun-Jung; Burns, Peter N.; Wilson, Stephanie R. (2010). “Hypervascular Liver Masses on Contrast-Enhanced Ultrasound: The Importance of Washout”. American Journal of Roentgenology. 194 (4): 977–983. doi:10.2214/AJR.09.3375. ISSN 0361-803X.
- ↑ Tamada T, Ito K, Yamamoto A, Sone T, Kanki A, Tanaka F, Higashi H (2011). “Hepatic hemangiomas: evaluation of enhancement patterns at dynamic MRI with gadoxetate disodium”. AJR Am J Roentgenol. 196 (4): 824–30. doi:10.2214/AJR.10.5113. PMID 21427331.
- ↑ Heiken, Jay P. (2007). “Distinguishing benign from malignant liver tumours”. Cancer Imaging. 7 (Special Issue A): S1–S14. doi:10.1102/1470-7330.2007.9084. ISSN 1470-7330.
- ↑ Alturkistany, Samira; Jang, Hyun-Jung; Yu, Hojun; Lee, Kyoung Ho; Kim, Tae Kyoung (2011). “Fading hepatic hemangiomas on multiphasic CT”. Abdominal Radiology. 37 (5): 775–780. doi:10.1007/s00261-011-9826-6. ISSN 2366-004X.
- ↑ Liu GJ, Lu MD, Xie XY, Xu HX, Xu ZF, Zheng YL, Liang JY, Wang W (2008). “Real-time contrast-enhanced ultrasound imaging of infected focal liver lesions”. J Ultrasound Med. 27 (4): 657–66. PMID 18359914.
- ↑ Kim, Kyoung Won; Choi, Byung Ihn; Park, Seong Ho; Kim, Ah Young; Koh, Young Hwan; Lee, Hyun Ju; Han, Joon Koo (2004). “Pyogenic hepatic abscesses: distinctive features from hypovascular hepatic malignancies on contrast-enhanced ultrasound with SH U 508A; early experience”. Ultrasound in Medicine & Biology. 30 (6): 725–733. doi:10.1016/j.ultrasmedbio.2004.03.006. ISSN 0301-5629.
- ↑ Syed MA, Kim TK, Jang HJ (2007). “Portal and hepatic vein thrombosis in liver abscess: CT findings”. Eur J Radiol. 61 (3): 513–9. doi:10.1016/j.ejrad.2006.11.022. PMID 17161932.
- ↑ Menias, Christine O.; Surabhi, Venkateswar R.; Prasad, Srinivasa R.; Wang, Hanlin L.; Narra, Vamsi R.; Chintapalli, Kedar N. (2008). “Mimics of Cholangiocarcinoma: Spectrum of Disease”. RadioGraphics. 28 (4): 1115–1129. doi:10.1148/rg.284075148. ISSN 0271-5333.
- ↑ Gollapudi P, Chejfec G, Zarling EJ (1992). “Spontaneous regression of hepatic pseudotumor”. Am. J. Gastroenterol. 87 (2): 214–7. PMID 1734701.
- ↑ Yoon KH, Ha HK, Lee JS, Suh JH, Kim MH, Kim PN, Lee MG, Yun KJ, Choi SC, Nah YH, Kim CG, Won JJ, Auh YH (1999). “Inflammatory pseudotumor of the liver in patients with recurrent pyogenic cholangitis: CT-histopathologic correlation”. Radiology. 211 (2): 373–9. doi:10.1148/radiology.211.2.r99ma36373. PMID 10228516.
- ↑ CHEDID, Marcio F.; KRUEL, Cleber R. P.; PINTO, Marcelo A.; GREZZANA-FILHO, Tomaz J. M.; LEIPNITZ, Ian; KRUEL, Cleber D. P.; SCAFFARO, Leandro A.; CHEDID, Aljamir D. (2017). “HEPATOCELLULAR CARCINOMA: DIAGNOSIS AND OPERATIVE MANAGEMENT”. ABCD. Arquivos Brasileiros de Cirurgia Digestiva (São Paulo). 30 (4): 272–278. doi:10.1590/0102-6720201700040011. ISSN 2317-6326.
- ↑ Luigi Grazioli, Lucio Olivetti, Giancarlo Mazza & Maria Pia Bondioni (2013). “MR Imaging of Hepatocellular Adenomas and Differential Diagnosis Dilemma”. International journal of hepatology. 2013: 374170. doi:10.1155/2013/374170. PMID 23606972.
- ↑ Lucas Maillette de Buy Wenniger, Valeska Terpstra & Ulrich Beuers (2010). “Focal nodular hyperplasia and hepatic adenoma: epidemiology and pathology”. Digestive surgery. 27 (1): 24–31. doi:10.1159/000268404. PMID 20357448.
- ↑ Christian Grieser, Ingo G. Steffen, Daniel Seehofer, Incken-Birthe Kramme, Robert Uktolseya, Christian Scheurig-Muenkler, Bernd Hamm & Timm Denecke (2013). “Histopathologically confirmed focal nodular hyperplasia of the liver: gadoxetic acid-enhanced MRI characteristics”. Magnetic resonance imaging. 31 (5): 755–760. doi:10.1016/j.mri.2012.11.006. PMID 23219272. Unknown parameter
|month=ignored (help) - ↑ Shahid M. Hussain, Turkan Terkivatan, Pieter E. Zondervan, Esmee Lanjouw, Sjoerd de Rave, Jan N. M. Ijzermans & Rob A. de Man (2004). “Focal nodular hyperplasia: findings at state-of-the-art MR imaging, US, CT, and pathologic analysis”. Radiographics : a review publication of the Radiological Society of North America, Inc. 24 (1): 3–17. doi:10.1148/rg.241035050. PMID 14730031. Unknown parameter
|month=ignored (help) - ↑ J. T. Ames, M. P. Federle & K. Chopra (2009). “Distinguishing clinical and imaging features of nodular regenerative hyperplasia and large regenerative nodules of the liver”. Clinical radiology. 64 (12): 1190–1195. doi:10.1016/j.crad.2009.07.015. PMID 19913129. Unknown parameter
|month=ignored (help) - ↑ Giovanni Morana, Luigi Grazioli, Miles A. Kirchin, Maria Pia Bondioni, Niccolo Faccioli, Alessandro Guarise & Gunther Schneider (2011). “Solid hypervascular liver lesions: accurate identification of true benign lesions on enhanced dynamic and hepatobiliary phase magnetic resonance imaging after gadobenate dimeglumine administration”. Investigative radiology. 46 (4): 225–239. doi:10.1097/RLI.0b013e3181feee3a. PMID 21102346. Unknown parameter
|month=ignored (help) - ↑ I. R. Wanless (1990). “Micronodular transformation (nodular regenerative hyperplasia) of the liver: a report of 64 cases among 2,500 autopsies and a new classification of benign hepatocellular nodules”. Hepatology (Baltimore, Md.). 11 (5): 787–797. PMID 2189821. Unknown parameter
|month=ignored (help) - ↑ I. R. Wanless (1996). “Nodular regenerative hyperplasia, dysplasia, and hepatocellular carcinoma”. The American journal of gastroenterology. 91 (5): 836–837. PMID 8633567. Unknown parameter
|month=ignored (help) - ↑ T. Ichikawa, M. P. Federle, L. Grazioli, J. Madariaga, M. Nalesnik & W. Marsh (1999). “Fibrolamellar hepatocellular carcinoma: imaging and pathologic findings in 31 recent cases”. Radiology. 213 (2): 352–361. doi:10.1148/radiology.213.2.r99nv31352. PMID 10551212. Unknown parameter
|month=ignored (help) - ↑ Jose Traila Campos, Claude B. Sirlin & Jin-Young Choi (2012). “Focal hepatic lesions in Gd-EOB-DTPA enhanced MRI: the atlas”. Insights into imaging. 3 (5): 451–474. doi:10.1007/s13244-012-0179-7. PMID 22700119. Unknown parameter
|month=ignored (help) - ↑ Christine Sempoux, Ghalib Jibara, Stephen C. Ward, Cathy Fan, Lihui Qin, Sasan Roayaie, M. Isabel Fiel, Myron Schwartz & Swan N. Thung (2011). “Intrahepatic cholangiocarcinoma: new insights in pathology”. Seminars in liver disease. 31 (1): 49–60. doi:10.1055/s-0031-1272839. PMID 21344350. Unknown parameter
|month=ignored (help) - ↑ Nathalie Guedj, Pierre Bedossa & Valerie Paradis (2010). “[Pathology of cholangiocarcinoma]”. Annales de pathologie. 30 (6): 455–463. doi:10.1016/j.annpat.2010.10.004. PMID 21167432. Unknown parameter
|month=ignored (help) - ↑ Y. Maetani, K. Itoh, C. Watanabe, T. Shibata, F. Ametani, H. Yamabe & J. Konishi (2001). “MR imaging of intrahepatic cholangiocarcinoma with pathologic correlation”. AJR. American journal of roentgenology. 176 (6): 1499–1507. doi:10.2214/ajr.176.6.1761499. PMID 11373220. Unknown parameter
|month=ignored (help) - ↑ Riccardo Manfredi, Brunella Barbaro, Gabriele Masselli, Amorino Vecchioli & Pasquale Marano (2004). “Magnetic resonance imaging of cholangiocarcinoma”. Seminars in liver disease. 24 (2): 155–164. doi:10.1055/s-2004-828892. PMID 15192788. Unknown parameter
|month=ignored (help) - ↑ P. Soyer, B. Van Beers, C. Grandin, J. Pringot & M. Levesque (1993). “Primary lymphoma of the liver: MR findings”. European journal of radiology. 16 (3): 209–212. PMID 8508837. Unknown parameter
|month=ignored (help) - ↑ E. S. Zafrani & P. Gaulard (1993). “Primary lymphoma of the liver”. Liver. 13 (2): 57–61. PMID 8510487. Unknown parameter
|month=ignored (help) - ↑ Saravanan Namasivayam, Diego R. Martin & Sanjay Saini (2007). “Imaging of liver metastases: MRI”. Cancer imaging : the official publication of the International Cancer Imaging Society. 7: 2–9. doi:10.1102/1470-7330.2007.0002. PMID 17293303.
- ↑ Daichi Hayashi, Jaroslaw N. Tkacz, Stephen Hammond, Brooke C. Devenney-Cakir, Souhil Zaim, Nadia Bouzegaou, Souhila Ounadjela & Ali Guermazi (2011). “Gastroenteropancreatic neuroendocrine tumors: multimodality imaging features with pathological correlation”. Japanese journal of radiology. 29 (2): 85–91. doi:10.1007/s11604-010-0522-1. PMID 21359932. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Natural History, Complications and Prognosis
Overview
There is 30% bleeding risk for hepatocellular adenoma if left untreated. The natural course of hepatocellular adenoma after cessation of oral contraceptive use remains unclear, it may regress or remain stable in size. Complications include bleeding, rupture and malignant transformation. The prognosis is usually good after discontinuation of oral contraceptives, as it may regress. In cases where it does not regress after oral contraception withdrawal, surgery is the management of choice.
Natural history
- The hepatocellular adenoma if left untreated, there is 30% bleeding risk.[1]
- The natural course of hepatocellular adenoma after cessation of oral contraceptive use remains unclear, it may regress or remain stable in size.[2]
- Obesity and metabolic syndrome may facilitate the progression of hepatocellular adenoma, therefore weight loss may help in stability or regression of the lesion.[3]
Complications
- The complications of hepatocellular adenoma include;[4][5][6][7][8]
- Bleeding and rupture
- The presence of hepatocellular adenoma can be complicated by growth and rupture.
- Bleeding in hepatocellular adenoma ranges from small subclinical bleed to life threatening intraperitoneal rupture, resulting in hemorrhagic shock requiring emergency care.
- Bleeding and rupture in hepatocellular adenoma are associated with tumor size and use of oral contraceptives.
- There is also increased risk of rupture in pregnancy because of increased hormone levels.
- The risk of rupture does not seem to be associated with tumor number.
- The risk of bleeding is directly correlated with size of tumor and > 5cm hepatocellular adenomas have a high risk of hemorrhage.
- Malignant transformation
- The malignant transformation into hepatocellular carcinoma is a serious but rare complication of hepatocellular adenoma.
- The specific risk factors for hepatocellular carcinoma include hepatocellular adenoma nodules with aberrant nuclear beta catenin expression. This subgroup seems overpresented in male patients.
- Male sex and tumor size >5cm have been identified as risk factors associated with higher rate of malignant transformation.[4]
Prognosis
- The prognosis is usually good for hepatocellular adenoma.
- When diagnosed, the discontinuation of oral contraception or androgen intake leads to regression of hepatocellular adenoma.
- In cases that do not regress after the withdrawal of oral contraception or androgen, surgical treatment is the management of choice.[9]
References
- ↑ Fauci, Anthony (2008). Harrison’s principles of internal medicine. New York: McGraw-Hill Medical. ISBN 978-0071466332.
- ↑ C. Bunchorntavakul, R. Bahirwani, D. Drazek, M. C. Soulen, E. S. Siegelman, E. E. Furth, K. Olthoff, A. Shaked & K. R. Reddy (2011). “Clinical features and natural history of hepatocellular adenomas: the impact of obesity”. Alimentary pharmacology & therapeutics. 34 (6): 664–674. doi:10.1111/j.1365-2036.2011.04772.x. PMID 21762186. Unknown parameter
|month=ignored (help) - ↑ David Q. Wang, Laurie M. Fiske, Caroline T. Carreras & David A. Weinstein (2011). “Natural history of hepatocellular adenoma formation in glycogen storage disease type I”. The Journal of pediatrics. 159 (3): 442–446. doi:10.1016/j.jpeds.2011.02.031. PMID 21481415. Unknown parameter
|month=ignored (help) - ↑ 4.0 4.1 “Radiopedia 2015 Hepatic adenoma [Dr Matt A. Morgan and Dr Koshy Jacob]”.
- ↑ Aamann L, Schultz N, Fallentin E, Hamilton-Dutoit S, Vogel I, Grønbæk H (2015). “[Hepatocellular adenoma – new classification and recommendations]”. Ugeskr Laeger. 177 (12). PMID 25786843.
- ↑ Jeremiah L. Deneve, Timothy M. Pawlik, Steve Cunningham, Bryan Clary, Srinevas Reddy, Charles R. Scoggins, Robert C. G. Martin, Michael D’Angelica, Charles A. Staley, Michael A. Choti, William R. Jarnagin, Richard D. Schulick & David A. Kooby (2009). “Liver cell adenoma: a multicenter analysis of risk factors for rupture and malignancy”. Annals of surgical oncology. 16 (3): 640–648. doi:10.1245/s10434-008-0275-6. PMID 19130136. Unknown parameter
|month=ignored (help) - ↑ Maarten G. Thomeer, Mirelle Broker, Joanne Verheij, Michael Doukas, Turkan Terkivatan, Diederick Bijdevaate, Robert A. De Man, Adriaan Moelker & Jan N. IJzermans (2016). “Hepatocellular adenoma: when and how to treat? Update of current evidence”. Therapeutic advances in gastroenterology. 9 (6): 898–912. doi:10.1177/1756283X16663882. PMID 27803743. Unknown parameter
|month=ignored (help) - ↑ Bunchorntavakul, C.; Bahirwani, R.; Drazek, D.; Soulen, M. C.; Siegelman, E. S.; Furth, E. E.; Olthoff, K.; Shaked, A.; Reddy, K. R. (2011). “Clinical features and natural history of hepatocellular adenomas: the impact of obesity”. Alimentary Pharmacology & Therapeutics. 34 (6): 664–674. doi:10.1111/j.1365-2036.2011.04772.x. ISSN 0269-2813.
- ↑ Sung W. Cho, J. Wallis Marsh, Jennifer Steel, Shane E. Holloway, Jason T. Heckman, Erin R. Ochoa, David A. Geller & T. Clark Gamblin (2008). “Surgical management of hepatocellular adenoma: take it or leave it?”. Annals of surgical oncology. 15 (10): 2795–2803. doi:10.1245/s10434-008-0090-0. PMID 18696154. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Diagnosis
Diagnosis
History and Symptoms | Physical Examination | Laboratory Findings | Chest X Ray | CT | MRI | Ultrasound | Other Imaging Findings | Other Diagnostic Studies
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Sabawoon Mirwais, M.B.B.S, M.D.[3]