

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Oral thrush
Introduction
For patient information page on this topic, click here.
Synonyms and keywords: OPC; thrush; oral thrush; candidiasis of the mouth and throat; candidosis; oral moniliasis; oropharyngeal candidiasis
Overview
Overview
Oral candidiasis of the mouth and throat is a fungal infection that occurs when there is an overgrowth of candida. Candida yeasts normally live on the skin or mucous membranes in small amounts. However, if the environment inside the mouth or throat becomes imbalanced, the yeasts can multiply and cause symptoms. Candida overgrowth can also develop in the esophagus, and cause esophageal candidiasis.
Historical prespective
In 1839, B. Lagenbeck from Germany described a yeast-like fungus for the first time in the human oral infection thrush and its ability to cause it.
Pathophysiology
Candida species are normal inhabitants of the mouth, throat, and the rest of the gastrointestinal tract. Usually, candida yeasts live in and on the body in small amounts and do not cause any harm. However, the use of certain medications or immunosuppression can cause Candida to multiply, which may cause symptoms of infection.
Causes
Oral candidiasis is an infection of yeast fungus, Candida albicans, (or, less commonly, Candida glabrata or Candida tropicalis or C. parapsilosis or C. krusei or other candida species) in the mucous membranes of the mouth.
Differentiating oral candidiasis from other diseases
Oropharyngeal candidiasis must be differentiated from its different kinds and from various other diseases that can cause stomatitis or glossitisز
Epidemiology and Demographics
Oral candidiasis is not common among the general population but is frequently diagnosed in the immunocompromised patients.
Risk Factors
People who have diabetes and had high blood sugar levels are more likely to get thrush in the mouth (oral thrush) because the extra sugar in saliva acts as a substrate for Candida. High doses of antibiotics or extended use of antibiotics also increases the risk of oral thrush. Antibiotics kill some of the healthy bacteria that help keep Candida from growing too much. People with poorly fitting dentures are also more likely to get thrush.
Natural History, Complications and Prognosis
There are no sequelae with appropriate antifungal therapy. In contrast, among immunocompromised patients with disseminated infections, the mortality rate is almost 50%. Thrush in infants may be painful but is rarely serious. Because of discomfort, it can interfere with eating. If it does not resolve on its own within 2 weeks, a pediatrician should be notified. In adults, thrush that occurs in the mouth can be cured. However, the long-term outlook is dependent on immune status and the cause of the immune deficit.
In patients with a weakened immune system (for example, HIV-positive or receiving chemotherapy), Candida can spread throughout body, causing infection in esophagus (esophagitis), brain (meningitis), heart (endocarditis), joints (arthritis), or eyes (endophthalmitis).
Diagnosis
History and Symptoms
Adults may experience discomfort or burning in the mouth. Symptoms of candidiasis in the esophagus may include pain and dysphagia (difficult swallowing). Candida infections of the mouth and throat can manifest in a variety of ways. The most common symptom of oral thrush is white patches or plaques on the tongue and other oral mucous membranes.
Physical Examination
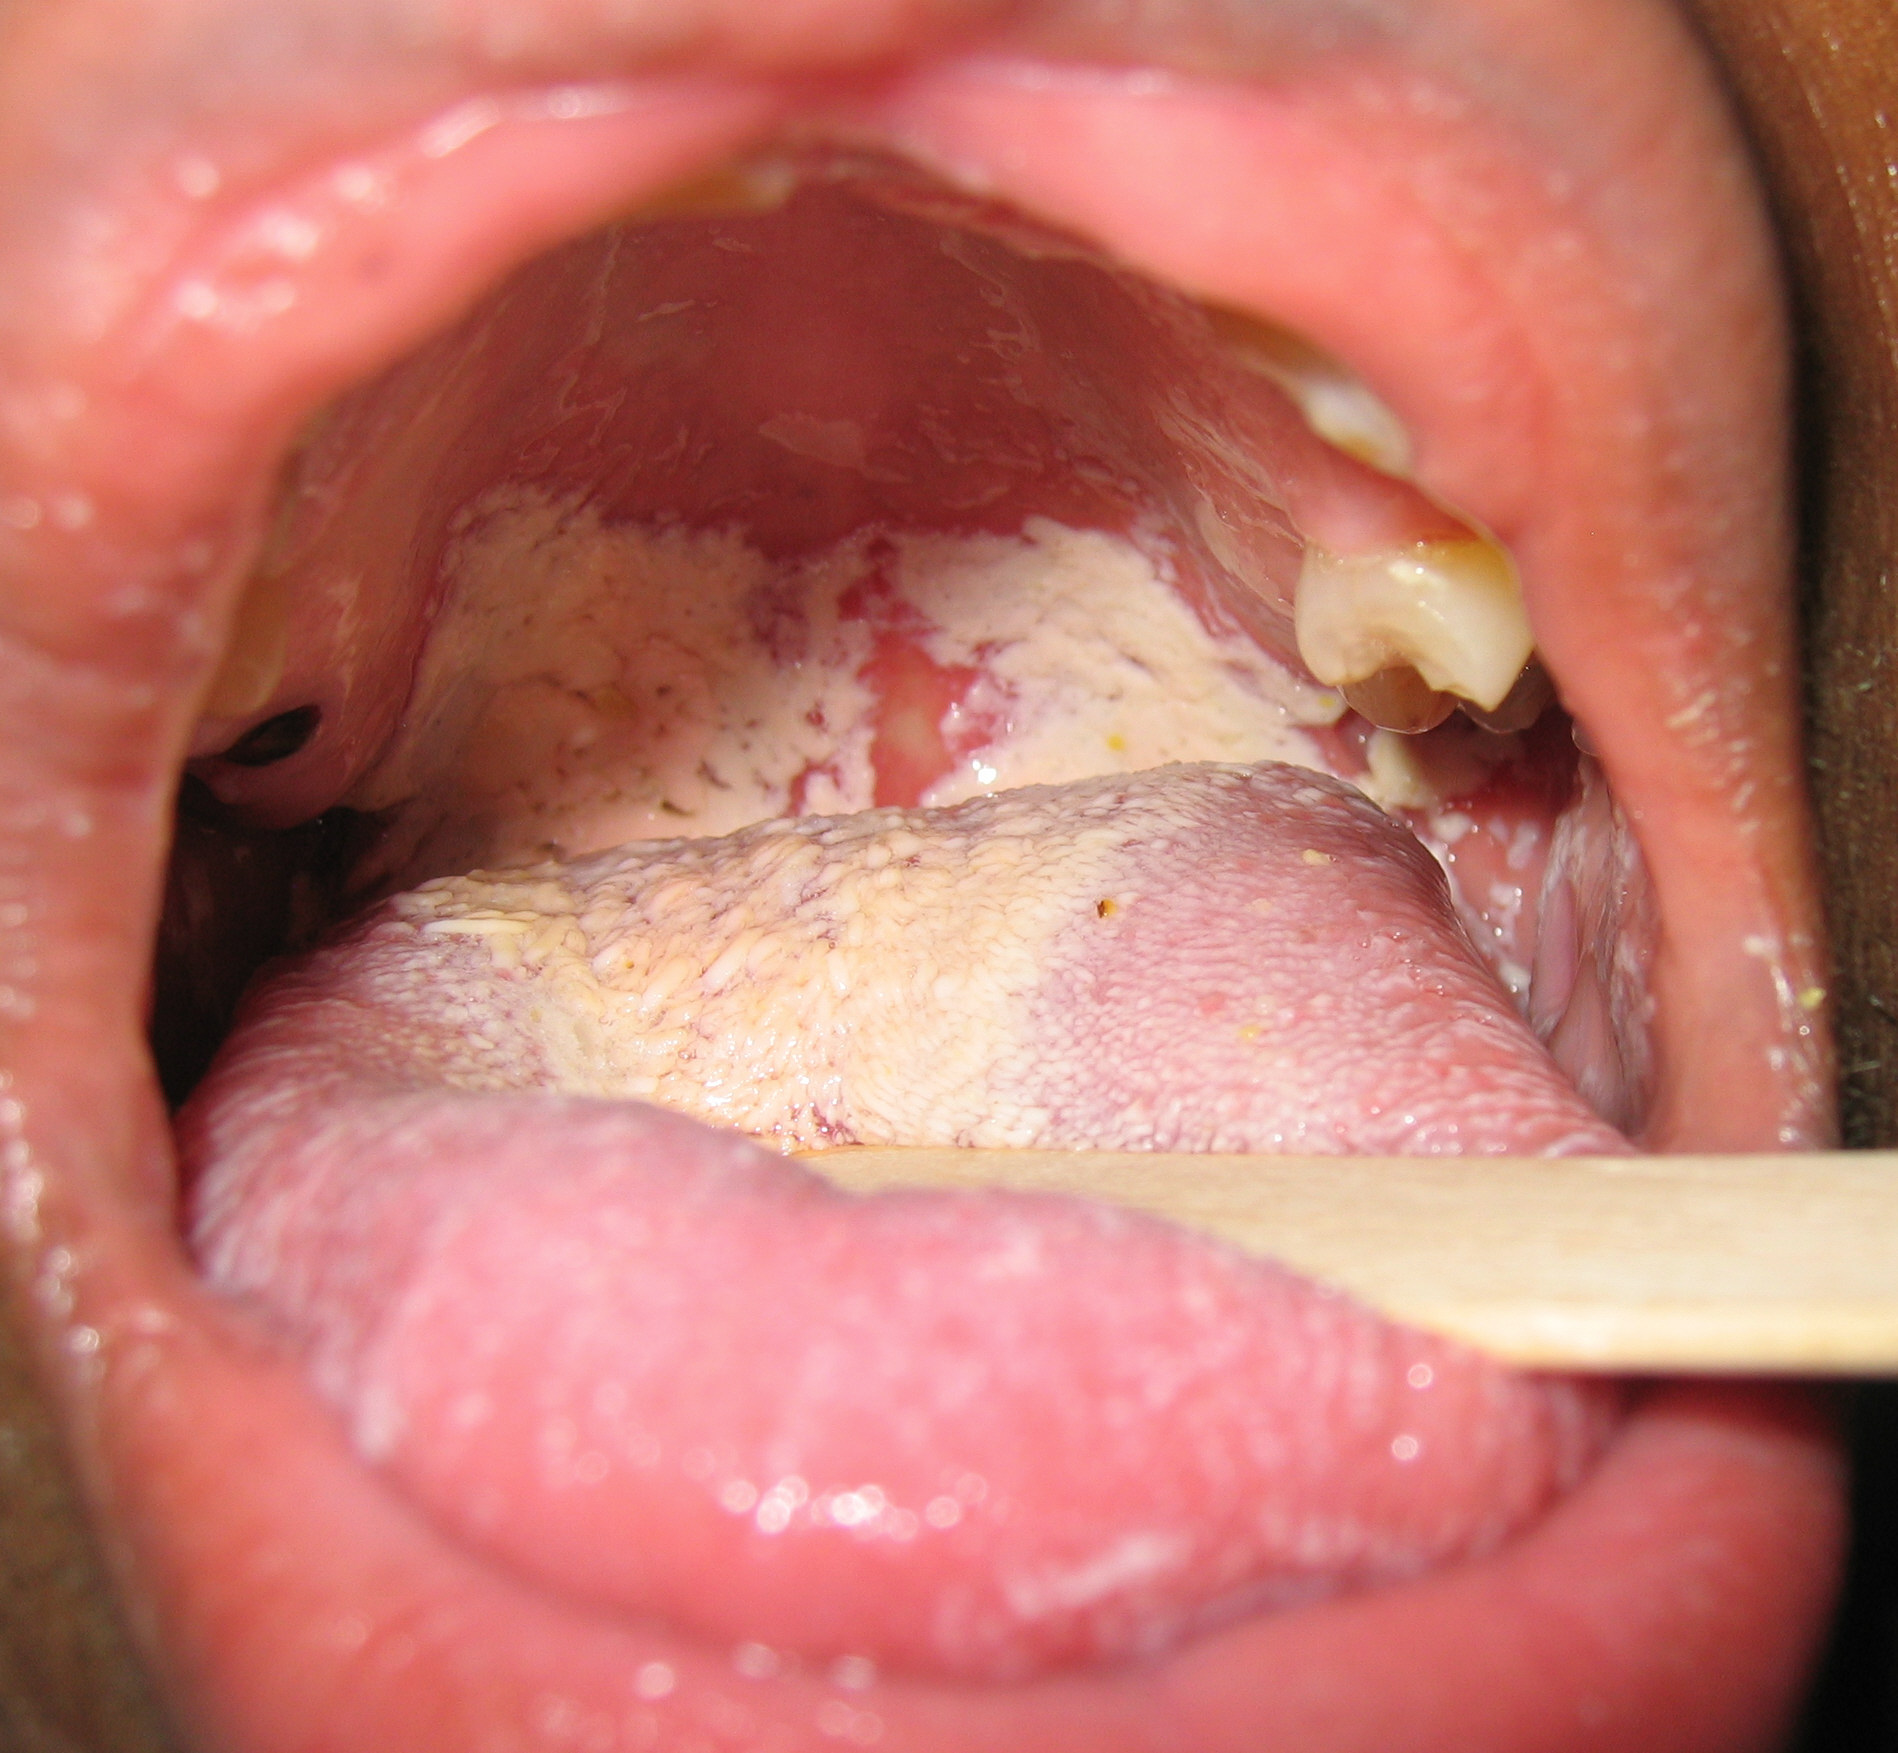
Oral infections of candida usually appear as thick white or cream color deposits. Underlying the deposits the mucosa of the mouth may appear inflamed (red and possibly slightly raised). Oral lesions are painless, white patches in the mouth.
Laboratory Findings
A healthcare provider diagnoses the infection based on symptoms, and by taking a scraping of affected areas to examine under a microscope. A culture may also be performed; however, because Candida organisms are normal inhabitants of the human mouth, a positive culture by itself does not make the diagnosis.
Treatment
Medical Therapy
Oral candidiasis can be treated with topical anti-fungal drugs, such as nystatin (Mycostatin), miconazole or amphotericin B. Patients who are immunocompromised, either with HIV/AIDS or as a result of chemotherapy, may require systemic treatment with oral or intravenous administered antifungals.
Primary Prevention
Good oral hygiene practices may help to prevent oral thrush in people with weakened immune systems. Some studies have shown that chlorhexidine (CHX) mouthwash can help to prevent oral candidiasis in people undergoing cancer treatment. People who use inhaled corticosteroids may be able to reduce the risk of developing thrush by washing out the mouth with water or mouthwash after using an inhaler.
Secondary prevention
Candida is usually a self-limiting disease unless concurrent immunosuppression is present.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Historical Perspective
Overview
In 1839, B. Lagenbeck from Germany described a yeast-like fungus for the first time in the human oral infection thrush and its ability to cause it.
Historical Perspective
- In 1839, B. Lagenbeck from Germany described a yeast-like fungus for the first time in the human oral infection thrush and its ability to cause it.[1]
- In 1923 the Candida albicans was described by Christine Marie Berkhout. Over the years the classification of the genera and species has evolved. Obsolete names for this genus include Mycotorula and Torulopsis. The species has also been known in the past as Monilia albicans and Oidium albicans. The current classification is nomen conservandum, which means the name is authorized for use by the International Botanical Congress (IBC).
- The full current taxonomic classification is available at Candida albicans.
- The genus Candida includes about 150 different species. However, only a few of those are known to cause human infections. c. albicans is the most significant pathogenic (disease-causing) species. Other Candida species causing diseases in humans include c. tropicalis, c. glabrata, c. krusei, c. parapsilosis, c. dubliniensis, and c. lusitaniae.
References
- ↑ Barnett JA (2008). “A history of research on yeasts 12: medical yeasts part 1, Candida albicans”. Yeast. 25 (6): 385–417. doi:10.1002/yea.1595. PMID 18509848.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Dima Nimri, M.D. [2], Aravind Kuchkuntla, M.B.B.S[3], Ahmed Younes M.B.B.CH [4]
Pathophysiology
Overview
Candida is a normal commensal of the skin and mucous membranes. The balance between the virulence of the fungus and the host immune defense is responsible avoiding opportunistic infection of candida. Deficiency of cell-mediated immunity or poor general status are the main risk factors for having opportunistic candidiasis. Candidiasis is usually localized to skin and mucous membranes. In rare cases, candidiasis can spread causing candidemia and distant infection. These cases are usually associated with deficient immunity . C. albicans is the main species causing infection in humans more than any other candida species.
Pathophysiology
Pathogenesis
Candida is a normal commensal of skin and mucous membranes. A competent immune system and an intact regenerating healthy skin prevent the virulence of Candida.
Candida Virulence factors
The main virulence factors that mediate the infection:[1]
- Secreting molecules that mediate adherence into host cells
- Production of hydrolases which has a lytic effect on tissues and facilitate the invasion by the fungus.
- Polymorphism: Candida has the ability to grow either as pseudohyphae (elongated ellipsoid form) or in a yeast form (rounded to oval budding form. While the role of polymorphism is not clearly understood in the virulence of Candida, it’s noted that the species that are capable of producing the most severe form of the disease has this ability.
- Biofilm production: which means the ability to form a thick layer of the organism on the mucosal surfaces or even on catheters and dentures.
Any condition that compromises cell-mediated immunity, worsens the general status of the patient or provide a favorable medium for Candida to form biofilms put the patient at increased risk for having candidiasis.[2]
Candidal gene VPS4 plays an important role in mucosal candidiasis specifically. Moreover, fungi with mutations affecting this gene were found to be less virulent.[3][4]
Gross Pathology
Pseudomembranous candidiasis:
On speculum examination typical curdy white discharge is present. Usually present in newborns or in patients with deficient immunity, administering corticosteroids, etc.
Atrophic candidiasis:
Appears as erythema or edema without the characteristic white plaques. Usually, seen in patients with dental dentures.[5]
Chronic hyperplastic candidiasis (Candidal leukoplakia):
Persistent tough, adherent, white lesions that are indistinguishable from other leukoplakia except through biopsy. Seen more in smokers, patients with iron deficiency anemia or deficient cell-mediated immunity.[6][5]
Chronic mucocutaneous candidiasis (CMCC):
- CMCC is a syndrome characterized by chronic or recurrent superficial candida infection in the skin and mucous membranes in association with endocrinal and autoimmune diseases.[7]
- Characterized by the inability of T cells to react to candidal antigens.
- Presents with recurrent or chronic candidal infections. Infection is usually superficial though invasive candidiasis is encountered especially in immunocompromised patients.[8]
- Endocrinopathies as hypoparathyroidism and adrenal insufficiency may accompany chronic candidiasis.
-
-
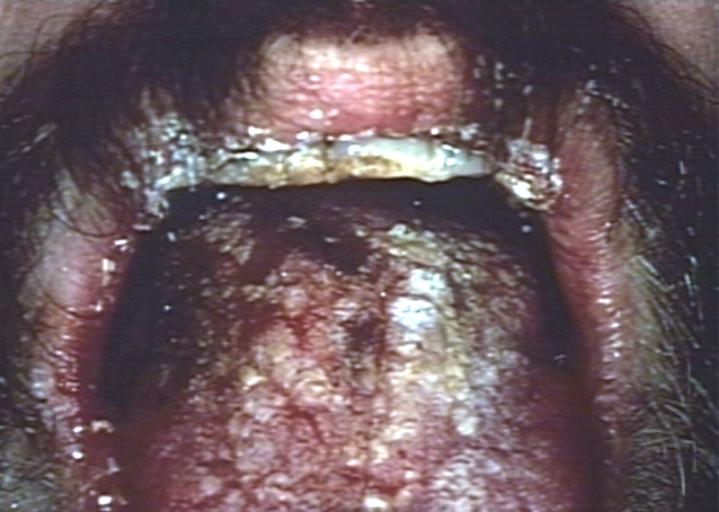 Oral manifestations of HIV infection and AIDS. Chronic oral candidiasis in patient with AIDS. Image courtesy of Professor Peter Anderson DVM PhD and published with permission. © PEIR, University of Alabama at Birmingham, Department of Pathology
-
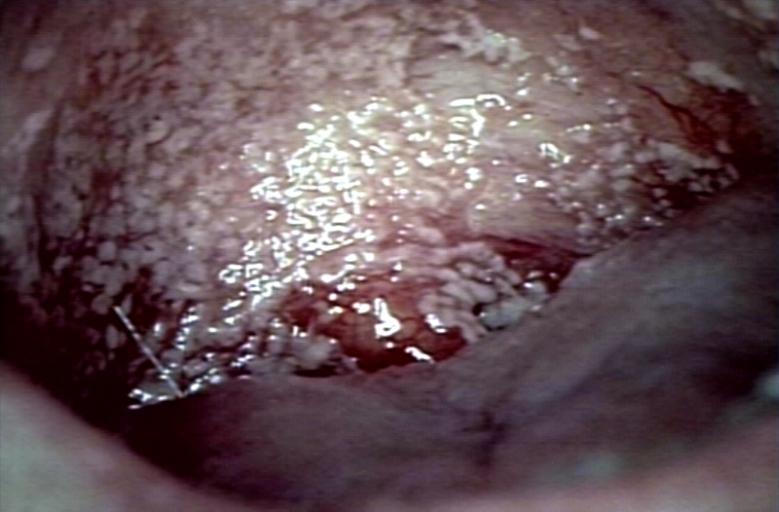 Soft palate showing extensive oral candidiasis in patient with AIDS. Image courtesy of Professor Peter Anderson DVM PhD and published with permission. © PEIR, University of Alabama at Birmingham, Department of Pathology
-
 Patient with swollen gingivae was diagnosed with oral moniliasis secondary to monocytic leukemia. From Public Health Image Library (PHIL). [9]


Microscopic pathology:
 |
`
- Microscopic examination of the wet mount with 10% KOH or saline demonstrates hyphae, pseudohyphae, and blastospores.
Videos
{{#ev:youtube|Qqb6vZtXxu8}}
References
- ↑ Mayer FL, Wilson D, Hube B (2013). “Candida albicans pathogenicity mechanisms”. Virulence. 4 (2): 119–28. doi:10.4161/viru.22913. PMC 3654610. PMID 23302789.
- ↑ Pappas PG (2006). “Invasive candidiasis”. Infect. Dis. Clin. North Am. 20 (3): 485–506. doi:10.1016/j.idc.2006.07.004. PMID 16984866.
- ↑ Rane HS, Hardison S, Botelho C, Bernardo SM, Wormley F, Lee SA (2014). “Candida albicans VPS4 contributes differentially to epithelial and mucosal pathogenesis”. Virulence. 5 (8): 810–8. doi:10.4161/21505594.2014.956648. PMID 25483774.
- ↑ Lee SA, Jones J, Hardison S, Kot J, Khalique Z, Bernardo SM, Lazzell A, Monteagudo C, Lopez-Ribot J (2009). “Candida albicans VPS4 is required for secretion of aspartyl proteases and in vivo virulence”. Mycopathologia. 167 (2): 55–63. doi:10.1007/s11046-008-9155-7. PMID 18814053.
- ↑ 5.0 5.1 Lynch DP (1994). “Oral candidiasis. History, classification, and clinical presentation”. Oral Surg. Oral Med. Oral Pathol. 78 (2): 189–93. PMID 7936588.
- ↑ “CHRONIC HYPERPLASTTC CANDIDIASIS—CANDIDAL LEUKOPLAKIA – CAWSON – 1968 – British Journal of Dermatology – Wiley Online Library”.
- ↑ Puel A, Cypowyj S, Bustamante J, Wright JF, Liu L, Lim HK, Migaud M, Israel L, Chrabieh M, Audry M, Gumbleton M, Toulon A, Bodemer C, El-Baghdadi J, Whitters M, Paradis T, Brooks J, Collins M, Wolfman NM, Al-Muhsen S, Galicchio M, Abel L, Picard C, Casanova JL (2011). “Chronic mucocutaneous candidiasis in humans with inborn errors of interleukin-17 immunity”. Science. 332 (6025): 65–8. doi:10.1126/science.1200439. PMC 3070042. PMID 21350122.
- ↑ Eyerich K, Foerster S, Rombold S, Seidl HP, Behrendt H, Hofmann H, Ring J, Traidl-Hoffmann C (2008). “Patients with chronic mucocutaneous candidiasis exhibit reduced production of Th17-associated cytokines IL-17 and IL-22”. J. Invest. Dermatol. 128 (11): 2640–5. doi:10.1038/jid.2008.139. PMID 18615114.
- ↑ “Public Health Image Library (PHIL)”.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Causes
Overview
C. albicans is the main species causing infection in humans more than any other candida species.
Causes:
Most common causes:
Candida albicans is the most common cause of oropharyngeal candidiasis.[1][2]
Less common causes:
Other candida strains can cause oropharyngeal candidiasis:[1][2]
References
- ↑ 1.0 1.1 Barchiesi F, Morbiducci V, Ancarani F, Scalise G (1993). “Emergence of oropharyngeal candidiasis caused by non-albicans species of Candida in HIV-infected patients”. Eur. J. Epidemiol. 9 (4): 455–6. PMID 8243605.
- ↑ 2.0 2.1 Sangeorzan JA, Bradley SF, He X, Zarins LT, Ridenour GL, Tiballi RN, Kauffman CA (1994). “Epidemiology of oral candidiasis in HIV-infected patients: colonization, infection, treatment, and emergence of fluconazole resistance”. Am. J. Med. 97 (4): 339–46. PMID 7942935.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Differentiating Oral Candidiasis from other Diseases
Overview
Oropharyngeal candidiasis must be differentiated from its different kinds and from various other diseases that can cause stomatitis or glossitis
Differential diagnosis
Oropharyngeal candidiasis must be differentiated from its different kinds and from various other diseases that can cause stomatitis or glossitis:[1][2]
- Aphthous ulcers
- Herpes simplex oral lesions
- Tumors of the tongue
- Autoimmune diseases[7]
- Behcet’s syndrome[8]
- CMV oral ulcers
- Blastomycosis oral lesions
- Crohn’s disease
- Agranulocytosis
- Fordyce’s spots
- Drug induced
- Burning mouth syndrome
- Syphilis
- Coxsackie virus accompanies involvement of the hands and the mouth
- HIV
- VZV or Chicken pox
Oral candidiasis must be differentiated from other diseases causing oral lesions such as leukoplakia and herpes simplex virus infection.
| Disease | Presentation | Risk Factors | Diagnosis | Affected Organ Systems | Important features | Picture |
|---|---|---|---|---|---|---|
| Diseases predominantly affecting the oral cavity | ||||||
| Oral Candidiasis |
|
|
|
Localized candidiasis
Invasive candidasis |
|
 |
| Herpes simplex oral lesions |
|
|
|
|
 | |
| Aphthous ulcers |
|
|
|
|
|
 |
| Squamous cell carcinoma |
|
|
 | |||
| Leukoplakia |
|
|
|
|
 | |
| Melanoma |
|
|
|
|
 | |
| Fordyce spots |
|
|
|
|
 | |
| Burning mouth syndrome |
|
|
||||
| Torus palatinus |
|
 | ||||
| Diseases involving oral cavity and other organ systems | ||||||
| Behcet’s disease |
|
|
|
 | ||
| Crohn’s disease |
|
|
|
|||
| Agranulocytosis |
|
|
||||
| Syphilis[11] |
|
|
|
 | ||
| Coxsackie virus |
|
|

| |||
| Chicken pox |
|
|
|
|
 | |
| Measles |
|
|
|
 | ||
References
- ↑ Mandell; Gouglas, Gordon; Bennett, John. Principles and Practice of Infectious Diseases. Harvard Medical School: WILEY MEDICAL. p. 383. ISBN 0-471-87643-7. Unknown parameter
|firs1t=ignored (help) - ↑ Scully C (1999). “A review of common mucocutaneous disorders affecting the mouth and lips”. Ann Acad Med Singapore. 28 (5): 704–7. PMID 10597357.
- ↑ R. Morgan, J. Tsang, N. Harrington & L. Fook (2001). “Survey of hospital doctors’ attitudes and knowledge of oral conditions in older patients”. Postgraduate medical journal. 77 (908): 392–394. PMID 11375454. Unknown parameter
|month=ignored (help) - ↑ D. Grady, J. Greene, T. E. Daniels, V. L. Ernster, P. B. Robertson, W. Hauck, D. Greenspan, J. Greenspan & S. Jr Silverman (1990). “Oral mucosal lesions found in smokeless tobacco users”. Journal of the American Dental Association (1939). 121 (1): 117–123. PMID 2370378. Unknown parameter
|month=ignored (help) - ↑ P. DeMatos, D. S. Tyler & H. F. Seigler (1998). “Malignant melanoma of the mucous membranes: a review of 119 cases”. Annals of surgical oncology. 5 (8): 733–742. PMID 9869521. Unknown parameter
|month=ignored (help) - ↑ Barry Ladizinski & Kachiu C. Lee (2014). “A nodular protuberance on the hard palate”. JAMA. 311 (15): 1558–1559. doi:10.1001/jama.2014.271. PMID 24737369. Unknown parameter
|month=ignored (help) - ↑ Magliocca KR, Fitzpatrick SG (2017) Autoimmune Disease Manifestations in the Oral Cavity. Surg Pathol Clin 10 (1):57-88. DOI:10.1016/j.path.2016.11.001 PMID: 28153136
- ↑ Dalghous AM, Freysdottir J, Fortune F (2006). “Expression of cytokines, chemokines, and chemokine receptors in oral ulcers of patients with Behcet’s disease (BD) and recurrent aphthous stomatitis is Th1-associated, although Th2-association is also observed in patients with BD”. Scand J Rheumatol. 35 (6): 472–5. PMID 17343257.
- ↑ Ann M. Gillenwater, Nadarajah Vigneswaran, Hanadi Fatani, Pierre Saintigny & Adel K. El-Naggar (2013). “Proliferative verrucous leukoplakia (PVL): a review of an elusive pathologic entity!”. Advances in anatomic pathology. 20 (6): 416–423. doi:10.1097/PAP.0b013e3182a92df1. PMID 24113312. Unknown parameter
|month=ignored (help) - ↑ Andrès E, Zimmer J, Affenberger S, Federici L, Alt M, Maloisel F. (2006). “Idiosyncratic drug-induced agranulocytosis: Update of an old disorder”. Eur J Intern Med. 17 (8): 529–35. Text “pmid 17142169” ignored (help)
- ↑ title=”By Internet Archive Book Images [No restrictions], via Wikimedia Commons” href=”https://commons.wikimedia.org/wiki/File:A_manual_of_syphilis_and_the_venereal_diseases%2C_(1900)_(14595882378).jpg“
- ↑ Feikin DR, Lezotte DC, Hamman RF, Salmon DA, Chen RT, Hoffman RE (2000). “Individual and community risks of measles and pertussis associated with personal exemptions to immunization”. JAMA. 284 (24): 3145–50. PMID 11135778.
- ↑ Ratnam S, West R, Gadag V, Williams B, Oates E (1996). “Immunity against measles in school-aged children: implications for measles revaccination strategies”. Can J Public Health. 87 (6): 407–10. PMID 9009400.
|}|}|}|}
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Epidemiology and Demographics
Overview
Oral candidiasis is not common among the general population but is frequently diagnosed in the immunocompromised patients.
Epidemiology and Demographics
- The infection is not very common in the general population.
- It is estimated that between 5% and 7% of infants less than one month old will develop oral candidiasis.
- The prevalence of oral candidiasis among AIDS patients is estimated to be between 9% and 31%, and studies have documented clinical evidence of oral candidiasis in nearly 20% of cancer patients.[1]
- Thrush is the fourth most common cause of nosocomial bloodstream infections.
- The incidence is 8 cases per 100,000 in the general population.
- There is a higher incidence among neonates and African-Americans.[2]
- Oleander (OPC) used to be a common opportunistic infection in HIV-infected persons (prior to the introduction of highly active antiretroviral therapy HAART).
- Nosocomial disease surveillance is conducted by NNIS in selected hospitals. Active population-based surveillance for candidemia is being conducted in selected U.S. sites.[3]
References
- ↑ Daniluk T, Tokajuk G, Stokowska W, Fiedoruk K, Sciepuk M, Zaremba ML, Rozkiewicz D, Cylwik-Rokicka D, Kedra BA, Anielska I, Górska M, Kedra BR (2006). “Occurrence rate of oral Candida albicans in denture wearer patients”. Adv Med Sci. 51 Suppl 1: 77–80. PMID 17458064.
- ↑ Campisi G, Pizzo G, Milici ME, Mancuso S, Margiotta V (2002). “Candidal carriage in the oral cavity of human immunodeficiency virus-infected subjects”. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 93 (3): 281–6. PMID 11925537.
- ↑ Reichart PA (2003). “Oral manifestations in HIV infection: fungal and bacterial infections, Kaposi’s sarcoma”. Med. Microbiol. Immunol. 192 (3): 165–9. doi:10.1007/s00430-002-0175-5. PMID 12684760.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Risk Factors
Overview
Uncontrolled diabetes are more likely to get oral thrush, because the extra glucose in saliva acts as a substrate for Candida. High doses of antibiotics or extended use of antibiotics also increases the risk of oral thrush. Antibiotics kill bacterial flora that compete with candida. People with poorly fitting dentures are also more likely to get thrush.
Risk Factors
- Thrush is commonly seen in infants.
- It is not considered abnormal in infants unless it lasts longer than 2 weeks.
- People who have uncontrolled diabetes are more likely to get oral thrush because the extra sugar in saliva acts as a substrate for Candida.
- High doses of antibiotics or extended use of antibiotics also increases the risk of oral thrush. Antibiotics kill bacterial flora that compete with candida.
- People with poorly fitting dentures are also more likely to get thrush.
At Risk Individuals[1]
- People with an immune deficiency (e.g. as a result of AIDS/HIV or chemotherapy treatment)
- Newborn babies
- Denture users
- Poorly controlled diabetes
- As a side effect of medication, most commonly having taken antibiotics. Inhaled corticosteroids for treatment of lung conditions (e.g, asthma or COPD) may also result in oral candidiasis which may be reduced by regularly rinsing the mouth with water after taking the medication.
- People with poor nutrition, specifically vitamin A, iron and folate deficiencies
- People with an immune deficiency (e.g. as a result of AIDS/HIV or chemotherapy treatment)
- Women undergoing hormonal changes, like pregnancy or those on birth control pills
- Organ transplantation patients
References
- ↑ Pappas PG, Kauffman CA, Andes DR, Clancy CJ, Marr KA, Ostrosky-Zeichner L, Reboli AC, Schuster MG, Vazquez JA, Walsh TJ, Zaoutis TE, Sobel JD (2016). “Clinical Practice Guideline for the Management of Candidiasis: 2016 Update by the Infectious Diseases Society of America”. Clin. Infect. Dis. 62 (4): e1–50. doi:10.1093/cid/civ933. PMC 4725385. PMID 26679628.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Natural History, Complications and Prognosis
Overview
There are no sequelae with appropriate antifungal therapy. In contrast, among immunocompromised patients with disseminated infections, the morbidity and mortality are very high.
Natural history
- Thrush in infants may be painful, but is rarely serious. If it does not resolve on its own within 2 weeks, a pediatrician must be notified.
- In adults, thrush that occurs in the mouth can be cured. However, the long-term outlook is dependent on a persons immune status and the cause of the immune deficit.
- In patients with immunodeficiency (HIV-positive or receiving chemotherapy), Candida can spread throughout body, causing esophagitis,meningitis, endocarditis, arthritis, or endophthalmitis.
Complications
Oropharyngeal candidiasis is rarely complicated except in immunocompromised individuals.
- Thrush in infants may cause weight loss because of dysphagia and discomfort associated with it.
- Spread to the trachea or the esophagus (causing respiratory distress or esophagitis) is rarely seen in otherwise healthy individuals.
- Systemic spread causing candidaemia and distant candida infection is frequently seen in immunocompromised individuals.
Prognosis
- Prognosis of oropharyngeal candidiasis is excellent in otherwise immunocompetent individuals with no serious sequelae in the majority of cases.
- Special attention should be given to immunocompromised patients as local spread to the trachea or esophagus or systemic spread causing candidaemia or distant candidiasis can be very serious with very high mortality rate.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1];Associate Editor(s)-in-Chief: Ahmed Younes M.B.B.CH [2]
Diagnosis
Diagnosis
History and Symptoms | Physical Examination | Laboratory Findings | Other Diagnostic Studies
Treatment
Treatment
Medical Therapy | Primary Prevention | Secondary Prevention | Cost-Effectiveness of Therapy | Future or Investigational Therapies
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-In-Chief: Prashanth Saddala M.B.B.S