

Health Dictionary
Reliable, easy-to-read patient information on common medical conditions — written in plain language, free of jargon, and grounded in current evidence. Browse the most frequent diagnoses, understand what they mean for everyday life, and learn which steps and questions help you have a focused conversation with your doctor.
Neuroblastomas
Introduction
For patient information click here.
Synonyms and keywords: Neuroblastomas; Sympathicoblastoma; Sympathicoblastomas; NB; Neuroblastoma sympathicum
Overview
Overview
Neuroblastoma is the most common solid extracranial cancer in childhood and is the most common cancer in infancy. It is a malignant tumor that arises from neural crest cells, which are normally involved in the development of the sympathetic nervous system and adrenal glands. It is usually located along the sympathetic nervous system structures including; adrenal glands, retroperitoneal organs, paravertebral sympathetic chain, organ of zuckerkandl and posterior mediastinum. It was first described by Rudolf Virchow in 1864 as an abdominal tumor in a child as “glioma“. James Homer Wright in 1910, described circular clumps of bone marrow (now named Homer-Wright pseudorosettes) and advanced the understanding that tumor originated from primitive neural cells and could metastasize to bone. International neuroblastoma pathology classification system is used for the classification of neuroblastoma tumors, which divides it into 02 main categories based on morphologic features of neuroblastoma tumors into: schwannian stroma poor and schwannian stroma rich/dominant. Neuroblastoma tumor cells secrete catecholamine by products including vanillylmandelic acid (VMA) and homovanillic acid (HVA) and vasoactive intestinal polypeptide (VIP) hormone as well. The various genes involved in pathogenesis of neuroblastoma include; NBPF10, KIF1B, ALK, LMO1 and PHOX2A genes. The most common genetic mutation is gain of chromosome 17q and MYCN oncogene amplification predicts more aggressive neuroblastoma. Neuroblastoma can also be associated with a number of syndromes including; neurofibromatosis type 1, beckwith-weidemann syndrome and hirschsprung disease. On gross pathology, the characteristic finding of neuroblastoma is a well defined, bulky and tan colored mass, that can be associated with fibrous pseudocapsule, necrosis or hemorrhage. On microscopic picture, the presence of round blue cells separated by thin fibrous septa are a characteristic finding. There are no known established causes for neuroblastoma. The risk factors for neuroblastomas diagnosed during infancy include; maternal anemia during pregnancy, neonatal respiratory distress syndrome and low 1 minute Apgar score. However, the risk factors for neuroblastoma cases diagnosed at age 1 year or above is not known. The overall incidence is 4.9 per 1,000,000 individuals in united states. Males are slightly more affected than females with 1.2:1 ratio. Neuroblastoma usually affects individuals of the caucasian race. Intra-abdominal neuroblastoma must be differentiated from other diseases that cause abdominal distension and constipation such as Wilms tumor and ganglioneuroma. Intra-thoracic neuroblastoma must be differentiated from other diseases that cause shortness of breath and chronic cough such as intrathoracic lymphoma and extra lobar pulmonary sequestration. There are no routine screening tests for neuroblastoma due to lack of any mortality benefits. Neuroblastoma may progress to develop fatigue, loss of appetite, joint pain and fever if left untreated. There is gradual development of site specific symptoms as the tumor size gradually increases. Complications of neuroblastoma include; persistent refractory diarrhea, horner’s syndrome, hypertension, transverse myelopathy, anemia and suppressed immunity. The prognosis of neuroblastoma is generally regarded as poor, depending on the tumor extent at the time of diagnosis. The other prognostic factors for nuroblastoma include; patient’s age, tumor stage and grade, genetic mutations and response to treatment. According to the conventional International Neuroblastoma Staging System (INSS), there are 6 stages of neuroblastoma based on the tumor size, lymph node involvement, and presence of metastasis. However, according to a newly proposed International Neuroblastoma Risk Group Staging System (INRGSS), there are four stages of neuroblastoma based on the extent of dissemination and image findings. Neuroblastoma patients are risk stratified according to the Children Oncology Group (COG) risk stratification system into a low risk group, an intermediate risk group, and a high risk group based on the tumor INSS stage, the patient’s age, tumor grade, and the amplification of MYCN gene. General neuroblastoma symptoms include; fever, irritability, fatigue, loss of appetite and weight loss. Other symptoms depending upon the anatomical location of neuroblastoma include; abdominal pain, distension and constipation (abdomen), shortness of breath, chronic cough & difficulty swallowing (posterior mediastinum), weakness, numbness, paralysis (retroperitoneum), visual defects, facial bruising (head & neck) and pallor, bone pain (bone marrow metastases). Physical examination findings of neuroblastoma include; fever, hypertension, tachycardia, pallor, ecchymoses, nystagmus, proptosis, ptosis, abdominal mass, brisk reflexes, sensory loss and ataxia. The laboratory findings in neuroblastoma include; ↓ hemoglobin, ↑ ferritin, ↑ catecholamine, ↑ dopamine, ↑ vanillylmandelic acid (VMA), ↑ homovanillic acid (HVA), ↑ lactate dehydrogenase and ↑ neuron-specific enolase levels. There are increased urinary catecholamine, vanillylmandelic acid (VMA) and homovanillic acid (HVA) levels. X ray findings of neuroblastoma include; intrathoracic or intraabdominal soft tissue mass, calcification, remodeling of surrounding ribs & vertebral bodies, thinning of surrounding pedicles and ill defined, metaphyseal, lucent bone lesions seen in metastases. CT scan of the neck, chest and abdomen is the gold standard test in neuroblastoma as it can localize the tumor and determine degree of involvement as well. CT scan in neuroblastoma can show the presence of; heterogeneous mass, calcification, necrosis, compression of surrounding vessels, invasion of psoas muscle & kidneys and swollen lymph nodes. MRI is considered the most useful modality in staging of neuroblastoma. It is superior to CT scan when determining marrow infiltration and intra spinal tumor extension. The definitive diagnosis of nueroblastoma is confirmed by a biopsy. Children oncology group (COG) risk stratification system determines the protocol of management used for neuroblastoma patients. COG risk stratification system divides the patients into 03 groups: low risk, intermediate risk and high risk patients. Low risk neuroblastoma patients are usually managed by either observation or surgical resection of the tumor. Intermediate risk patients are managed by neoadjuvant therapy in advance of a definitive surgical resection. High risk neuroblastoma patients are usually managed by a combination of surgery, chemotherapy, radiation therapy, hematopoietic stem cell transplantation, immunotherapy and isotretinoin. Surgical intervention is curative as a single therapeutic modality for management of low risk neuroblastoma patients. In intermediate risk patients, surgical intervention must be followed by chemotherapy. However, the benefits of surgery to achieve complete tumor resection in high risk patients with metastatic disease is not clearly demonstrated.
Historical Perspective
Neuroblastoma was first described by Rudolf Virchow in 1864 as an abdominal tumor in a child as “glioma“. Felix Marchand described characteristics of tumors from adrenal medulla and sympathetic nervous system in 1891. James Homer wright in 1910, described circular clumps of bone marrow ( now named “Homer-Wright pseudorosettes) and advanced the understanding that tumor originated from primitive neural cells and could metastasize to bone.
Classification
International neuroblastoma pathology classification system is used for the classification of neuroblastic tumors. It is subdivided in 02 main categories based on the morphologic features of neuroblastic tumors into; schwannian stroma-poor and schwannian stroma-rich/dominant.
Pathophysiology
Neuroblastoma arises from the neural crest cells, which are normally involved in development of sympathetic nervous system and adrenal glands. It is frequently located along the sympathetic nervous system structures including; adrenal glands, retroperitoneal organs, organ of zuckerkandl, paravertebral sympathetic chain and posterior mediastinum among others. Neuroblastoma tumor cells secrete catecholamine by products including vanillylmandelic acid (VMA) and homovanillic acid (HVA) and vasoactive intestinal polypeptide (VIP) hormone as well. It can metastasize to bone, liver, lungs and brain. The various genes involved in pathogenesis of neuroblastoma include; NBPF10, KIF1B, ALK, LMO1 and PHOX2A genes. The most common genetic mutation is gain of chromosome 17q and MYCN oncogene amplification predicts more aggressive neuroblastoma. Neuroblastoma can also be associated with a number of syndromes including; neurofibromatosis type 1, beckwith-wiedemann syndrome and hirschsprung disease. On gross pathology, the characteristic finding of neuroblastoma is a well defined, bulky and tan colored mass, that can be associated with fibrous pseudocapsule, necrosis or hemorrhage. On microscopic picture, the presence of round blue cells separated by thin fibrous septa are a characteristic finding.
Causes
There are no known established causes for neuroblastoma.
Differentiating Multiple Myeloma from other Diseases
Intra-abdominal neuroblastoma must be differentiated from other diseases that cause abdominal distension and constipation such as Wilms tumor and ganglioneuroma. Intra-thoracic neuroblastoma must be differentiated from other diseases that cause shortness of breath and chronic cough such as intrathoracic lymphoma and extra lobar pulmonary sequestration.
Epidemiology and Demographics
Neuroblastoma is the most common solid extracranial cancer in childhood and is the most common cancer in infancy. The overall incidence is 4.9 per 1,000,000 individuals in united states. Males are slightly more affected than females with 1.2:1 ratio. Neuroblastoma usually affects individuals of the caucasian race.
Risk Factors
The risk factors for neuroblastomas diagnosed during infancy include; maternal anemia during pregnancy, neonatal respiratory distress syndrome and low 1 minute Apgar score. However, the risk factors for neuroblastoma cases diagnosed at age 1 year or above is not known.
Screening
There is insufficient evidence to recommend the routine screening for neuroblastoma as it has no mortality benefits.
Natural History, Complications and Prognosis
Neuroblastoma may progress to develop fatigue, loss of appetite, joint pain and fever if left untreated. There is gradual development of site specific symptoms as the tumor size gradually increases. Complications of neuroblastoma include; persistent refractory diarrhea, horner’s syndrome, hypertension, transverse myelopathy, anemia and suppressed immunity. The prognosis of neuroblastoma is generally regarded as poor, depending on the tumor extent at the time of diagnosis. The other prognostic factors for nuroblastoma include; patient’s age, tumor stage and grade, genetic mutations and response to treatment.
Diagnosis
Staging
According to the conventional International Neuroblastoma Staging System (INSS), there are 6 stages of neuroblastoma based on the tumor size, lymph node involvement, and presence of metastasis. However, according to a newly proposed International Neuroblastoma Risk Group Staging System (INRGSS), there are four stages of neuroblastoma based on the extent of dissemination and image findings. Neuroblastoma patients are risk stratified according to the Children Oncology Group (COG) risk stratification system into a low risk group, an intermediate risk group, and a high risk group based on the tumor INSS stage, the patient’s age, tumor grade, and the amplification of MYCN gene.
History and Symptoms
A detailed history of presenting symptoms, family history and other associated symptoms should be undertaken when evaluating a patient of neuroblastoma. General neuroblastoma symptoms include; fever, irritability, fatigue, loss of appetite and weight loss. Other symptoms depending upon the anatomical location of neuroblastoma include; abdominal pain, distension and constipation (abdomen), shortness of breath, chronic cough & difficulty swallowing (posterior mediastinum), weakness, numbness, paralysis (retroperitoneum), visual defects, facial bruising (head & neck) and pallor, bone pain (bone marrow metastases).
Physical Examination
Physical examination findings of neuroblastoma include; fever, hypertension, tachycardia, pallor, ecchymoses, nystagmus, proptosis, ptosis, abdominal mass, brisk reflexes, sensory loss and ataxia.
Laboratory Findings
The laboratory findings in neuroblastoma include; ↓ hemoglobin, ↑ ferritin, ↑ catecholamine, ↑ dopamine, ↑ vanillylmandelic acid (VMA), ↑ homovanillic acid (HVA), ↑ lactate dehydrogenase and ↑ neuron-specific enolase levels. There are increased urinary catecholamine, vanillylmandelic acid (VMA) and homovanillic acid (HVA) levels.
X Ray
X ray findings of neuroblastoma include; intrathoracic or intraabdominal soft tissue mass, calcification, remodeling of surrounding ribs & vertebral bodies, thinning of surrounding pedicles and ill defined, metaphyseal, lucent bone lesions seen in metastases.
CT
CT scan of the neck, chest and abdomen is the gold standard test in neuroblastoma as it can localize the tumor and determine degree of involvement as well. CT scan in neuroblastoma can show the presence of; heterogeneous mass, calcification, necrosis, compression of surrounding vessels, invasion of psoas muscle & kidneys and swollen lymph nodes.
MRI
MRI is considered the most useful modality in staging of neuroblastoma. It is superior to CT scan when determining marrow infiltration and intra spinal tumor extension.MRI findings in neuroblastoma patients include; hypointense heterogeneous mass on T1 weighted image, heterogeneous/hyperintense enhancement due to necrosis and cyst formation seen on T2 weighted images.
Echocardiography or Ultrasound
Ultrasound in the neuroblastoma shows heterogeneous solid masses due to vascular, necrotic and calcified content of the masses. When it is present in the adrenal, it displaces the kidneys inferiorly.
Other Imaging Findings
Nuclear medicine studies used for diagnosis of neuroblastoma include fluorodeoxyglucose-18F positron emission tomography (18F- FDG PET) scan and metaiodobenzylguanidine (123I-MIBG) scintigraphy. 18F-FDG PET scan may distinguish stage 1 and 2 neuroblastoma from other differential diagnoses. 123I- MIBG scintigraphy distinguishes stage 3 and 4 neuroblastoma other differential diagnoses.
Other Diagnostic Studies
The definitive diagnosis of nueroblastoma is confirmed by a biopsy. Charecterstic findings for neuroblastoma on microscopic histopathological analysis can be found here.
Treatment
Medical Therapy
Children oncology group (COG) risk stratification system determines the protocol of management used for neuroblastoma patients. COG risk stratification system divides the patients into 03 groups: low risk, intermediate risk and high risk patients. Low risk neuroblastoma patients are usually managed by either observation or surgical resection of the tumor. Intermediate risk patients are managed by neoadjuvant therapy in advance of a definitive surgical resection. High risk neuroblastoma patients are usually managed by a combination of surgery, chemotherapy, radiation therapy, hematopoietic stem cell transplantation, immunotherapy and isotretinoin.
Surgery
Surgical intervention is curative as a single therapeutic modality for management of low risk neuroblastoma patients. In intermediate risk patients, surgical intervention must be followed by chemotherapy. However, the benefits of surgery to achieve complete tumor resection in high risk patients with metastatic disease is not clearly demonstrated.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]
Historical Perspective
Overview
Neuroblastoma was first described by Rudolf Virchow in 1864 as an abdominal tumor in a child as “glioma“. Felix Marchand described characteristics of tumors from adrenal medulla and sympathetic nervous system in 1891. James Homer wright in 1910, described circular clumps of bone marrow ( now named “Homer-Wright pseudorosettes) and advanced the understanding that tumor originated from primitive neural cells and could metastasize to bone.
Historical Perspective
- In 1864, Rudolf Virchow (german physician) first described an abdominal tumor in a child as “glioma“.[1]
- In 1891, Felix Marchand (german pathologist) described the characteristics of tumors from adrenal medulla and sympathetic nervous system.[2]
- In 1901, William Pepper described a neuroblastoma stage 4S presentation in infants that was metastatic to liver.
- In 1910, James Homer Wright described circular clumps of cells in bone marrow ( now named “Homer-Wright pseudorosettes) and advanced the understanding that tumor originated from primitive neural cells and could metastasize to bone.[3]
References
- ↑ . doi:10.5281/zenodo.1437314. Missing or empty
|title=(help) - ↑ Ritesh R. Kalaskar & Ashita R. Kalaskar (2016). “Neuroblastoma in early childhood: A rare case report and review of literature”. Contemporary clinical dentistry. 7 (3): 401–404. doi:10.4103/0976-237X.188579. PMID 27630510. Unknown parameter
|month=ignored (help) - ↑ Alexis B. Rothenberg, Walter E. Berdon, Giulio J. D’Angio, Darrell J. Yamashiro & Robert A. Cowles (2009). “Neuroblastoma-remembering the three physicians who described it a century ago: James Homer Wright, William Pepper, and Robert Hutchison”. Pediatric radiology. 39 (2): 155–160. doi:10.1007/s00247-008-1062-z. PMID 19034443. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Classification
Overview
International neuroblastoma pathology classification system is used for the classification of neuroblastic tumors. It is subdivided in 02 main categories based on the morphologic features of neuroblastic tumors into; schwannian stroma-poor and schwannian stroma-rich/dominant.
Classification
- International neuroblastoma pathology classification, a system based on the framework of Shimada classification with minor modifications is proposed for international use in classification of neuroblastic tumors. [1][2][3]
- It is a biologically relevant and pathologically significant classification system based on the morphologic features of neuroblastic tumors,i-e,neuroblastoma, ganglioneuroblastoma and ganglioneuroma.[4][5]
Neuroblastic tumors | |||||||||||||||||||||||||||||
| Schwannian stroma-poor group | Schwannian stroma-rich/dominant group | ||||||||||||||||||||||||||||
Undifferentiated neuroblastoma Poorly differentiated neuroblastoma Differentiating neuroblastoma |
Nodular ganglioneuroblastoma Intermixed ganglioneuroblastoma Maturing ganglioneuroma Mature ganglioneuroma | ||||||||||||||||||||||||||||
References
- ↑ Neuroblastoma, Ganglioneuroblastoma and Ganglioneuroma. Stanford Medicine Surgical Pathology Criteria(2015) http://surgpathcriteria.stanford.edu/srbc/neuroblastoma-ganglioneuroblastoma-ganglioneuroma/ Accessed on October, 5 2015
- ↑ Shimada H, Umehara S, Monobe Y, Hachitanda Y, Nakagawa A, Goto S; et al. (2001). “International neuroblastoma pathology classification for prognostic evaluation of patients with peripheral neuroblastic tumors: a report from the Children’s Cancer Group”. Cancer. 92 (9): 2451–61. PMID 11745303.
- ↑ Shimada, Hiroyuki; Ambros, Inge M.; Dehner, Louis P.; Hata, Jun-ichi; Joshi, Vijay V.; Roald, Borghild; Stram, Daniel O.; Gerbing, Robert B.; Lukens, John N.; Matthay, Katherine K.; Castleberry, Robert P. (1999). “The International Neuroblastoma Pathology Classification (the Shimada system)”. Cancer. 86 (2): 364–372. doi:10.1002/(SICI)1097-0142(19990715)86:2<364::AID-CNCR21>3.0.CO;2-7. ISSN 0008-543X.
- ↑ H. Shimada, I. M. Ambros, L. P. Dehner, J. Hata, V. V. Joshi, B. Roald, D. O. Stram, R. B. Gerbing, J. N. Lukens, K. K. Matthay & R. P. Castleberry (1999). “The International Neuroblastoma Pathology Classification (the Shimada system)”. Cancer. 86 (2): 364–372. PMID 10421273. Unknown parameter
|month=ignored (help) - ↑ H. Shimada, I. M. Ambros, L. P. Dehner, J. Hata, V. V. Joshi & B. Roald (1999). “Terminology and morphologic criteria of neuroblastic tumors: recommendations by the International Neuroblastoma Pathology Committee”. Cancer. 86 (2): 349–363. PMID 10421272. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Pathophysiology
Overview
Neuroblastoma arises from the neural crest cells, which are normally involved in development of sympathetic nervous system and adrenal glands. It is frequently located along the sympathetic nervous system structures including; adrenal glands, retroperitoneal organs, organ of zuckerkandl, paravertebral sympathetic chain and posterior mediastinum among others. Neuroblastoma tumor cells secrete catecholamine by products including vanillylmandelic acid (VMA) and homovanillic acid (HVA) and vasoactive intestinal polypeptide (VIP) hormone as well. It can metastasize to bone, liver, lungs and brain. The various genes involved in pathogenesis of neuroblastoma include; NBPF10, KIF1B, ALK, LMO1 and PHOX2A genes. The most common genetic mutation is gain of chromosome 17q and MYCN oncogene amplification predicts more aggressive neuroblastoma. Neuroblastoma can also be associated with a number of syndromes including; neurofibromatosis type 1, beckwith-wiedemann syndrome and hirschsprung disease. On gross pathology, the characteristic finding of neuroblastoma is a well defined, bulky and tan colored mass, that can be associated with fibrous pseudocapsule, necrosis or hemorrhage. On microscopic picture, the presence of round blue cells separated by thin fibrous septa are a characteristic finding.
Pathogenesis
- Neuroblastoma arises from neural crest cells, which are normally involved in the development of the sympathetic nervous system and adrenal glands.[1][2][3][4][5]
- Neuroblastoma is frequently located along the sympathetic nervous system structures. Specific sites may include:
- Adrenal glands (35% of the cases)
- Retroperitoneal organs (30% of the cases) such as:
- Posterior mediastinum (20% of the cases)
- Nerve tissues in the neck (1-5% of the cases)
- Nerve tissues in the pelvis (2-3% of the cases)
- Neuroblastoma tumor cells secrete catecholamine by-products such as:
- Vanillylmandelic acid (VMA)
- Homovanillic acid (HVA)
- Neuroblastoma tumor cells may secrete vasoactive intestinal peptide (VIP) hormone.
- Neuroblastoma may demonstrate spontaneous regression from an undifferentiated state to a completely benign cellular state.
- Spontaneous regression occurs only in neuroblastomas characterized by the following features:
- Near triploid number of chromosomes
- No MYCN amplification
- No loss of chromosome 1p
- Metastatic disease is common and has a variety of patterns:
Genetics
- Development of neuroblasotma is the result of multiple genetic mutations.[1][6][7][8][9][10][11]
- The vast majority of neuroblastoma cases are sporadic.
- 1-2% of neuroblastoma cases may demonstrate a familial predilection.
- Genes involved in the pathogenesis of neuroblastoma include:
- NBPF10 gene located on chromosome 1
- KIF1B gene located on chromosome 1
- ALK gene located on chromosome 2
- LMO1 gene located on chromosome 11
- PHOX2A gene located on chromosome 11
- Gain of chromosome 17q is the most common genetic mutation among neuroblastoma patients.
- MYCN oncogene (chromosome 2p24) amplification predicts a more aggressive nature of neuroblastomas.
- Deletion of chromosome 1p36 is associated with an increased recurrence rate following resection of localized neuroblastomas.
- Deletions of chromosome 11q is associated with poor prognosis among nueroblastoma patients.
Associated Conditions
Gross Pathology
- On gross pathology, a well defined, bulky, and tan colored mass is a characteristic finding of neuroblastoma.[1][12]
- Other associated findings of neuroblastoma on gross pathology may include:
- Fibrous pseudocapsule
- Necrosis
- Hemorrhage
- Calcification
Microscopic Pathology
- On microscopic histopathological analysis the presence of round blue cells separated by thin fibrous septa are characteristic findings of neuroblastoma.[13]
- Other findings of neuroblastoma on light microscopy may include:[12]
- On electron microscopy neuroblastoma is characterized by:
- Dendritic processes with longitudinally oriented microtubules
- Membrane bound electron-dense granules that contain catecholamines
- Presence of desmosomes
- Absence of glycogen
- On immunohistochemistry neuroblastoma is characterized by:
- Protein gene product (PGP) 9.5 +ve
- Monoclonal antibody NB84 +ve
- Synaptophysin +ve
- CD99 marker -ve
- Based on the degree of the cellular maturity and composition, neuroblastoma may be classified into three subtypes according to the International Neuroblastoma Pathology Classification which include:[14]
| Subtypes | Description |
|---|---|
| Undifferentiated Neuroblastoma | Completely formed by neuroblasts with no maturity of ganglion cells |
| Poorly Differentiated Neuroblastoma | Mostly formed by neuroblasts with less the 5% maturing ganglion cells |
| Differentiating Neuroblastoma |
Predominantly formed by neuroblasts but with more than 5% mature ganglion cells |
Gallery
- Illustrated below is a series of microscopic images demonstrating neuroblastoma:
-
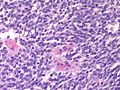 Adrenal neuroblastoma[12]
-
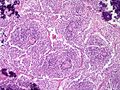 Adrenal neuroblastoma[12]
-
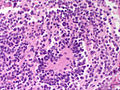
-
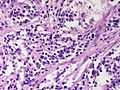 Adrenal neuroblastoma[12]
-
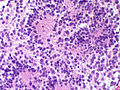 Adrenal neuroblastoma[12]
-
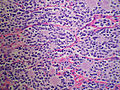 Adrenal neuroblastoma[12]
-
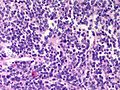 Adrenal neuroblastoma[12]
-
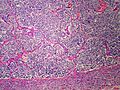 Adrenal neuroblastoma[12]
-
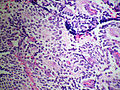 Adrenal neuroblastoma[12]


References
- ↑ 1.0 1.1 1.2 1.3 Neuroblastoma. Radiopaedia(2015) http://radiopaedia.org/articles/neuroblastoma Accessed on October, 5 2015
- ↑ Neuroblastoma Treatment for health professionals. National Cancer Institute (2015) http://www.cancer.gov/types/neuroblastoma/hp/neuroblastoma-treatment-pdq#link/_534_toc Accessed on October, 7 2015
- ↑ Nai-Kong V. Cheung & Michael A. Dyer (2013). “Neuroblastoma: developmental biology, cancer genomics and immunotherapy”. Nature reviews. Cancer. 13 (6): 397–411. doi:10.1038/nrc3526. PMID 23702928. Unknown parameter
|month=ignored (help) - ↑ Julie A. Tomolonis, Saurabh Agarwal & Jason M. Shohet (2018). “Neuroblastoma pathogenesis: deregulation of embryonic neural crest development”. Cell and tissue research. 372 (2): 245–262. doi:10.1007/s00441-017-2747-0. PMID 29222693. Unknown parameter
|month=ignored (help) - ↑ M. Schwab, K. Alitalo, K. H. Klempnauer, H. E. Varmus, J. M. Bishop, F. Gilbert, G. Brodeur, M. Goldstein & J. Trent (1983). “Amplified DNA with limited homology to myc cellular oncogene is shared by human neuroblastoma cell lines and a neuroblastoma tumour”. Nature. 305 (5931): 245–248. PMID 6888561. Unknown parameter
|month=ignored (help) - ↑ 6.0 6.1 Neuroblastoma. Wikipedia(2015) https://en.wikipedia.org/wiki/Neuroblastoma Accessed on October, 5 2015
- ↑ Colon NC, Chung DH (2011). “Neuroblastoma”. Adv Pediatr. 58 (1): 297–311. doi:10.1016/j.yapd.2011.03.011. PMC 3668791. PMID 21736987.
- ↑ Delphine Trochet, Franck Bourdeaut, Isabelle Janoueix-Lerosey, Anne Deville, Loic de Pontual, Gudrun Schleiermacher, Carole Coze, Nicole Philip, Thierry Frebourg, Arnold Munnich, Stanislas Lyonnet, Olivier Delattre & Jeanne Amiel (2004). “Germline mutations of the paired-like homeobox 2B (PHOX2B) gene in neuroblastoma”. American journal of human genetics. 74 (4): 761–764. doi:10.1086/383253. PMID 15024693. Unknown parameter
|month=ignored (help) - ↑ Kai Wang, Sharon J. Diskin, Haitao Zhang, Edward F. Attiyeh, Cynthia Winter, Cuiping Hou, Robert W. Schnepp, Maura Diamond, Kristopher Bosse, Patrick A. Mayes, Joseph Glessner, Cecilia Kim, Edward Frackelton, Maria Garris, Qun Wang, Wendy Glaberson, Rosetta Chiavacci, Le Nguyen, Jayanti Jagannathan, Norihisa Saeki, Hiroki Sasaki, Struan F. A. Grant, Achille Iolascon, Yael P. Mosse, Kristina A. Cole, Hongzhe Li, Marcella Devoto, Patrick W. McGrady, Wendy B. London, Mario Capasso, Nazneen Rahman, Hakon Hakonarson & John M. Maris (2011). “Integrative genomics identifies LMO1 as a neuroblastoma oncogene”. Nature. 469 (7329): 216–220. doi:10.1038/nature09609. PMID 21124317. Unknown parameter
|month=ignored (help) - ↑ Teeara Berry, William Luther, Namrata Bhatnagar, Yann Jamin, Evon Poon, Takaomi Sanda, Desheng Pei, Bandana Sharma, Winston R. Vetharoy, Albert Hallsworth, Zai Ahmad, Karen Barker, Lisa Moreau, Hannah Webber, Wenchao Wang, Qingsong Liu, Antonio Perez-Atayde, Scott Rodig, Nai-Kong Cheung, Florence Raynaud, Bengt Hallberg, Simon P. Robinson, Nathanael S. Gray, Andrew D. J. Pearson, Suzanne A. Eccles, Louis Chesler & Rani E. George (2012). “The ALK(F1174L) mutation potentiates the oncogenic activity of MYCN in neuroblastoma”. Cancer cell. 22 (1): 117–130. doi:10.1016/j.ccr.2012.06.001. PMID 22789543. Unknown parameter
|month=ignored (help) - ↑ G. M. Brodeur, G. Sekhon & M. N. Goldstein (1977). “Chromosomal aberrations in human neuroblastomas”. Cancer. 40 (5): 2256–2263. PMID 922665. Unknown parameter
|month=ignored (help) - ↑ 12.00 12.01 12.02 12.03 12.04 12.05 12.06 12.07 12.08 12.09 12.10 Neuroblastoma. Libre Pathology (2015) http://librepathology.org/wiki/index.php/Adrenal_gland#Neuroblastoma Accessed on October, 5 2015
- ↑ Atsuko Nakazawa, Chizuko Haga, Miki Ohira, Hajime Okita, Takehiko Kamijo & Akira Nakagawara (2015). “Correlation between the International Neuroblastoma Pathology Classification and genomic signature in neuroblastoma”. Cancer science. 106 (6): 766–771. doi:10.1111/cas.12665. PMID 25827934. Unknown parameter
|month=ignored (help) - ↑ Neuroblastoma, Ganglioneuroblastoma and Ganglioneuroma. Stanford Medicine Surgical Pathology Criteria(2015) http://surgpathcriteria.stanford.edu/srbc/neuroblastoma-ganglioneuroblastoma-ganglioneuroma/ Accessed on October, 5 2015
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Haytham Allaham, M.D. [2] Zahir Ali Shaikh, MD[3]
Causes
Overview
There are no known established causes for neuroblastoma.
Causes
- There are no known established causes for neuroblastoma.[1]
References
- ↑ Tadeusz Izbicki, Joanna Mazur & Elzbieta Izbicka (2003). “Epidemiology and etiology of neuroblastoma: an overview”. Anticancer research. 23 (1B): 755–760. PMID 12680179. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Haytham Allaham, M.D. [2] Zahir Ali Shaikh, MD[3]
Differentiating Neuroblastoma from other diseases

Overview
Intra-abdominal neuroblastoma must be differentiated from other diseases that cause abdominal distension and constipation such as Wilms tumor and ganglioneuroma. Intra-thoracic neuroblastoma must be differentiated from other diseases that cause shortness of breath and chronic cough such as intrathoracic lymphoma and extra lobar pulmonary sequestration.
Differentiationg Neuroblastoma from other Diseases
Abbreviations
ACTH: Adrenocorticotropic hormone, ARR: Aldosterone-renin ratio, CAM: Cellular adhesion molecules, ERCP: Endoscopic retrograde cholangiopancreatography, ESR: Erythrocyte sedimentation rate, CT: Computerized tomography, Fluorescence in situ hybridization, FDG: Fluorodeoxyglucose, FSH: Follicle stimulating hormone, GI: Gastrointestinal, H&E stain: Hematoxylin and eosin stain, LCA: Leukocyte common antigen, LDH: Lactate dehydrogenase, LH: Luteinizing hormone, MEN: Multiple endocrine neoplasia, MRCP: Magnetic resonance cholangiopancreatography, MRI: Magnetic resonance imaging, N/A: Not applicable/Not available, N/L: Normal, PAS stain: Periodic acid–Schiff stain, PET: Position emission tomography, PGP: Protein gene product 9.5, TB: Tuberculosis, U/S: Ultrasound, ZF: Zona fasciculata, ZG: Zona granulosa, ZR: Zona reticularis.
| Adrenal Cortex | Product | Clinical manifestations | Diagnosis | Other features | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Symptoms | Signs | Blood & Urine | Histopathological | Others | Ultrasound | CT scan | FDG PET/CT | MRI | |||
| Adrenal Adenoma | Aldosterone [1][2][3][4] |
|
|
|
| ||||||
| Cortisol [1][5][6][7] |
|
|
|
|
|
||||||
| Androgens [4][8][9][10] |
|
|
|
|
|
|
|
||||
| Non-functional [1][11][12][13] |
|
|
|
|
|
|
|
| |||
| Adrenal Carcinoma [12][14][15][16][17] |
|
|
|
|
|
|
|
|
| ||
| Adrenal Hyperplasia [2][5][4][8][9][15][18][19] |
|
|
|
|
|
|
|
|
|||
| Medulla | Product | Clinical manifestations | Diagnosis | Other features | |||||||
| Symptoms | Signs | Blood & Urine | Histopathological | Others | Ultrasound | CT scan | FDG PET/CT | MRI | |||
| Pheochromocytoma [20][21][22][23][24] |
|
|
|
|
|
|
|
| |||
| Neuroblastoma [15][25][26][27] |
|
|
|
|
|
|
|
|
|
Stains positive for:
| |
| Ganglioneuroma [15][28][29][30] |
|
|
|
|
|
|
|
Stains positive for: |
|||
| Stroma | Product | Clinical manifestations | Diagnosis | Other features | |||||||
| Symptoms | Signs | Blood & Urine | Histopathological | Others | Ultrasound | CT scan | FDG PET/CT | MRI | |||
| Lipoma/Myolipoma [15][31][32][33] |
|
|
|
|
|
|
|
|
|||
| Others | Product | Clinical manifestations | Diagnosis | Other features | |||||||
| Symptoms | Signs | Blood & Urine | Histopathological | Others | Ultrasound | CT scan | FDG PET/CT | MRI | |||
| Tuberculosis [34][35][36][37][38] |
|
|
|
|
|
|
|
|
| ||
| Histoplasmosis [39][40][41][42][43] |
|
|
|
|
|
|
|
| |||
| Cysts [15][44][45][46] |
|
|
|
|
|
|
|
|
|
| |
| Hematoma [15][47][48][49] |
|
|
|
|
|
|
|
|
|
|
|
| Hemangioma [15][50][51][52] |
|
|
|
|
|
|
|
|
|
||
| Lymphoma [15][53][54][55] |
|
|
|
|
|
|
|
|
|||
| Cystic Lymphangioma [15][56][57][58] |
|
|
|
|
|
|
|
|
|
| |
| Teratoma [15][59][60][61] |
|
|
|
|
|
|
|
|
|||
| Metastases [15][62][63][64][65] |
|
|
|
|
|
|
|
OR
|
| ||
References
- ↑ 1.0 1.1 1.2 Park JJ, Park BK, Kim CK (June 2016). “Adrenal imaging for adenoma characterization: imaging features, diagnostic accuracies and differential diagnoses”. Br J Radiol. 89 (1062): 20151018. doi:10.1259/bjr.20151018. PMC 5258164. PMID 26867466.
- ↑ 2.0 2.1 Monticone S, Castellano I, Versace K, Lucatello B, Veglio F, Gomez-Sanchez CE, Williams TA, Mulatero P (August 2015). “Immunohistochemical, genetic and clinical characterization of sporadic aldosterone-producing adenomas”. Mol. Cell. Endocrinol. 411: 146–54. doi:10.1016/j.mce.2015.04.022. PMC 4474471. PMID 25958045.
- ↑ Stowasser M, Taylor PJ, Pimenta E, Ahmed AH, Gordon RD (May 2010). “Laboratory investigation of primary aldosteronism”. Clin Biochem Rev. 31 (2): 39–56. PMC 2874431. PMID 20498828.
- ↑ 4.0 4.1 4.2 Guerrisi A, Marin D, Baski M, Guerrisi P, Capozza F, Catalano C (2013). “Adrenal lesions: spectrum of imaging findings with emphasis on multi-detector computed tomography and magnetic resonance imaging”. J Clin Imaging Sci. 3: 61. doi:10.4103/2156-7514.124088. PMC 3935261. PMID 24605256.
- ↑ 5.0 5.1 Stratakis CA (2008). “Cushing syndrome caused by adrenocortical tumors and hyperplasias (corticotropin- independent Cushing syndrome)”. Endocr Dev. 13: 117–32. doi:10.1159/000134829. PMC 3132884. PMID 18493137.
- ↑ Zilbermint M, Stratakis CA (June 2015). “Protein kinase A defects and cortisol-producing adrenal tumors”. Curr Opin Endocrinol Diabetes Obes. 22 (3): 157–62. doi:10.1097/MED.0000000000000149. PMC 4560837. PMID 25871963.
- ↑ Wei J, Li S, Liu Q, Zhu Y, Wu N, Tang Y, Li Q, Ren K, Zhang Q, Yu Y, An Z, Chen J, Li J (April 2018). “ACTH-independent Cushing’s syndrome with bilateral cortisol-secreting adrenal adenomas: a case report and review of literatures”. BMC Endocr Disord. 18 (1): 22. doi:10.1186/s12902-018-0250-6. PMC 5913873. PMID 29685132.
- ↑ 8.0 8.1 Arnold DT, Reed JB, Burt K (January 2003). “Evaluation and management of the incidental adrenal mass”. Proc (Bayl Univ Med Cent). 16 (1): 7–12. PMC 1200803. PMID 16278716.
- ↑ 9.0 9.1 Rodríguez-Gutiérrez R, Bautista-Medina MA, Teniente-Sanchez AE, Zapata-Rivera MA, Montes-Villarreal J (2013). “Pure androgen-secreting adrenal adenoma associated with resistant hypertension”. Case Rep Endocrinol. 2013: 356086. doi:10.1155/2013/356086. PMC 3681270. PMID 23819074.
- ↑ Zhou WB, Chen N, Li CJ (January 2019). “A rare case of pure testosterone-secreting adrenal adenoma in a postmenopausal elderly woman”. BMC Endocr Disord. 19 (1): 14. doi:10.1186/s12902-019-0342-y. PMC 6343319. PMID 30674304.
- ↑ Lopez D, Luque-Fernandez MA, Steele A, Adler GK, Turchin A, Vaidya A (October 2016). ““Nonfunctional” Adrenal Tumors and the Risk for Incident Diabetes and Cardiovascular Outcomes: A Cohort Study”. Ann. Intern. Med. 165 (8): 533–542. doi:10.7326/M16-0547. PMC 5453639. PMID 27479926.
- ↑ 12.0 12.1 Nieman LK (September 2010). “Approach to the patient with an adrenal incidentaloma”. J. Clin. Endocrinol. Metab. 95 (9): 4106–13. doi:10.1210/jc.2010-0457. PMC 2936073. PMID 20823463.
- ↑ Li B, Guo Q, Yang H, Guan J (January 2013). “Giant non-functional adrenal adenoma: A case report”. Oncol Lett. 5 (1): 378–380. doi:10.3892/ol.2012.978. PMC 3525484. PMID 23255953.
- ↑ Libé R (2015). “Adrenocortical carcinoma (ACC): diagnosis, prognosis, and treatment”. Front Cell Dev Biol. 3: 45. doi:10.3389/fcell.2015.00045. PMC 4490795. PMID 26191527.
- ↑ 15.00 15.01 15.02 15.03 15.04 15.05 15.06 15.07 15.08 15.09 15.10 15.11 Wang F, Liu J, Zhang R, Bai Y, Li C, Li B, Liu H, Zhang T (September 2018). “CT and MRI of adrenal gland pathologies”. Quant Imaging Med Surg. 8 (8): 853–875. doi:10.21037/qims.2018.09.13. PMC 6177362. PMID 30306064.
- ↑ Else T, Kim AC, Sabolch A, Raymond VM, Kandathil A, Caoili EM, Jolly S, Miller BS, Giordano TJ, Hammer GD (April 2014). “Adrenocortical carcinoma”. Endocr. Rev. 35 (2): 282–326. doi:10.1210/er.2013-1029. PMC 3963263. PMID 24423978.
- ↑ Wang C, Sun Y, Wu H, Zhao D, Chen J (March 2014). “Distinguishing adrenal cortical carcinomas and adenomas: a study of clinicopathological features and biomarkers”. Histopathology. 64 (4): 567–76. doi:10.1111/his.12283. PMC 4282325. PMID 24102952.
- ↑ Michelle M A, Jensen CT, Habra MA, Menias CO, Shaaban AM, Wagner-Bartak NA, Roman-Colon AM, Elsayes KM (November 2017). “Adrenal cortical hyperplasia: diagnostic workup, subtypes, imaging features and mimics”. Br J Radiol. 90 (1079): 20170330. doi:10.1259/bjr.20170330. PMC 5963387. PMID 28707538. Vancouver style error: name (help)
- ↑ Zhang Y, Li H (2015). “Classification and surgical treatment for 180 cases of adrenocortical hyperplastic disease”. Int J Clin Exp Med. 8 (10): 19311–7. PMC 4694469. PMID 26770569.
- ↑ Martucci VL, Pacak K (2014). “Pheochromocytoma and paraganglioma: diagnosis, genetics, management, and treatment”. Curr Probl Cancer. 38 (1): 7–41. doi:10.1016/j.currproblcancer.2014.01.001. PMC 3992879. PMID 24636754.
- ↑ Kantorovich V, Pacak K (2010). “Pheochromocytoma and paraganglioma”. Prog. Brain Res. 182: 343–73. doi:10.1016/S0079-6123(10)82015-1. PMC 4714594. PMID 20541673.
- ↑ Miller AD, Masek-Hammerman K, Dalecki K, Mansfield KG, Westmoreland SV (November 2009). “Histologic and immunohistochemical characterization of pheochromocytoma in 6 cotton-top tamarins (Saguinus oedipus)”. Vet. Pathol. 46 (6): 1221–9. doi:10.1354/vp.09-VP-0022-M-FL. PMID 19605896.
- ↑ Kantorovich V, Eisenhofer G, Pacak K (December 2008). “Pheochromocytoma: an endocrine stress mimicking disorder”. Ann. N. Y. Acad. Sci. 1148: 462–8. doi:10.1196/annals.1410.081. PMC 2693284. PMID 19120142.
- ↑ Eisenhofer G, Peitzsch M (December 2014). “Laboratory evaluation of pheochromocytoma and paraganglioma”. Clin. Chem. 60 (12): 1486–99. doi:10.1373/clinchem.2014.224832. PMID 25332315.
- ↑ Vo KT, Matthay KK, Neuhaus J, London WB, Hero B, Ambros PF, Nakagawara A, Miniati D, Wheeler K, Pearson AD, Cohn SL, DuBois SG (October 2014). “Clinical, biologic, and prognostic differences on the basis of primary tumor site in neuroblastoma: a report from the international neuroblastoma risk group project”. J. Clin. Oncol. 32 (28): 3169–76. doi:10.1200/JCO.2014.56.1621. PMC 4171360. PMID 25154816.
- ↑ Bordbar M, Tasbihi M, Kamfiroozi R, Haghpanah S (2014). “Epidemiological and clinical characteristics of neuroblastoma in southern iran”. Iran J Ped Hematol Oncol. 4 (3): 89–96. PMC 4173027. PMID 25254086.
- ↑ Skoura E, Oikonomopoulos G, Vasileiou S, Kyprianou D, Koumakis G, Datseris IE (2014). “(18)F-FDG-PET/CT, (123)I-MIBG and (99m)Tc-MDP whole-body scans, in detecting recurrence of an adult adrenal neuroblastoma”. Hell J Nucl Med. 17 (1): 58–61. doi:10.1967/s002449910116. PMID 24563879.
- ↑ Mylonas KS, Schizas D, Economopoulos KP (October 2017). “Adrenal ganglioneuroma: What you need to know”. World J Clin Cases. 5 (10): 373–377. doi:10.12998/wjcc.v5.i10.373. PMC 5648998. PMID 29085827.
- ↑ Adas M, Koc B, Adas G, Ozulker F, Aydin T (April 2014). “Ganglioneuroma presenting as an adrenal incidentaloma: a case report”. J Med Case Rep. 8: 131. doi:10.1186/1752-1947-8-131. PMC 4031973. PMID 24779851.
- ↑ Li J, Yang CH, Li LM (April 2013). “Diagnosis and treatment of 29 cases of adrenal ganglioneuroma”. Eur Rev Med Pharmacol Sci. 17 (8): 1110–3. PMID 23661526.
- ↑ Lam KY, Lo CY (September 2001). “Adrenal lipomatous tumours: a 30 year clinicopathological experience at a single institution”. J. Clin. Pathol. 54 (9): 707–12. PMC 1731508. PMID 11533079.
- ↑ Gershuni VM, Bittner JG, Moley JF, Brunt LM (January 2014). “Adrenal myelolipoma: operative indications and outcomes”. J Laparoendosc Adv Surg Tech A. 24 (1): 8–12. doi:10.1089/lap.2013.0411. PMC 3931430. PMID 24328509.
- ↑ Luo J, Chen L, Wen Q, Xu L, Chu S, Wang W, Alnemah MM, Fan S (2015). “Lipoadenoma of the adrenal gland: report of a rare entity and review of literature”. Int J Clin Exp Pathol. 8 (8): 9693–7. PMC 4583971. PMID 26464739.
- ↑ Rodríguez-Gutiérrez R, Rendon A, Barrera-Sánchez M, Carlos-Reyna KE, Álvarez-Villalobos NA, González-Saldivar G, González-González JG (2016). “Multidrug-Resistant Tuberculosis and Its Association with Adrenal Insufficiency: Assessment with the Low-Dose ACTH Stimulation Test”. Int J Endocrinol. 2016: 9051865. doi:10.1155/2016/9051865. PMC 4781954. PMID 27006656.
- ↑ Haddara WM, van Uum SH (September 2004). “TB and adrenal insufficiency”. CMAJ. 171 (7): 710, author reply 710–1. doi:10.1503/cmaj.1041046. PMC 517840. PMID 15451821.
- ↑ Huang YC, Tang YL, Zhang XM, Zeng NL, Li R, Chen TW (October 2015). “Evaluation of primary adrenal insufficiency secondary to tuberculous adrenalitis with computed tomography and magnetic resonance imaging: Current status”. World J Radiol. 7 (10): 336–42. doi:10.4329/wjr.v7.i10.336. PMC 4620114. PMID 26516430.
- ↑ Vinnard C, Blumberg EA (January 2017). “Endocrine and Metabolic Aspects of Tuberculosis”. Microbiol Spectr. 5 (1). doi:10.1128/microbiolspec.TNMI7-0035-2016. PMID 28233510.
- ↑ Rajasekharan C, Ajithkumar S, Anto V, Parvathy R (May 2013). “Extrapulmonary disseminated tuberculosis with tuberculous adrenalitis: a stitch in time saves nine”. BMJ Case Rep. 2013. doi:10.1136/bcr-2012-008011. PMID 23687365.
- ↑ Rog CJ, Rosen DG, Gannon FH (December 2016). “Bilateral adrenal histoplasmosis in an immunocompetent man from Texas”. Med Mycol Case Rep. 14: 4–7. doi:10.1016/j.mmcr.2016.11.006. PMC 5154969. PMID 27995051.
- ↑ Wahab NA, Mohd R, Zainudin S, Kamaruddin NA (2013). “Adrenal involvement in histoplasmosis”. EXCLI J. 12: 1–4. PMC 4817423. PMID 27047312.
- ↑ May D, Khaled D, Gills J (July 2018). “Unilateral adrenal histoplasmosis”. Urol Case Rep. 19: 54–56. doi:10.1016/j.eucr.2018.03.010. PMC 5991316. PMID 29888193.
- ↑ Gupta RK, Majumdar K, Srivastava S, Varakanahalli S, Saran RK (2018). “Endoscopic Ultrasound-guided Cytodiagnosis of Adrenal Histoplasmosis with Reversible CD4 T-Lymphocytopenia and Jejunal Lymphangiectasia”. J Cytol. 35 (2): 110–113. doi:10.4103/JOC.JOC_234_15. PMC 5885598. PMID 29643659.
- ↑ Padma S, Sreehar S (May 2014). “18F FDG PET/CT identifies unsuspected bilateral adrenal histoplasmosis in an elderly immuno compromised patient”. Indian J. Med. Res. 139 (5): 786–7. PMC 4140048. PMID 25027093.
- ↑ Carsote M, Ghemigian A, Terzea D, Gheorghisan-Galateanu AA, Valea A (2017). “Cystic adrenal lesions: focus on pediatric population (a review)”. Clujul Med. 90 (1): 5–12. doi:10.15386/cjmed-677. PMID 28246490.
- ↑ Słapa RZ, Jakubowski WS, Dobruch-Sobczak K, Kasperlik-Załuska AA (December 2015). “Standards of ultrasound imaging of the adrenal glands”. J Ultrason. 15 (63): 377–87. doi:10.15557/JoU.2015.0035. PMC 4710689. PMID 26807295.
- ↑ Olaoye IO, Adesina MD, Afolayan EA (June 2018). “A giant adrenal cyst with an uncertain preoperative diagnosis causing a dilemma in management”. Clin Case Rep. 6 (6): 1074–1076. doi:10.1002/ccr3.1519. PMC 5986023. PMID 29881567.
- ↑ Hamilton D, Harris MD, Foweraker J, Gresham GA (February 2004). “Waterhouse-Friderichsen syndrome as a result of non-meningococcal infection”. J. Clin. Pathol. 57 (2): 208–9. PMC 1770213. PMID 14747454.
- ↑ Di Serafino M, Severino R, Coppola V, Gioioso M, Rocca R, Lisanti F, Scarano E (September 2017). “Nontraumatic adrenal hemorrhage: the adrenal stress”. Radiol Case Rep. 12 (3): 483–487. doi:10.1016/j.radcr.2017.03.020. PMC 5551907. PMID 28828107.
- ↑ Ierardi AM, Petrillo M, Patella F, Biondetti P, Fumarola EM, Angileri SA, Pesapane F, Pinto A, Dionigi G, Carrafiello G (April 2018). “Interventional radiology of the adrenal glands: current status”. Gland Surg. 7 (2): 147–165. doi:10.21037/gs.2018.01.04. PMC 5938278. PMID 29770310.
- ↑ Alhajri K, Alhasan I, Alzerwi N, Abudaff N (April 2011). “Adrenal haemangioma”. BMJ Case Rep. 2011. doi:10.1136/bcr.12.2010.3604. PMC 3079485. PMID 22701011.
- ↑ Iwamoto G, Shimokihara K, Kawahara T, Takamoto D, Yao M, Teranishi JI, Otani M, Uemura H (2018). “Adrenal Hemangioma: A Case of Retroperitoneal Tumor”. Case Rep Med. 2018: 8796327. doi:10.1155/2018/8796327. PMC 5836307. PMID 29560018.
- ↑ Tarchouli M, Boudhas A, Ratbi MB, Essarghini M, Njoumi N, Sair K, Zentar A (2015). “Giant adrenal hemangioma: Unusual cause of huge abdominal mass”. Can Urol Assoc J. 9 (11–12): E834–6. doi:10.5489/cuaj.2967. PMC 4639440. PMID 26600897.
- ↑ Harada K, Kimura K, Iwamuro M, Terasaka T, Hanayama Y, Kondo E, Hayashi E, Yoshino T, Otsuka F (September 2017). “The Clinical and Hormonal Characteristics of Primary Adrenal Lymphomas: The Necessity of Early Detection of Adrenal Insufficiency”. Intern. Med. 56 (17): 2261–2269. doi:10.2169/internalmedicine.8216-16. PMC 5635296. PMID 28794358.
- ↑ Laurent C, Casasnovas O, Martin L, Chauchet A, Ghesquieres H, Aussedat G, Fornecker LM, Bologna S, Borot S, Laurent K, Bouillet B, Verges B, Petit JM (February 2017). “Adrenal lymphoma: presentation, management and prognosis”. QJM. 110 (2): 103–109. doi:10.1093/qjmed/hcw174. PMID 27795295.
- ↑ Karimi F (October 2017). “Primary Adrenal Lymphoma Presenting with Adrenal Failure: A Case Report and Review of the Literature”. Int J Endocrinol Metab. 15 (4): e12014. doi:10.5812/ijem.12014. PMC 5750783. PMID 29344029.
- ↑ Michalopoulos N, Laskou S, Karayannopoulou G, Pavlidis L, Kanellos I (December 2015). “Adrenal Gland Lymphangiomas”. Indian J Surg. 77 (Suppl 3): 1334–42. doi:10.1007/s12262-015-1206-y. PMC 4775622. PMID 27011561.
- ↑ Zhao M, Gu Q, Li C, Yu J, Qi H (2014). “Cystic lymphangioma of adrenal gland: a clinicopathological study of 3 cases and review of literature”. Int J Clin Exp Pathol. 7 (8): 5051–6. PMC 4152068. PMID 25197378.
- ↑ Joliat GR, Melloul E, Djafarrian R, Schmidt S, Fontanella S, Yan P, Demartines N, Halkic N (February 2015). “Cystic lymphangioma of the adrenal gland: report of a case and review of the literature”. World J Surg Oncol. 13: 58. doi:10.1186/s12957-015-0490-0. PMC 4335415. PMID 25889625.
- ↑ Ramakant P, Rana C, Singh KR, Mishra A (2018). “Primary adrenal teratoma: An unusual tumor – Challenges in diagnosis and surgical management”. J Postgrad Med. 64 (2): 112–114. doi:10.4103/jpgm.JPGM_588_16. PMC 5954807. PMID 29067922.
- ↑ Li S, Li H, Ji Z, Yan W, Zhang Y (November 2015). “Primary adrenal teratoma: Clinical characteristics and retroperitoneal laparoscopic resection in five adults”. Oncol Lett. 10 (5): 2865–2870. doi:10.3892/ol.2015.3701. PMC 4665718. PMID 26722254.
- ↑ Zhou L, Pan X, He T, Lai Y, Li W, Hu Y, Ni L, Yang S, Chen Y, Lai Y (October 2018). “Primary adrenal teratoma: A case series and review of the literature”. Mol Clin Oncol. 9 (4): 437–442. doi:10.3892/mco.2018.1687. PMC 6125700. PMID 30214733.
- ↑ Karanikiotis C, Tentes AA, Markakidis S, Vafiadis K (November 2004). “Large bilateral adrenal metastases in non-small cell lung cancer”. World J Surg Oncol. 2: 37. doi:10.1186/1477-7819-2-37. PMC 535544. PMID 15541184.
- ↑ ABRAMS HL, SPIRO R, GOLDSTEIN N (January 1950). “Metastases in carcinoma; analysis of 1000 autopsied cases”. Cancer. 3 (1): 74–85. PMID 15405683.
- ↑ Gerber E, Dinlenc C, Wagner JR (2004). “Laparoscopic adrenalectomy for isolated adrenal metastasis”. JSLS. 8 (4): 314–9. PMC 3016821. PMID 15554272.
- ↑ Vaughan ED (September 1998). “Diagnosis and management of surgical adrenal disorders”. Int. J. Urol. 5 (5): 401–17. PMID 9781426.
References
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]
Epidemiology and Demographics
Overview
Neuroblastoma is the most common solid extracranial cancer in childhood and is the most common cancer in infancy. The overall incidence is 4.9 per 1,000,000 individuals in United states. Males are slightly more affected than females with 1.2:1 ratio. The incidence of neuroblastoma decreases with age and the highest incidence is in the first year of life. Neuroblastoma usually affects individuals of the Caucasian race.
Epidemiology and Demographics
Incidence
- The overall incidence rate of neuroblastoma is approximately 4.9 per 1,000,000 individuals in the United States.[1][2]
Prevalence
- Neuroblastoma is the most common extracranial solid cancer in childhood and the most common cancer in infancy.[3][4][5]
Age
- The incidence of neuroblastoma decreases with age; the highest incidence is in the first year of life.[6]
- The incidence of neuroblastoma according to specific age groups is approximately:[1]
- 25.3 per 1,000,000 individuals aged between (0-4) years
- 2.3 per 1,000,000 individuals aged between (5-9) years
- 0.7 per 1,000,000 individuals aged between (10-14) years
- 0.2 per 1,000,000 individuals aged between (20-24) years
- 0.3 per 1,000,000 individuals aged between (25-29) years
Gender
- Males are slightly more commonly affected with neuroblastoma than females. The male to female ratio is approximately 1.12 to 1.[7]
- The incidence rate of neuroblastoma among males is approximately 5.1 per 1,000,000 individuals in the United States.
- The incidence rate of neuroblastoma among females is approximately 4.6 per 1,000,000 individuals in the United States.[1]
Race
- Neuroblastoma usually affects individuals of the Caucasian race. African Americans, Native Indians, and Asians are less likely to develop neuroblastoma.[8]
- The incidence rate of neuroblastoma among Caucasians is approximately 5.1 per 1,000,000 individuals in the United States.
- The incidence rate of neuroblastoma among African Americans is approximately 4.1 per 1,000,000 individuals in the United States.
- The overall incidence rate of neuroblastoma among Native Indians and Asians is approximately 3.8 per 1,000,000 individuals in the United States.[1]
References
- ↑ 1.0 1.1 1.2 1.3 Navalkele P, O’Dorisio MS, O’Dorisio TM, Zamba GK, Lynch CF (2011). “Incidence, survival, and prevalence of neuroendocrine tumors versus neuroblastoma in children and young adults: nine standard SEER registries, 1975-2006”. Pediatr Blood Cancer. 56 (1): 50–7. doi:10.1002/pbc.22559. PMC 4251713. PMID 21108439.
- ↑ J. G. Gurney, J. A. Ross, D. A. Wall, W. A. Bleyer, R. K. Severson & L. L. Robison (1997). “Infant cancer in the U.S.: histology-specific incidence and trends, 1973 to 1992”. Journal of pediatric hematology/oncology. 19 (5): 428–432. PMID 9329464. Unknown parameter
|month=ignored (help) - ↑ Tadeusz Izbicki, Joanna Mazur & Elzbieta Izbicka (2003). “Epidemiology and etiology of neuroblastoma: an overview”. Anticancer research. 23 (1B): 755–760. PMID 12680179. Unknown parameter
|month=ignored (help) - ↑ Tadeusz Izbicki, Joanna Mazur & Elzbieta Izbicka (2003). “Epidemiology of neuroblastoma: analysis of a single institution”. Anticancer research. 23 (2C): 1933–1938. PMID 12820482. Unknown parameter
|month=ignored (help) - ↑ Julie R. Park, Angelika Eggert & Huib Caron (2010). “Neuroblastoma: biology, prognosis, and treatment”. Hematology/oncology clinics of North America. 24 (1): 65–86. doi:10.1016/j.hoc.2009.11.011. PMID 20113896. Unknown parameter
|month=ignored (help) - ↑ Nadja C. Colon & Dai H. Chung (2011). “Neuroblastoma”. Advances in pediatrics. 58 (1): 297–311. doi:10.1016/j.yapd.2011.03.011. PMID 21736987.
- ↑ Julia E. Heck, Beate Ritz, Rayjean J. Hung, Mia Hashibe & Paolo Boffetta (2009). “The epidemiology of neuroblastoma: a review”. Paediatric and perinatal epidemiology. 23 (2): 125–143. doi:10.1111/j.1365-3016.2008.00983.x. PMID 19159399. Unknown parameter
|month=ignored (help) - ↑ N. L. Carlsen (1992). “Neuroblastoma: epidemiology and pattern of regression. Problems in interpreting results of mass screening”. The American journal of pediatric hematology/oncology. 14 (2): 103–110. PMID 1530115. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Haytham Allaham, M.D. [2] Zahir Ali Shaikh, MD[3]
Risk Factors
Overview
The risk factors for neuroblastomas diagnosed during infancy include; maternal anemia during pregnancy, neonatal respiratory distress syndrome and low 1 minute Apgar score. However, the risk factors for neuroblastoma cases diagnosed at age 1 year or above is not known.
Risk Factors
- The risk factors for neuroblastoma are not well known. However, following risk factors may be associated with neuroblastomas diagnosed during infancy:[1][2][3][4][5][6][7][8][9][10][11]
- Maternal anemia during pregnancy
- Maternal opiate consumption
- Maternal folate deficiency
- Toxic exposures
- Small or large for gestational age
- Gestational diabetes mellitus
- Neonatal respiratory distress syndrome
- Low 1 minute Apgar score
- Familial neuroblastoma
- Genetic factors
- Turner syndrome
- Neurofibromatosis type 1
- Germline chromosomal abnormality single-nucleotide polymorphisms (SNPs) at LMO1
- Germline mutations in SDHB, APC, ALK, and BRCA2
- The risk factors for neuroblastomas diagnosed at age 1 year or above is not known.[12]
References
- ↑ Elizabeth Bluhm, Dawn Elizabeth McNeil, Sven Cnattingius, Gloria Gridley, Laure El Ghormli & Joseph F. Jr Fraumeni (2008). “Prenatal and perinatal risk factors for neuroblastoma”. International journal of cancer. 123 (12): 2885–2890. doi:10.1002/ijc.23847. PMID 18798548. Unknown parameter
|month=ignored (help) - ↑ Amy E. French, Ron Grant, Sheila Weitzman, Joel G. Ray, Marian J. Vermeulen, Lillian Sung, Mark Greenberg & Gideon Koren (2003). “Folic acid food fortification is associated with a decline in neuroblastoma”. Clinical pharmacology and therapeutics. 74 (3): 288–294. doi:10.1016/S0009-9236(03)00200-5. PMID 12966372. Unknown parameter
|month=ignored (help) - ↑ G. R. Bunin, R. R. Kuijten, J. D. Buckley, L. B. Rorke & A. T. Meadows (1993). “Relation between maternal diet and subsequent primitive neuroectodermal brain tumors in young children”. The New England journal of medicine. 329 (8): 536–541. doi:10.1056/NEJM199308193290804. PMID 8336753. Unknown parameter
|month=ignored (help) - ↑ A. M. Michalek, G. M. Buck, P. C. Nasca, A. N. Freedman, M. S. Baptiste & M. C. Mahoney (1996). “Gravid health status, medication use, and risk of neuroblastoma”. American journal of epidemiology. 143 (10): 996–1001. PMID 8629618. Unknown parameter
|month=ignored (help) - ↑ Andrew F. Olshan, Joanna C. Smith, Melissa L. Bondy, Joseph P. Neglia & Brad H. Pollock (2002). “Maternal vitamin use and reduced risk of neuroblastoma”. Epidemiology (Cambridge, Mass.). 13 (5): 575–580. doi:10.1097/01.EDE.0000023970.93548.59. PMID 12192228. Unknown parameter
|month=ignored (help) - ↑ Eric J. Chow, Debra L. Friedman & Beth A. Mueller (2007). “Maternal and perinatal characteristics in relation to neuroblastoma”. Cancer. 109 (5): 983–992. doi:10.1002/cncr.22486. PMID 17285600. Unknown parameter
|month=ignored (help) - ↑ Oldridge DA, Wood AC, Weichert-Leahey N, Crimmins I, Sussman R, Winter C, McDaniel LD, Diamond M, Hart LS, Zhu S, Durbin AD, Abraham BJ, Anders L, Tian L, Zhang S, Wei JS, Khan J, Bramlett K, Rahman N, Capasso M, Iolascon A, Gerhard DS, Guidry Auvil JM, Young RA, Hakonarson H, Diskin SJ, Look AT, Maris JM (December 2015). “Genetic predisposition to neuroblastoma mediated by a LMO1 super-enhancer polymorphism”. Nature. 528 (7582): 418–21. doi:10.1038/nature15540. PMC 4775078. PMID 26560027.
- ↑ Origone P, Defferrari R, Mazzocco K, Lo Cunsolo C, De Bernardi B, Tonini GP (May 2003). “Homozygous inactivation of NF1 gene in a patient with familial NF1 and disseminated neuroblastoma”. Am. J. Med. Genet. A. 118A (4): 309–13. doi:10.1002/ajmg.a.10167. PMID 12687660.
- ↑ Cook MN, Olshan AF, Guess HA, Savitz DA, Poole C, Blatt J, Bondy ML, Pollock BH (April 2004). “Maternal medication use and neuroblastoma in offspring”. Am. J. Epidemiol. 159 (8): 721–31. PMID 15051581.
- ↑ Rios P, Bailey HD, Orsi L, Lacour B, Valteau-Couanet D, Levy D, Corradini N, Leverger G, Defachelles AS, Gambart M, Sirvent N, Thebaud E, Ducassou S, Clavel J (November 2016). “Risk of neuroblastoma, birth-related characteristics, congenital malformations and perinatal exposures: A pooled analysis of the ESCALE and ESTELLE French studies (SFCE)”. Int. J. Cancer. 139 (9): 1936–48. doi:10.1002/ijc.30239. PMID 27342419.
- ↑ Buck GM, Michalek AM, Chen CJ, Nasca PC, Baptiste MS (January 2001). “Perinatal factors and risk of neuroblastoma”. Paediatr Perinat Epidemiol. 15 (1): 47–53. PMID 11237115.
- ↑ Elizabeth Bluhm, Dawn Elizabeth McNeil, Sven Cnattingius, Gloria Gridley, Laure El Ghormli & Joseph F. Jr Fraumeni (2008). “Prenatal and perinatal risk factors for neuroblastoma”. International journal of cancer. 123 (12): 2885–2890. doi:10.1002/ijc.23847. PMID 18798548. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]
Screening
Overview
There is insufficient evidence to recommend the routine screening for neuroblastoma as it has no mortality benefits.
Screening
- There is insufficient evidence to recommend the routine screening for neuroblastoma by measuring the vanillylmandelic acid and homovanillic acid at 6 months or 1 year or age, as it does not have the mortality benefits.[1][2][3][4]
References
- ↑ Recommendations. US Preventive Services Task Force(2015) http://www.uspreventiveservicestaskforce.org/BrowseRec/Search?s=neuroblastoma Accessed on October, 5 2015
- ↑ William G. Woods, Ru-Nie Gao, Jonathan J. Shuster, Leslie L. Robison, Mark Bernstein, Sheila Weitzman, Greta Bunin, Isra Levy, Josee Brossard, Geoffrey Dougherty, Mendel Tuchman & Bernard Lemieux (2002). “Screening of infants and mortality due to neuroblastoma”. The New England journal of medicine. 346 (14): 1041–1046. doi:10.1056/NEJMoa012387. PMID 11932470. Unknown parameter
|month=ignored (help) - ↑ Freimut H. Schilling, Claudia Spix, Frank Berthold, Rudolf Erttmann, Natalja Fehse, Barbara Hero, Gisela Klein, Johannes Sander, Kerstin Schwarz, Joern Treuner, Ulrich Zorn & Joerg Michaelis (2002). “Neuroblastoma screening at one year of age”. The New England journal of medicine. 346 (14): 1047–1053. doi:10.1056/NEJMoa012277. PMID 11932471. Unknown parameter
|month=ignored (help) - ↑ “Neuroblastoma Screening (PDQ(R)): Health Professional Version”. 2002. PMID 26389460.
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]
Natural History, Complications and Prognosis
Overview
Neuroblastoma may progress to develop fatigue, loss of appetite, joint pain and fever if left untreated. There is gradual development of site specific symptoms as the tumor size gradually increases. Complications of neuroblastoma include persistent refractory diarrhea, horner’s syndrome, hypertension, transverse myelopathy, anemia and suppressed immunity. The prognosis of neuroblastoma is generally regarded as poor, depending on the tumor extent at the time of diagnosis. The other prognostic factors for nuroblastoma include patient’s age, tumor stage and grade, genetic mutations and response to treatment.
Natural History
- Neuroblastoma patients may initially present with vague symptoms making the diagnosis of such patients difficult.[1][2]
- If left untreated, patients with neuroblastoma may progress to develop fatigue, loss of appetite, joint pain, and fever.
- Gradual development of site specific symptoms may occur as the tumor size gradually increases.[3]
Complications
- Complications of neuroblastoma may include:[4][5][6]
- Persistent refractory diarrhea (due to vasoactive intestinal polypeptide secretion)
- Horner’s syndrome (due to cervical sympathetic chain compression)
- Opsoclonus myoclonus syndrome and ataxia (due to a paraneoplastic syndrome)
- Hypertension (due to either catecholamine secretion or renal artery compression)
- Transverse myelopathy (due to tumor spinal cord compression)
- Anemia and suppressed immunity (due to bone marrow metastasis)
Prognosis
- Depending on the extent of the tumor at the time of diagnosis, the prognosis may vary. However, the prognosis of neuroblastoma is generally regarded as poor.[7][8][9][10]
- INSS stage 1, stage 2, and stage 4S neuroblastomas are associated with a 3 year survival rate of 75-90%.
- INSS stage 3 neuroblastoma is associated with a 3 year survival rate of 80-90% among patients younger than 1 year of age.
- INSS stage 3 neuroblastoma is associated with a 3 year survival rate of 50% among patients older than 1 year of age.
- INSS stage 4 neuroblastoma is associated with a 3 year survival rate of 60-75% among patients younger than 1 year of age.
- INSS stage 4 neuroblastoma is associated with a 3 year survival rate of 15% among patients older than 1 year of age.
- The table below lists the prognostic factors for neuroblastoma patients:[11][12][13][14]
| Prognostic Factor | Description |
|---|---|
| Patient’s Age | |
| Tumor Stage |
|
| Tumor Grade | |
| Schwannnian Stroma |
|
| Mitotic-karyorrhectic Index |
|
| Genetic Mutations |
|
| Response to Treatment |
References
- ↑ L. M. Wilson & G. J. Draper (1974). “Neuroblastoma, its natural history and prognosis: a study of 487 cases”. British medical journal. 3 (5926): 301–307. PMID 4414795. Unknown parameter
|month=ignored (help) - ↑ Somruetai Shuangshoti, Shanop Shuangshoti, Issarang Nuchprayoon, Somjai Kanjanapongkul, Paula Marrano, Meredith S. Irwin & Paul S. Thorner (2012). “Natural course of low risk neuroblastoma”. Pediatric blood & cancer. 58 (5): 690–694. doi:10.1002/pbc.23325. PMID 21922650. Unknown parameter
|month=ignored (help) - ↑ C. S. Alvarado, W. B. London, A. T. Look, G. M. Brodeur, D. H. Altmiller, P. S. Thorner, V. V. Joshi, S. T. Rowe, M. B. Nash, E. I. Smith, R. P. Castleberry & S. L. Cohn (2000). “Natural history and biology of stage A neuroblastoma: a Pediatric Oncology Group Study”. Journal of pediatric hematology/oncology. 22 (3): 197–205. PMID 10864050. Unknown parameter
|month=ignored (help) - ↑ Nadja C. Colon & Dai H. Chung (2011). “Neuroblastoma”. Advances in pediatrics. 58 (1): 297–311. doi:10.1016/j.yapd.2011.03.011. PMID 21736987.
- ↑ John M. Maris (2010). “Recent advances in neuroblastoma”. The New England journal of medicine. 362 (23): 2202–2211. doi:10.1056/NEJMra0804577. PMID 20558371. Unknown parameter
|month=ignored (help) - ↑ Michal Sieniawski, Jeremy Franklin, Lucia Nogova, Jan-Peter Glossmann, Thomas Schober, Hiltrud Nisters-Backes, Volker Diehl & Andreas Josting (2007). “Outcome of patients experiencing progression or relapse after primary treatment with two cycles of chemotherapy and radiotherapy for early-stage favorable Hodgkin’s lymphoma”. Journal of clinical oncology : official journal of the American Society of Clinical Oncology. 25 (15): 2000–2005. doi:10.1200/JCO.2006.10.1386. PMID 17420510. Unknown parameter
|month=ignored (help) - ↑ Julie R. Park, Angelika Eggert & Huib Caron (2008). “Neuroblastoma: biology, prognosis, and treatment”. Pediatric clinics of North America. 55 (1): 97–120. doi:10.1016/j.pcl.2007.10.014. PMID 18242317. Unknown parameter
|month=ignored (help) - ↑ L. M. Wilson & G. J. Draper (1974). “Neuroblastoma, its natural history and prognosis: a study of 487 cases”. British medical journal. 3 (5926): 301–307. PMID 4414795. Unknown parameter
|month=ignored (help) - ↑ Maya Suzuki, Brian H. Kushner, Kim Kramer, Ellen M. Basu, Stephen S. Roberts, William J. Hammond, Michael P. LaQuaglia, Suzanne L. Wolden, Nai-Kong V. Cheung & Shakeel Modak (2018). “Treatment and outcome of adult-onset neuroblastoma”. International journal of cancer. 143 (5): 1249–1258. doi:10.1002/ijc.31399. PMID 29574715. Unknown parameter
|month=ignored (help) - ↑ Nermine O. Basta, Gail C. Halliday, Guy Makin, Jillian Birch, Richard Feltbower, Nick Bown, Martin Elliott, Lucas Moreno, Giuseppe Barone, Andrew Dj Pearson, Peter W. James, Deborah A. Tweddle & Richard Jq McNally (2016). “Factors associated with recurrence and survival length following relapse in patients with neuroblastoma”. British journal of cancer. 115 (9): 1048–1057. doi:10.1038/bjc.2016.302. PMID 27701387. Unknown parameter
|month=ignored (help) - ↑ Neuroblastoma. Radiopaedia(2015) http://radiopaedia.org/articles/neuroblastoma Accessed on October, 5 2015
- ↑ Neuroblastoma Treatment for health professionals. National Cancer Institute (2015) http://www.cancer.gov/types/neuroblastoma/hp/neuroblastoma-treatment-pdq#link/_534_toc Accessed on October, 7 2015
- ↑ Neuroblastoma. Libre Pathology(2015) http://librepathology.org/wiki/index.php/Adrenal_gland#Neuroblastoma Accessed on October, 5 2015
- ↑ G. Hale, M. J. Gula & J. Blatt (1994). “Impact of gender on the natural history of neuroblastoma”. Pediatric hematology and oncology. 11 (1): 91–97. PMID 8155504. Unknown parameter
|month=ignored (help)
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]
Diagnosis
Diagnosis
Staging | History and Symptoms | Physical Examination | Laboratory tests | X Ray | CT | MRI | Echocardiography or Ultrasound | Other Imaging Findings | Other Diagnostic Studies
For patient information click here.
Synonyms and keywords: Neuroblastomas; Sympathicoblastoma; Sympathicoblastomas; NB; Neuroblastoma sympathicum
Diagnosis
Staging | History and Symptoms | Physical Examination | Laboratory tests | X Ray | CT | MRI | Echocardiography or Ultrasound | Other Imaging Findings | Other Diagnostic Studies
Treatment
Medical therapy | Surgery | Cost-Effectiveness of Therapy | Future or Investigational Therapies
Additional Reading
- Neuroblastoma: biological insights into a clinical enigma. Brodeur GM. Nature Reviews Cancer. 2003 Mar;3(3):203-16. PMID 12612655
- Current aspects of biology, risk assessment, and treatment of neuroblastoma. Haase GM, Perez C, Atkinson JB. Semin Surg Oncol. 1999 Mar;16(2):91-104. PMID 9988866
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]
Treatment
Treatment
Medical therapy | Surgery | Cost-Effectiveness of Therapy | Future or Investigational Therapies
For patient information click here.
Synonyms and keywords: Neuroblastomas; Sympathicoblastoma; Sympathicoblastomas; NB; Neuroblastoma sympathicum
Diagnosis
Staging | History and Symptoms | Physical Examination | Laboratory tests | X Ray | CT | MRI | Echocardiography or Ultrasound | Other Imaging Findings | Other Diagnostic Studies
Treatment
Medical therapy | Surgery | Cost-Effectiveness of Therapy | Future or Investigational Therapies
Additional Reading
- Neuroblastoma: biological insights into a clinical enigma. Brodeur GM. Nature Reviews Cancer. 2003 Mar;3(3):203-16. PMID 12612655
- Current aspects of biology, risk assessment, and treatment of neuroblastoma. Haase GM, Perez C, Atkinson JB. Semin Surg Oncol. 1999 Mar;16(2):91-104. PMID 9988866
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]
Additional Reading
Additional Reading
- Neuroblastoma: biological insights into a clinical enigma. Brodeur GM. Nature Reviews Cancer. 2003 Mar;3(3):203-16. PMID 12612655
- Current aspects of biology, risk assessment, and treatment of neuroblastoma. Haase GM, Perez C, Atkinson JB. Semin Surg Oncol. 1999 Mar;16(2):91-104. PMID 9988866
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1] Associate Editor(s)-in-Chief: Zahir Ali Shaikh, MD[2]Haytham Allaham, M.D. [3]